Cystoid macular edema in retinitis pigmentosa is a treatable cause of reduced vision in a disease that is otherwise untreatable in most patients.
It occurs in a significant proportion of patients, and a trial of a carbonic anhydrase inhibitor can also improve both the cysts and the vision.
Recognizing it is therefore worth the effort.
How Common Is Cystoid Macular Edema in Retinitis Pigmentosa?
Studies using OCT have found cystoid spaces in the macula in about 10 to 50 percent of patients with retinitis pigmentosa, depending on the age, the type, and the method (see the references).
It is more frequent in some forms, such as Usher syndrome type 2 and autosomal dominant disease, and it can appear at any age.
It may also be unilateral or bilateral, and it often fluctuates.
Why It Happens
- Dysfunction of the retinal pigment epithelium, which fails to pump fluid out of the subretinal space
- Müller cell dysfunction, which reduces the clearance of fluid in the inner retina
- Breakdown of the blood-retinal barrier in some patients, with leakage on angiography
- Autoimmune and inflammatory factors, including antiretinal antibodies, in some cases
- Vitreomacular traction and epiretinal membrane, which can contribute
The exact mechanism probably varies, and several processes may act together.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteClinical Features of Cystoid Macular Edema in Retinitis Pigmentosa
- Reduced central vision, often worse than expected for the stage of disease, or fluctuating vision
- Metamorphopsia and difficulty reading
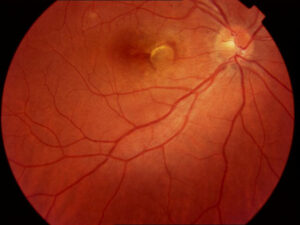
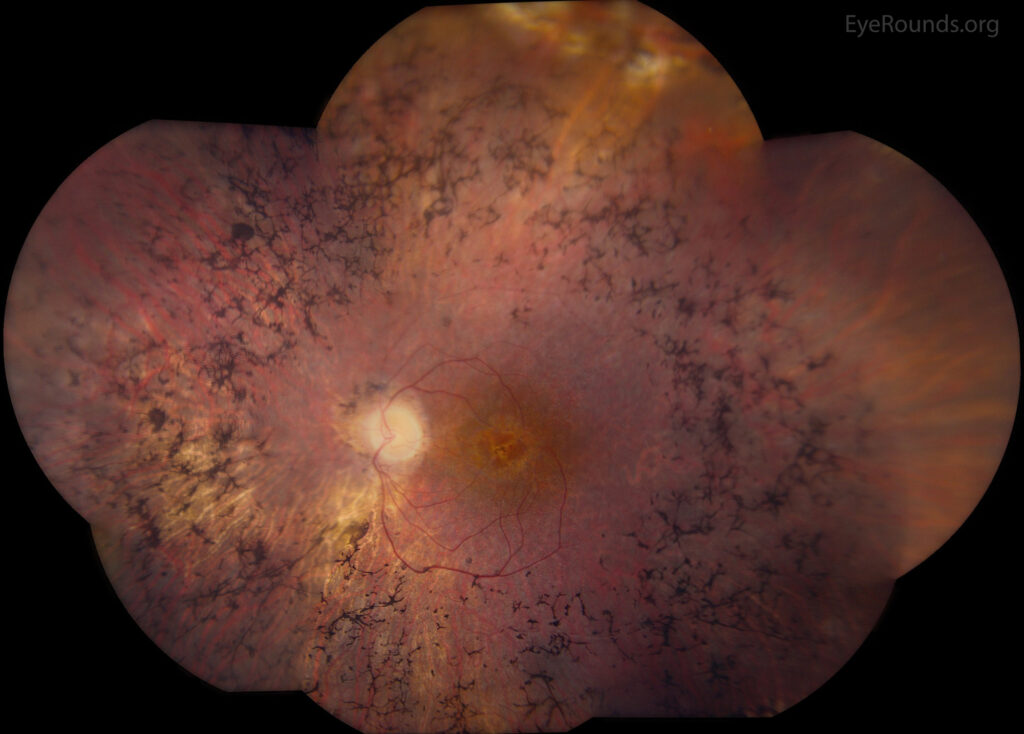
- An abnormal-looking macula on examination, or a normal one
- OCT showing cystoid spaces in the inner nuclear and outer plexiform layers, with thickening of the fovea
- Fluorescein angiography that often shows no leakage, in contrast to other forms of edema, though some patients show leakage (see macular edema causes)
OCT is the key investigation, as the cysts may be missed on examination.
Differential Diagnosis of Cystoid Macular Edema in Retinitis Pigmentosa
- Other forms of cystoid macular edema, such as postsurgical or diabetic (see cystoid macular edema)
- X-linked retinoschisis and Goldmann-Favre syndrome, with foveal schisis (see X-linked retinoschisis)
- Drug-induced cystoid changes, such as niacin or taxanes (see niacin maculopathy)
- Macular telangiectasia (see macular telangiectasia)
- Epiretinal membrane and vitreomacular traction (see epiretinal membrane)
A history of retinitis pigmentosa and the findings on the fundus usually make the diagnosis clear.
Cystoid Macular Edema in Retinitis Pigmentosa: Treatment Options
- Topical dorzolamide 2 percent: applied three times a day, and the best-studied topical treatment, which reduces the cysts and improves vision in a proportion of patients (see the references)
- Oral acetazolamide: a more potent option, used when topical treatment fails, with side effects such as paresthesia, fatigue, and kidney stones
- Other carbonic anhydrase inhibitors, such as methazolamide
- Intravitreal or periocular steroids, which may help in refractory cases, with the usual risks of cataract and raised pressure
- Intravitreal anti-VEGF drugs, with inconsistent results
- Topical or oral NSAIDs, with limited evidence (see NSAIDs for macular edema)
- Vitrectomy and peeling, when traction or a membrane is present
The response varies, and some eyes show recurrence after an initial improvement.
What to Expect From Treatment
- Genead and Fishman reported that sustained dorzolamide therapy reduced cystic lesions in many patients with retinitis pigmentosa and Usher syndrome (see the references)
- Vision improvement is often modest, and anatomic improvement is more common
- Treatment may need to be continued over time
- Patients who do not respond to one agent may respond to another
Because the underlying photoreceptor disease continues, the effect of treating the edema is limited by the amount of remaining retina.
Practical Approach
- Obtain OCT in every patient with retinitis pigmentosa who has reduced vision, and at regular intervals
- Start topical dorzolamide, and review in four to six weeks with repeat OCT
- Consider oral acetazolamide if there is no response, with monitoring of electrolytes and kidney function
- Reevaluate and consider other options if the edema persists
- Treat associated problems, such as cataract and epiretinal membrane
Document the response with OCT and acuity, and share the plan with the patient.
Counselling
Explain that the swelling is a treatable part of the disease, that treatment helps many patients, and that it may need to continue.
Also, remind patients that regular monitoring is important, and that they should report new changes in vision.
Case Example
A woman in her thirties with known retinitis pigmentosa reports that her reading has become worse over a few months, though her visual field is unchanged.
OCT shows cystoid spaces in both maculae, and angiography shows no leakage.
After three months of topical dorzolamide, the cysts are smaller and she reads two lines better, and the plan is to continue treatment with regular scans.
Monitoring and Limits
Repeat OCT every three to six months once the edema is controlled, since recurrence is possible.
Remind patients that the treatment addresses the swelling and does not stop the loss of photoreceptors, and discuss other supports, such as low vision services and genetic counselling (see inherited retinal disease genetic testing).


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Hajali M, Fishman GA, Anderson RJ. The prevalence of cystoid macular oedema in retinitis pigmentosa patients determined by optical coherence tomography. Br J Ophthalmol. 2008;92:1065-1068.
- Genead MA, Fishman GA. Efficacy of sustained topical dorzolamide therapy for cystic macular lesions in patients with retinitis pigmentosa and Usher syndrome. Arch Ophthalmol. 2010;128:1146-1150.
- Hartong DT, Berson EL, Dryja TP. Retinitis pigmentosa. Lancet. 2006;368:1795-1809.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 12: Retina and Vitreous. AAO; current edition.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.