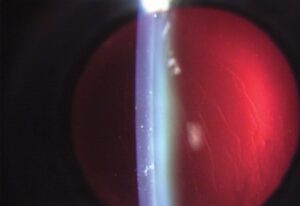
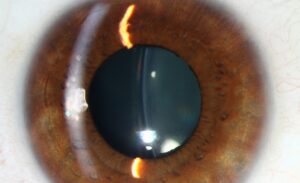
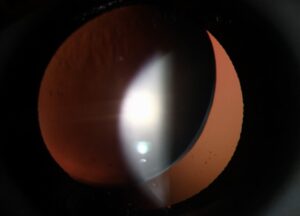
A sulcus-fixated IOL is a lens that surgeons place in front of the capsular bag, in the ciliary sulcus. They use it when the posterior capsule is lost but the anterior capsule is still intact.
It is the commonest backup after posterior capsule rupture.
It works well when surgeons use the right lens in the right way.
Mistakes in lens design or power can cause lasting problems.
When a Sulcus-Fixated IOL Is Possible
A sulcus lens needs sufficient support from the anterior capsule remnant and the ciliary sulcus.
- Posterior capsule rupture with an intact anterior capsulorhexis, the classic indication (see vitreous loss in cataract surgery)
- Zonular loss that is limited, with enough remaining support
- Late dislocation in the bag, with a stable anterior capsule
- Secondary lens placement in an aphakic eye with a residual capsule rim
If the anterior capsule is also lost, or the zonules are very weak, you need an alternative method of fixation, such as an iris-fixated or scleral-fixated lens (see iris-claw IOL).
Choosing the Lens
The right lens is a three-piece design with a large overall diameter, commonly 13 millimeters or more, with rounded, thick haptics.
Three-piece lenses have a stiffer haptic that holds well in the sulcus and a smooth edge.
Manufacturers do not design single-piece acrylic lenses for the sulcus, because their haptics are thick and sharp and can chafe the iris and ciliary body.
A report from the American Society of Cataract and Refractive Surgery committee reviewed complications of placing single-piece acrylic lenses in the sulcus, including pigment dispersion, glaucoma, hyphema, and lens decentration, and recommended the use of a three-piece lens as a backup.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteAdjusting the Lens Power
A lens in the sulcus sits about 0.5 to 1.0 millimeter in front of its position in the bag, so its effective power is higher.
Also, the surgeon reduces the power to prevent a myopic surprise, commonly by about 0.5 diopter for lenses of moderate power. The reduction is larger for higher-power lenses, according to a chart or the lens manufacturer’s advice.
Some modern calculators have a setting for sulcus placement, and the surgeon should use it.
Optic Capture
In an eye with an intact capsulorhexis that is smaller than the optic, the surgeon can place the haptics in the sulcus and push the optic posteriorly through the rhexis.
This holds the lens in the center, stabilizes it against the capsule, and reduces the risk of pigment dispersion and decentration.
It also moves the optic back toward the plane of the bag, so the power adjustment is smaller.
The method needs a rhexis of the right size and a complete anterior capsule edge.
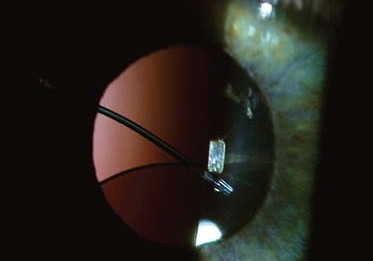
Complications of Sulcus-Fixated IOL
- Uveitis-glaucoma-hyphema syndrome, from the chafing of the lens against the iris and ciliary body (see uveitis-glaucoma-hyphema syndrome)
- Pigment dispersion and raised pressure
- Decentration, tilt, and pupillary capture
- Cystoid macular edema (see Irvine-Gass syndrome)
- Postoperative astigmatism and refractive surprise if the surgeon does not adjust the power
Patients should have follow-up that includes the pressure and the lens position, particularly if there is any pain or reduced vision.
Sulcus-Fixated IOL: Technique Tips
Fill the sulcus with viscoelastic, inspect the capsule rim, and measure the sulcus-to-sulcus distance if possible.
Place the lens gently, with the haptics oriented at the intact capsule support and away from any zonular gaps.
Consider constricting the pupil with an agent, and remove the viscoelastic carefully.
Document the lens model, the position, and the power adjustment, so that later teams know what the surgeon did.
Alternatives When the Capsule Is Insufficient
If the anterior capsule is inadequate, consider scleral fixation, iris fixation, or an anterior chamber lens, depending on the eye (see iris-claw IOL and scleral-fixated intraocular lens).
If the surgeon is not equipped for these procedures, the safest course may be to leave the eye aphakic and plan a secondary lens at a later date. Do not force an unsafe lens into the sulcus.
Avoid placing a lens on a bed of vitreous, and complete the vitrectomy before implanting.
After Surgery
Review the pressure, the lens position, and the anterior chamber reaction at the first visits.
Use topical steroids and nonsteroidal drops according to the case, and consider extended monitoring for macular edema.
If pigment dispersion, raised pressure, or hyphema occurs, consider exchanging the lens or repositioning it, since chronic irritation worsens over time.
Tell patients that a lens in the sulcus should stay stable for life, and that any sudden change in vision, pain, or redness needs urgent examination.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Chang DF, Masket S, Miller KM, et al. Complications of sulcus placement of single-piece acrylic intraocular lenses: recommendations for backup IOL implantation following posterior capsule rupture. J Cataract Refract Surg. 2009;35:1445-1458.
- Wagoner MD, Cox TA, Ariyasu RG, Jacobs DS, Karp CL. Intraocular lens implantation in the absence of capsular support: a report by the American Academy of Ophthalmology. Ophthalmology. 2003;110:840-859.
- Salmon JF. Kanski’s Clinical Ophthalmology: A Systematic Approach. 9th ed. Elsevier; 2020.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 11: Lens and Cataract. AAO; current edition.
Test yourself
A few questions straight from this article.
-
What is the classic indication for a sulcus-fixated IOL?
A sulcus lens needs support from the anterior capsule remnant, so posterior capsule rupture with an intact rhexis is the classic indication. -
Which lens design is appropriate for sulcus fixation after posterior capsule rupture?
A three-piece design with a large overall diameter has stiffer haptics that hold well in the sulcus, and is the recommended backup lens. -
Why must the power of a sulcus-fixated IOL be adjusted from the in-the-bag calculation?
A sulcus lens sits about 0.5 to 1.0 mm in front of its position in the bag, so its effective power rises and the power is reduced to avoid a myopic surprise. -
By how much is a moderate-power IOL commonly reduced when it is placed in the ciliary sulcus?
The reduction is commonly about 0.5 D for moderate-power lenses and larger for higher-power lenses, following a chart, the manufacturer or a calculator's sulcus setting. -
What is optic capture with a sulcus-fixated IOL?
With an intact rhexis smaller than the optic, the optic is pushed posteriorly through it; this centers the lens, reduces pigment dispersion and decentration, and reduces the power adjustment. -
Chafing of a sulcus-fixated IOL against the iris and ciliary body can cause which syndrome?
Chafing causes uveitis-glaucoma-hyphema syndrome; single-piece acrylic lenses in the sulcus have been linked to pigment dispersion, glaucoma, hyphema and decentration. -
If both the anterior and posterior capsule are lost, which IOL fixation should replace a sulcus lens?
When the anterior capsule is also lost or the zonules are very weak, an alternative such as iris, scleral or anterior chamber fixation is needed. -
Capsular support is inadequate for a sulcus IOL and the surgeon cannot perform alternative fixation. What is the safest course?
Leaving the eye aphakic with a planned secondary lens is safer than forcing an unsafe lens into the sulcus or placing it on a bed of vitreous. -
During implantation of a sulcus-fixated IOL, how should the haptics be oriented?
The lens is placed gently with its haptics at the intact capsule support and away from any zonular gaps, after filling the sulcus with viscoelastic. -
Pigment dispersion, raised pressure or hyphema develops after a sulcus-fixated IOL. What should be considered?
Lens exchange or repositioning should be considered because chronic irritation from the lens worsens over time.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.