Persistent hyaloid artery is a fetal vessel remnant that fails to regress and still crosses the vitreous from the optic disc.
Most cases are found by chance during a dilated examination.
However, the same remnant can occasionally bleed and blur vision suddenly.
Embryology of the Hyaloid Artery
The hyaloid artery enters the eye through the optic fissure early in gestation.
It then nourishes the primary vitreous and the tunica vasculosa lentis.
Regression usually begins in mid gestation and is normally complete around birth.
As a result, a vessel that persists after birth reflects arrested involution.
What a Persistent Hyaloid Artery Looks Like
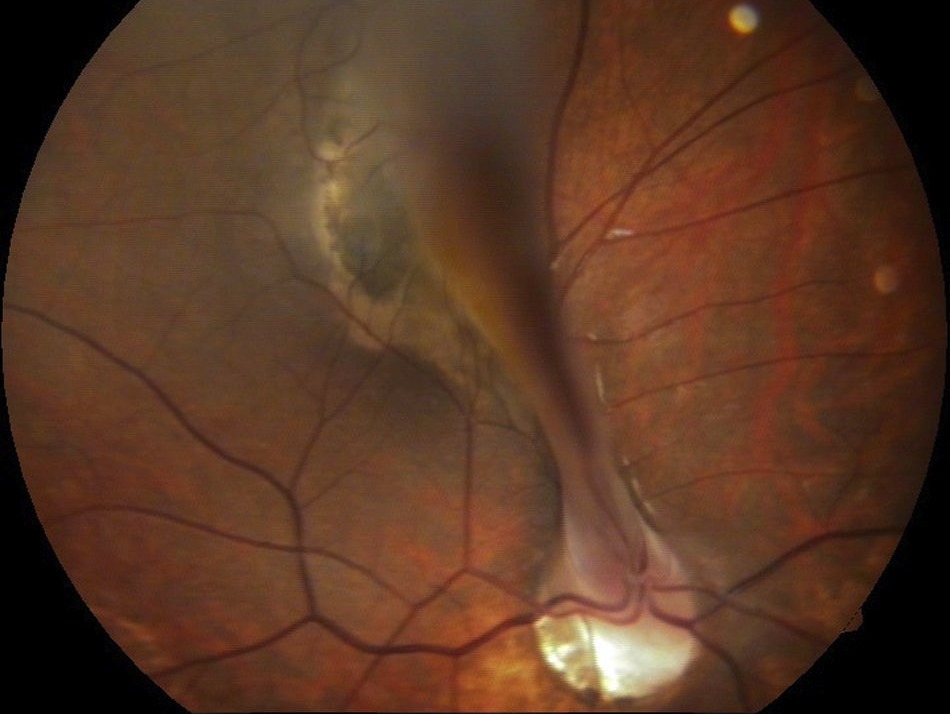
On fundus examination, a fine white or red cord rises from the disc.
It runs forward through the vitreous, often along Cloquet canal.
The stalk may end freely, attach to the posterior lens capsule, or sway with eye movement.
In addition, a patent segment can contain a visible blood column.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteSlit-Lamp Signs of Persistent Hyaloid Artery
With a narrow beam focused behind the lens, the anterior end appears as a translucent strand.
Retroillumination also outlines the strand against the red reflex.
Next, look for a small capsular opacity that often marks its anterior attachment.
Patent Versus Obliterated Stalks
Most remnants are bloodless fibrous cords.
However, a minority remain perfused, and some pulsate with the heartbeat.
Fluorescein angiography confirms flow when the vessel fills from the disc.
Because a perfused vessel can bleed, patency changes how closely you follow the patient.
Persistent Hyaloid Artery Versus Mittendorf Dot
Mittendorf dot is the anterior footprint of the regressed vessel on the posterior capsule.
It is usually a tiny white spot slightly inferonasal to the visual axis.
In contrast, a persistent hyaloid artery has length and extends back into the vitreous.
The two often coexist in the same eye (see Mittendorf dot).
Persistent Hyaloid Artery Versus Bergmeister Papilla
Bergmeister papilla is the posterior remnant sitting on the optic disc.
It appears as a small glial tuft or veil over the cup.
However, it does not travel far into the vitreous.
Therefore, when a cord continues forward from that tuft, describe it as a persistent hyaloid stalk (see Bergmeister papilla).
Persistent Hyaloid Artery and Fetal Vasculature
An isolated stalk sits at the mild end of the persistent fetal vasculature spectrum.
Severe posterior forms add a dense stalk, retinal folds, or traction on the disc and macula.
Anterior forms add a retrolental membrane, cataract, and elongated ciliary processes.
Also, look for microphthalmia in the more severe cases (see persistent fetal vasculature).
When a Persistent Hyaloid Artery Bleeds
Bleeding arises from a patent segment and spreads into the vitreous or in front of the disc.
Minor trauma, vitreous traction, or posterior vitreous detachment may trigger it.
However, other episodes occur without any clear cause.
As a result, a child or young adult may report sudden floaters or blurred vision.
Examining a Fresh Vitreous Hemorrhage
First, document vision, pupils, and the red reflex in both eyes.
Then use B-scan ultrasonography when blood hides the fundus.
A linear echo from the disc toward the lens supports the diagnosis.
Finally, scan the periphery to exclude retinal tears or detachment.
Imaging the Hyaloid Stalk
Optical coherence tomography shows the stalk rising above the disc surface and any traction on nearby retina.
Wide-field photography also documents its course for later comparison.
In addition, angiography separates perfused vessels from avascular remnants.
Differential Diagnosis
- Mittendorf dot or isolated Bergmeister papilla
- Prepapillary vascular loop, which returns to the disc
- Vitreous strand after posterior vitreous detachment
- Retinal fold from retinopathy of prematurity or familial exudative vitreoretinopathy
- Retinoblastoma or Coats disease when leukocoria is present
Managing Persistent Hyaloid Artery
An asymptomatic, avascular stalk needs no treatment.
Therefore, record its appearance and reassure the patient.
Small hemorrhages, for example, often clear with observation alone.
However, dense hemorrhage that fails to clear may need vitrectomy with stalk removal.
Surgery carries risks of cataract, retinal tear, and bleeding from the cut vessel.
Amblyopia Risk in Children
In young children, even temporary media opacity can disrupt visual development.
Therefore, nonclearing hemorrhage reaches the surgical threshold sooner than in adults.
After the blood clears, refraction and patching also protect long-term acuity.
Counseling the Patient
Explain that the strand is a leftover fetal vessel with no link to tumors or systemic disease.
Most people keep normal vision throughout life.
However, ask them to report new floaters, a shadow, or sudden blur promptly.
A patent vessel also warrants periodic dilated review, and imaging after any bleed.
Pitfalls to Avoid
- Do not call every disc strand a hyaloid remnant without tracing its course
- Avoid missing a retinal tear behind a hyaloid hemorrhage
- Never ignore leukocoria in a child with a suspected stalk
- Do not delay surgery when hemorrhage threatens amblyopia


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Goldberg MF. Persistent fetal vasculature (PFV): an integrated interpretation of signs and symptoms associated with persistent hyperplastic primary vitreous (PHPV). Am J Ophthalmol. 1997;124:587-626.
- Reese AB. Persistent hyperplastic primary vitreous. Am J Ophthalmol. 1955;40:317-331.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 12: Retina and Vitreous. San Francisco: AAO; 2023.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 6: Pediatric Ophthalmology and Strabismus. San Francisco: AAO; 2023.
- Salmon JF. Kanski’s Clinical Ophthalmology: A Systematic Approach. 9th ed. Elsevier; 2020.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.