Subretinal fibrosis is a collagen-rich scar beneath the neurosensory retina, often after neovascular or inflammatory injury.
Neovascular AMD is the best known cause, although many other diseases end in the same lesion.
Therefore, the history guides the workup, while foveal involvement shapes the prognosis.
What Subretinal Fibrosis Is
Fibroblast-like cells, glia, RPE cells and extracellular matrix form the scar.
It replaces the normal contact between photoreceptors and RPE.
As a result, the overlying photoreceptors lose function.
How Subretinal Fibrosis Forms
Injury first recruits macrophages, which release growth factors such as transforming growth factor beta.
RPE cells may then undergo epithelial-mesenchymal transition and produce matrix.
Much of this evidence comes from laboratory work, so clinical translation is incomplete.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteCauses Beyond AMD
- Myopic choroidal neovascularization
- Multifocal choroiditis and punctate inner choroidopathy
- Presumed ocular histoplasmosis syndrome
- Vogt-Koyanagi-Harada disease
- Angioid streaks, for example in pseudoxanthoma elasticum
- Diabetic macular edema with heavy hard exudate
- Choroidal rupture and organized submacular hemorrhage
Neovascular AMD and Scarring
A disciform scar marks the end stage of untreated macular neovascularization.
Anti-VEGF therapy preserves vision in many eyes; however, it does not prevent every scar.
In CATT, scar risk rose with classic neovascularization and foveal subretinal hyperreflective material.
Inflammatory Causes of Subretinal Fibrosis
Young patients with bilateral lesions should prompt a search for inflammatory disease.
Multifocal choroiditis scars may bridge into larger fibrotic bands.
Active inflammation then requires systemic evaluation and often immunosuppression.
Subretinal Fibrosis in Diabetic Macular Edema
ETDRS report 23 linked this complication to severe hard exudate at the macula.
Therefore, heavy foveal lipid deserves prompt macular treatment.
Trauma and Detachment
Choroidal rupture may heal with a fibrovascular scar, sometimes after secondary neovascularization.
Long-standing retinal detachment can also develop subretinal bands.
Surgeons then judge whether a band prevents reattachment.
Symptoms and Fundus Signs
Patients report a fixed central blur or scotoma.
Metamorphopsia may also occur when the scar contracts.
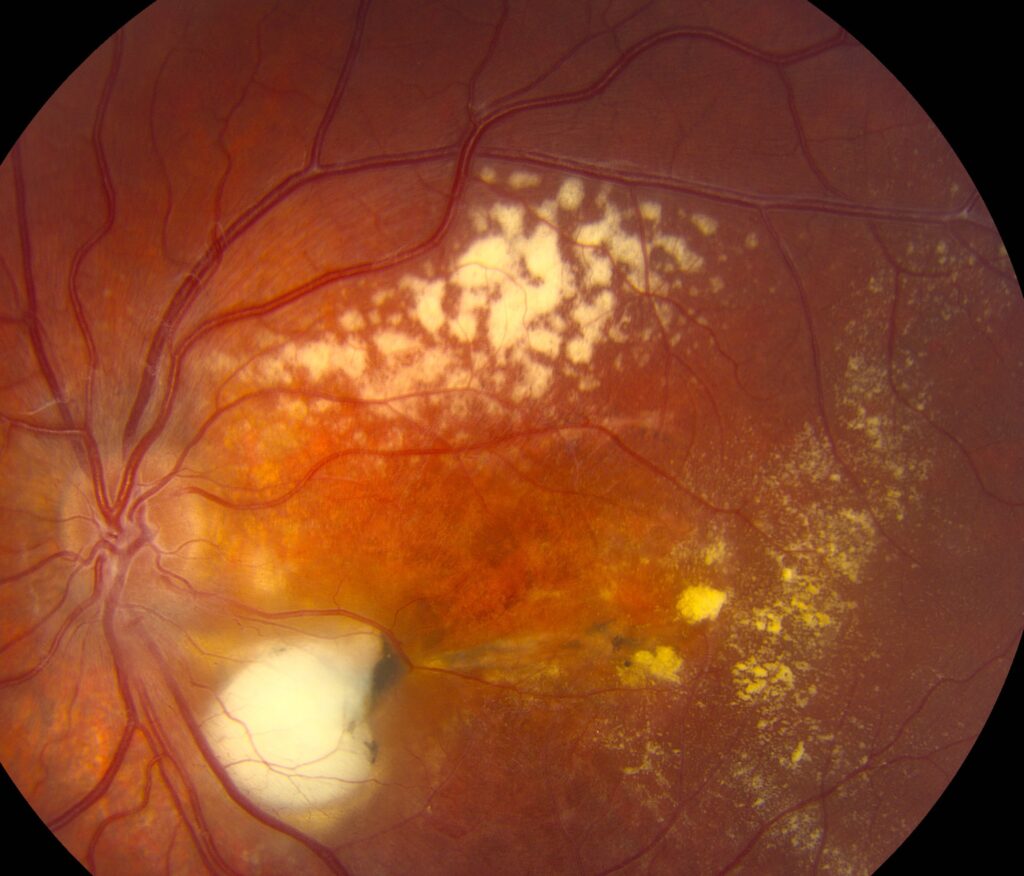
The examiner sees a well-defined white or yellow-white lesion, often with surrounding pigment.
However, hemorrhage, exudate or fluid at the margin suggests active neovascularization.
OCT Appearance of Subretinal Fibrosis
OCT shows compact, sharply demarcated hyperreflective material above or merging with the RPE.
The ellipsoid zone and outer nuclear layer often thin over the lesion.
Outer retinal tubulation nearby usually indicates chronic degeneration.
Scar or Active Material on OCT
Subretinal hyperreflective material is a descriptive term, because it can contain fluid, fibrin, blood or scar.
Fibrosis usually has a stable shape and crisp borders, while exudative material looks fuzzy and changes between visits.
Accompanying subretinal fluid therefore favors activity.
Separately, hyperreflective foci carry a different meaning and are not scar.
Other Imaging Tests
Fluorescein angiography usually shows late staining without expanding leakage.
Fundus autofluorescence often appears dark where RPE is lost.
OCT angiography may reveal flow inside a quiet scar, but flow alone does not mandate treatment.
Prognosis in Subretinal Fibrosis
Location matters most, because a subfoveal scar usually limits central acuity permanently.
In CATT, eyes that developed scar had worse acuity than eyes without it.
Bloch and colleagues also reported poorer acuity in ranibizumab-treated eyes with subfoveal fibrosis.
Treatment of Subretinal Fibrosis
No approved drug reverses established fibrosis.
Treatment targets the driver, for example anti-VEGF for neovascular activity or immunosuppression for inflammation.
Anti-VEGF cannot restore photoreceptors lost beneath a mature scar.
Antifibrotic strategies remain under investigation and are not established care.
Limits of Surgery
The Submacular Surgery Trials showed no overall acuity benefit from removing subfoveal lesions in AMD.
Removal can also damage the adjacent RPE and choriocapillaris.
Selected cases, such as a band blocking reattachment, follow a different logic.
Counseling and Follow-Up
Explain that a scar is healed damage, so lost central vision will not return.
Next, teach monocular self-testing, because either eye may develop new disease.
Low vision rehabilitation can improve daily reading.
At follow-up, compare serial OCT scans for fluid, enlargement or fresh hemorrhage.
Pitfalls to Avoid
- Never label every hyperreflective subretinal lesion as scar
- Assume a white lesion is inactive only after OCT review
- Avoid attributing bilateral scars in a young patient to AMD
- Treating OCT angiography flow alone adds little
- Do not promise visual recovery from anti-VEGF in a mature scar


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Daniel E, Toth CA, Grunwald JE, et al. Risk of scar in the Comparison of Age-related Macular Degeneration Treatments Trials. Ophthalmology. 2014;121:656-666.
- Ishikawa K, Kannan R, Hinton DR. Molecular mechanisms of subretinal fibrosis in age-related macular degeneration. Exp Eye Res. 2016;142:19-25.
- Fong DS, Segal PP, Myers F, et al. Subretinal fibrosis in diabetic macular edema. ETDRS report 23. Arch Ophthalmol. 1997;115:873-877.
- Bloch SB, Lund-Andersen H, Sander B, Larsen M. Subfoveal fibrosis in eyes with neovascular age-related macular degeneration treated with intravitreal ranibizumab. Am J Ophthalmol. 2013;156:116-124.
- Submacular Surgery Trials Research Group. Surgery for subfoveal choroidal neovascularization in age-related macular degeneration: ophthalmic findings. SST report no. 11. Ophthalmology. 2004;111:1967-1980.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.