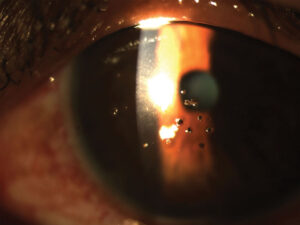
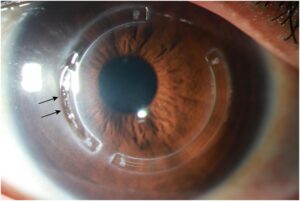
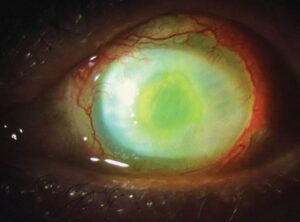
Senile furrow degeneration is a shallow, painless thinning of the peripheral cornea that develops in older adults, usually within an arcus senilis.
It is benign, rarely perforates, and needs no treatment, but it is often mistaken for a more dangerous cause of peripheral thinning.
The skill lies in recognizing its quiet, noninflammatory features.
What Is Senile Furrow Degeneration?
The furrow is a narrow groove in the peripheral corneal stroma, lying in the clear zone between the arcus and the limbus.
It develops slowly in elderly patients, and it often affects both eyes.
The cornea is thinned, but the epithelium is intact, and there is no infiltrate, no vascularization, and no inflammation.
The cause is not clear, and it may reflect a degenerative process with age, perhaps a disturbance of nutrition at the limbus.
It is common enough that clinicians see it often, but few patients know that they have it.
Clinical Features
The patient has no symptoms, and the diagnosis is made on a routine examination.
A slit-lamp beam shows a thin, crescent-shaped groove, usually a millimeter or less in depth, lying inside the arcus.
The groove may be seen around the whole circumference or in a segment, and the thinning can reach a significant fraction of the corneal thickness.
Fluorescein does not stain it, because there is no epithelial defect, and the limbal vessels are normal.
The vision is unaffected unless there is astigmatism from the associated thinning, and this is usually minimal.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteDifferential Diagnosis
- Terrien marginal degeneration: thinning with lipid deposits and superficial vascularization, typically in the superior or inferior periphery, progressing slowly (see Terrien marginal degeneration)
- Mooren ulcer: painful, inflamed, with an overhanging edge and progressive circumferential spread (see Mooren ulcer)
- Peripheral ulcerative keratitis: associated with systemic autoimmune disease, with epithelial defect and inflammation (see peripheral ulcerative keratitis)
- Pellucid marginal degeneration: inferior thinning with ectasia above the band (see pellucid marginal degeneration)
- Staphylococcal marginal keratitis: infiltrates separated from the limbus by a clear interval
The presence of pain, redness, or an epithelial defect points away from senile furrow degeneration.
Evaluation
A careful slit-lamp examination with a thin beam is usually enough.
Anterior segment OCT can measure the depth of the groove and document stability, and corneal topography helps to exclude ectasia.
A history of rheumatoid arthritis or other autoimmune disease should lead to a review for peripheral ulcerative keratitis if there is any inflammation.
Photographs allow comparison at later visits, and a measurement of the minimum thickness is helpful.
Management
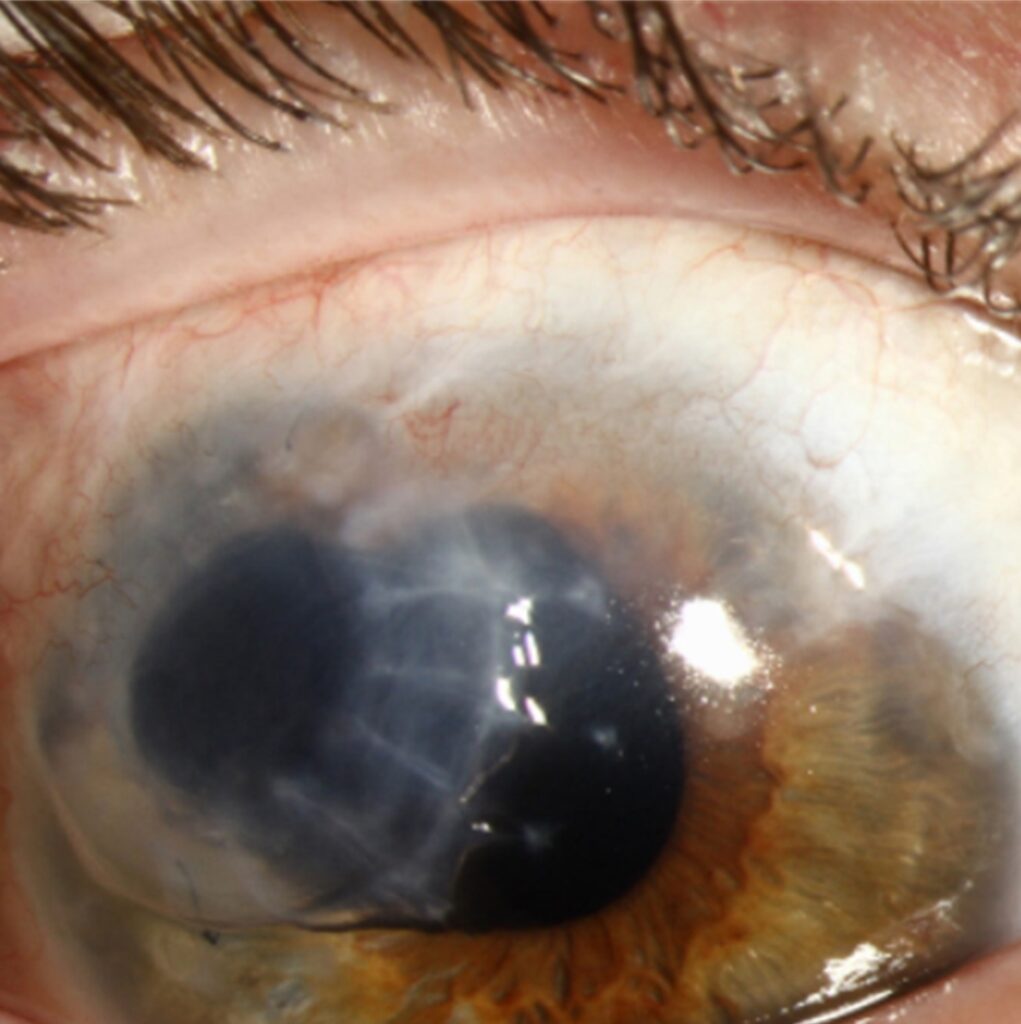
No treatment is required in most cases.
Patients can be reassured that the condition is a benign age-related change and that perforation is very rare.
Lubricants help if there is dry eye, which can make the thinning more noticeable.
Protective eyewear is sensible because the thin area could be more vulnerable to blunt trauma.
Follow-up at the usual interval for the age group is enough, and a change in appearance or the onset of symptoms should prompt a new examination.
Why It Is Worth Recognizing
Peripheral corneal thinning is one of the situations in which a benign and a vision-threatening condition can look alike on a cursory glance.
Recognizing senile furrow degeneration spares the patient an unnecessary autoimmune work-up, a course of steroids, or a referral that causes worry.
Equally, a clinician who dismisses every peripheral thinning as a furrow might miss a case of peripheral ulcerative keratitis.
The simple rule is to look for inflammation and an epithelial defect, and if either is present, the diagnosis is not a senile furrow.
Perioperative Considerations
The thin zone lies near the limbus, where the incisions for cataract surgery are made, and clear corneal incisions placed through or near a furrow may be less stable.
In those cases, surgeons often choose a different site for the incision, and they check the wound for leakage at the end of the operation.
Patients with a furrow who have had cataract surgery should be told to report any sudden change in vision or a feeling that the eye is leaking.
Corneal Imaging
Anterior segment OCT shows a localized loss of stromal thickness with a smooth contour, and the epithelium is continuous across the groove.
Topography may show flattening at the thinned area, but it rarely changes the refractive state enough to matter.
These tools are most useful when a clinician is unsure whether the thinning is stable, and they allow objective follow-up over time.
Photographs and measurements taken at the first visit are the best protection for the clinician, because a later change in a thin area can then be shown objectively.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Mannis MJ, Holland EJ, eds. Cornea. 4th ed. Elsevier; 2017.
- Salmon JF. Kanski’s Clinical Ophthalmology: A Systematic Approach. 9th ed. Elsevier; 2020.
- Krachmer JH, Palay DA. Cornea Atlas. 3rd ed. Elsevier; 2014.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 8: External Disease and Cornea. AAO; current edition.
Test yourself
A few questions straight from this article.
-
Where does the groove of senile corneal furrow degeneration lie?
The furrow is a narrow groove in the peripheral stroma lying in the clear zone between the arcus senilis and the limbus. -
Which pair of findings points away from senile corneal furrow degeneration?
The simple rule is to look for inflammation and an epithelial defect; if either is present the diagnosis is not a senile furrow. -
What is the typical symptom profile of senile corneal furrow degeneration?
The patient has no symptoms and the diagnosis is made on a routine slit-lamp examination of an otherwise quiet eye. -
Which peripheral corneal thinning shows lipid deposits and superficial vascularization?
Terrien marginal degeneration produces thinning with lipid deposits and superficial vascularization, typically in the superior or inferior periphery. -
What does anterior segment OCT show in senile corneal furrow degeneration?
Anterior segment OCT shows a localized loss of stromal thickness with a smooth contour, and the epithelium runs continuously across the groove. -
Which cause of peripheral corneal thinning is linked to systemic autoimmune disease?
Peripheral ulcerative keratitis is associated with systemic autoimmune disease and shows an epithelial defect with inflammation, so any inflammation warrants review. -
How is senile corneal furrow degeneration managed in most cases?
No treatment is required in most cases; patients are reassured that it is a benign age-related change, with lubricants added if dry eye coexists. -
In which patients does senile corneal furrow degeneration develop, and in what pattern?
The furrow develops slowly in elderly patients and often affects both eyes, which is one reason it is seen so frequently in clinic. -
What is the state of the limbal vessels in senile corneal furrow degeneration?
The limbal vessels are normal and there is no vascularization or infiltrate, which separates the furrow from Terrien marginal degeneration. -
What is the risk of perforation in senile corneal furrow degeneration?
The condition is benign and rarely perforates, so patients can be reassured and followed at the usual interval for their age group.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.