Geographic ulcer is an enlarged form of herpes simplex epithelial keratitis with a broad, scalloped corneal defect.
It usually develops from a dendrite that keeps expanding across the epithelium.
Because live virus drives the lesion, treatment centers on antivirals, while topical steroids can worsen it.
What a Geographic Ulcer Is
The name describes the shape, because the irregular margins resemble the outline of a map.
Clinicians also use the term amoeboid ulcer for the same appearance.
The defect mainly involves the epithelium, although the anterior stroma may show mild haze.
How a Dendrite Becomes a Geographic Ulcer
Herpes simplex virus replicates within corneal epithelial cells and spreads to neighboring cells.
As infected cells die, a linear branching defect forms.
If replication continues, the branches widen and merge into one larger ulcer.
Therefore, the edge often retains dendritic extensions that reveal the origin of the lesion.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteFactors That Favor Enlargement
Topical corticosteroid use during active epithelial infection is the classic association.
In addition, systemic immunosuppression and atopic disease may allow more extensive infection.
Delayed diagnosis can also give the virus more time to spread.
Symptoms Patients Report
Patients usually describe redness, tearing, photophobia and foreign body sensation.
However, reduced corneal sensation can blunt pain, so mild symptoms may accompany a large defect.
Vision falls when the ulcer crosses the visual axis.
Slit Lamp Signs of Geographic Ulcer
First, test corneal sensation before instilling any anesthetic.
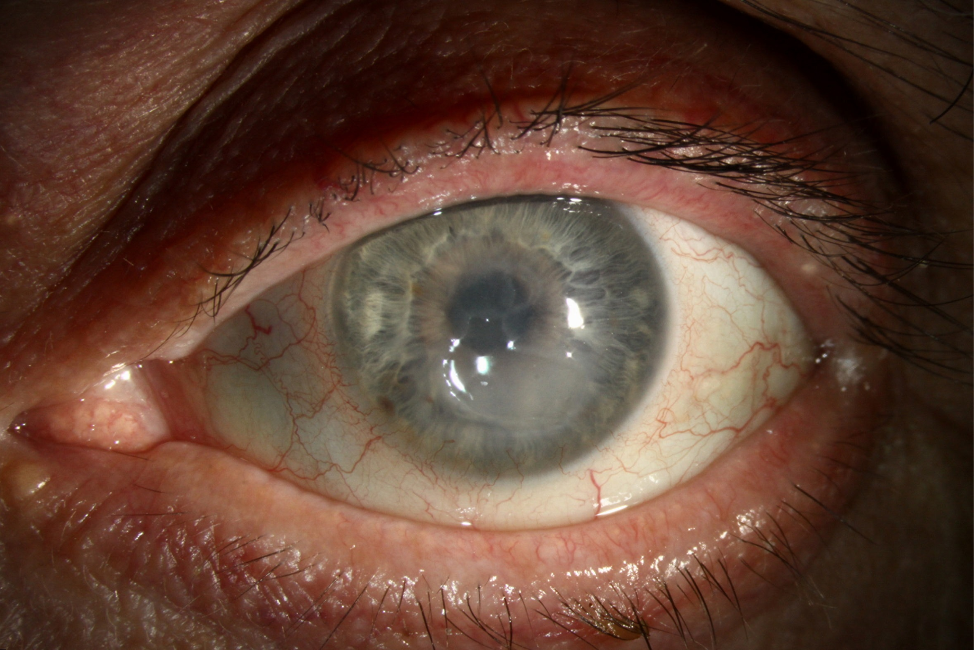
Then look for a large defect with scalloped borders and swollen, grayish margins.
Fluorescein stains the ulcer bed, while lissamine green highlights damaged cells at the edge.
Next, search the border for dendritic tails with terminal bulbs.
Finally, examine the stroma and anterior chamber for coexisting herpetic inflammation.
Confirming the Diagnosis
Diagnosis usually rests on the clinical appearance and history.
However, PCR or viral culture can help when the lesion looks atypical or responds poorly.
Sample the ulcer margin, because infected epithelial cells concentrate there.
Geographic Ulcer vs Neurotrophic Ulcer
A neurotrophic ulcer tends to have smooth, rolled margins and an oval shape, without dendritic tails.
Both entities can occur in one eye, so the distinction changes management.
For example, prolonged antivirals can further damage a neurotrophic surface.
Zoster pseudodendrites, by contrast, look raised and stain poorly (see herpes zoster ophthalmicus).
Antiviral Treatment of Geographic Ulcer
A Cochrane review supports topical antivirals for faster healing of herpetic epithelial keratitis.
For example, ganciclovir 0.15% gel is used five times daily until healing, then three times daily for one week.
Oral options in the AAO guideline include acyclovir 400 mg five times daily and valacyclovir 500 mg two or three times daily.
Also adjust oral doses for renal impairment.
However, antivirals cannot restore lost corneal nerve function.
Debridement as an Adjunct
Gentle debridement removes infected cells and may lower the viral load.
Therefore, some clinicians add it to antiviral treatment.
It does not prevent recurrence, so it should not replace antiviral therapy.
Steroid Risk in Geographic Ulcer
Topical steroids can enlarge the defect and delay healing while the virus is actively replicating.
Therefore, review every drop the patient uses, including old bottles and combination products.
The benefit shown in the HEDS stromal trial applied to stromal keratitis under antiviral cover (see herpes simplex keratitis).
When Stromal Disease Coexists
Most clinicians control the epithelial infection first, then consider cautious steroids once the surface heals.
Severe stromal thinning or infiltrate calls for urgent review (see stromal corneal ulcers).
Meanwhile, consider bacterial or fungal superinfection before attributing the infiltrate to herpes.
Follow-Up After Geographic Ulcer
Re-examine the patient within a few days and record the defect size with fluorescein.
If healing stalls, consider drug toxicity, neurotrophic disease, superinfection or antiviral resistance.
After closure, check sensation, stromal scarring and intraocular pressure.
Preventing Recurrence After Geographic Ulcer
HEDS found that oral acyclovir 400 mg twice daily for 12 months reduced recurrent ocular herpes from 32% to 19%.
Therefore, discuss prophylaxis based on recurrence history, visual risk and patient preference.
Counseling the Patient
Explain that the virus remains latent after the ulcer heals, so recurrence remains possible.
Next, ask patients to avoid leftover steroid drops and to report new redness or blur promptly.
Pitfalls to Avoid
- Do not start steroids for an undiagnosed red eye with an epithelial defect
- Do not continue topical antivirals indefinitely when the surface looks toxic
- Never skip corneal sensation testing


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Holland EJ, Schwartz GS. Classification of herpes simplex virus keratitis. Cornea. 1999;18:144-154.
- Wilhelmus KR. Antiviral treatment and other therapeutic interventions for herpes simplex virus epithelial keratitis. Cochrane Database Syst Rev. 2015;1:CD002898.
- White ML, Chodosh J. Herpes simplex virus keratitis: a treatment guideline. American Academy of Ophthalmology. 2014.
- Wilhelmus KR, Gee L, Hauck WW, et al. Herpetic Eye Disease Study: a controlled trial of topical corticosteroids for herpes simplex stromal keratitis. Ophthalmology. 1994;101:1883-1895.
- Herpetic Eye Disease Study Group. Acyclovir for the prevention of recurrent herpes simplex virus eye disease. N Engl J Med. 1998;339:300-306.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.