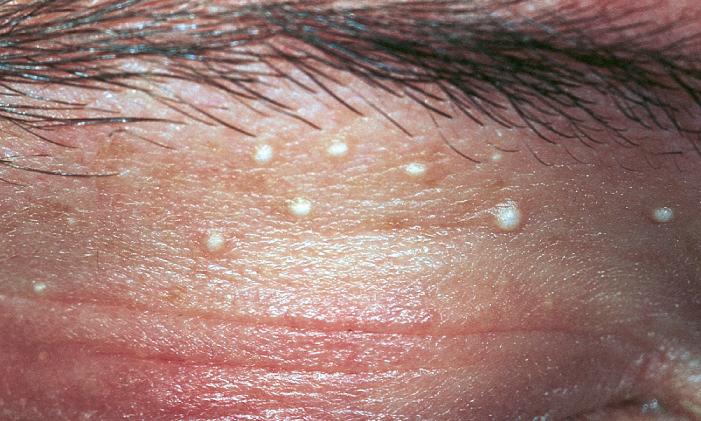
Eyelid milia are small, superficial keratin cysts that appear as firm white bumps on the lid skin.
They are benign and painless, and most patients seek care for appearance.
However, several lid lesions look similar, so careful examination comes first.
What Eyelid Milia Are
A milium is a tiny epidermal inclusion cyst filled with keratin.
Primary milia arise from the infundibulum of vellus hair follicles.
In contrast, secondary milia form after skin injury blocks eccrine ducts or follicles.
Histology also shows a thin squamous lining around laminated keratin.
Who Develops Eyelid Milia
Many newborns have facial milia, and these usually clear within weeks.
In adults, the periorbital skin and cheeks are common sites.
Women present more often, perhaps because cosmetic concern brings them in.
Also, heavy occlusive eye creams may contribute, although evidence is limited.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteCauses of Secondary Milia
First, ask about previous skin trauma, because secondary milia follow injury.
- Burns, dermabrasion or ablative laser resurfacing
- Also blistering diseases such as porphyria cutanea tarda or bullous pemphigoid
- Then long-term topical corticosteroid use
- In addition, prior eyelid surgery or radiation
What the Patient Reports
Patients usually describe a few tiny white spots present for months.
However, the lesions do not itch, hurt or discharge.
Some have tried squeezing them, and therefore arrive with redness or small scabs.
Exam Signs of Eyelid Milia
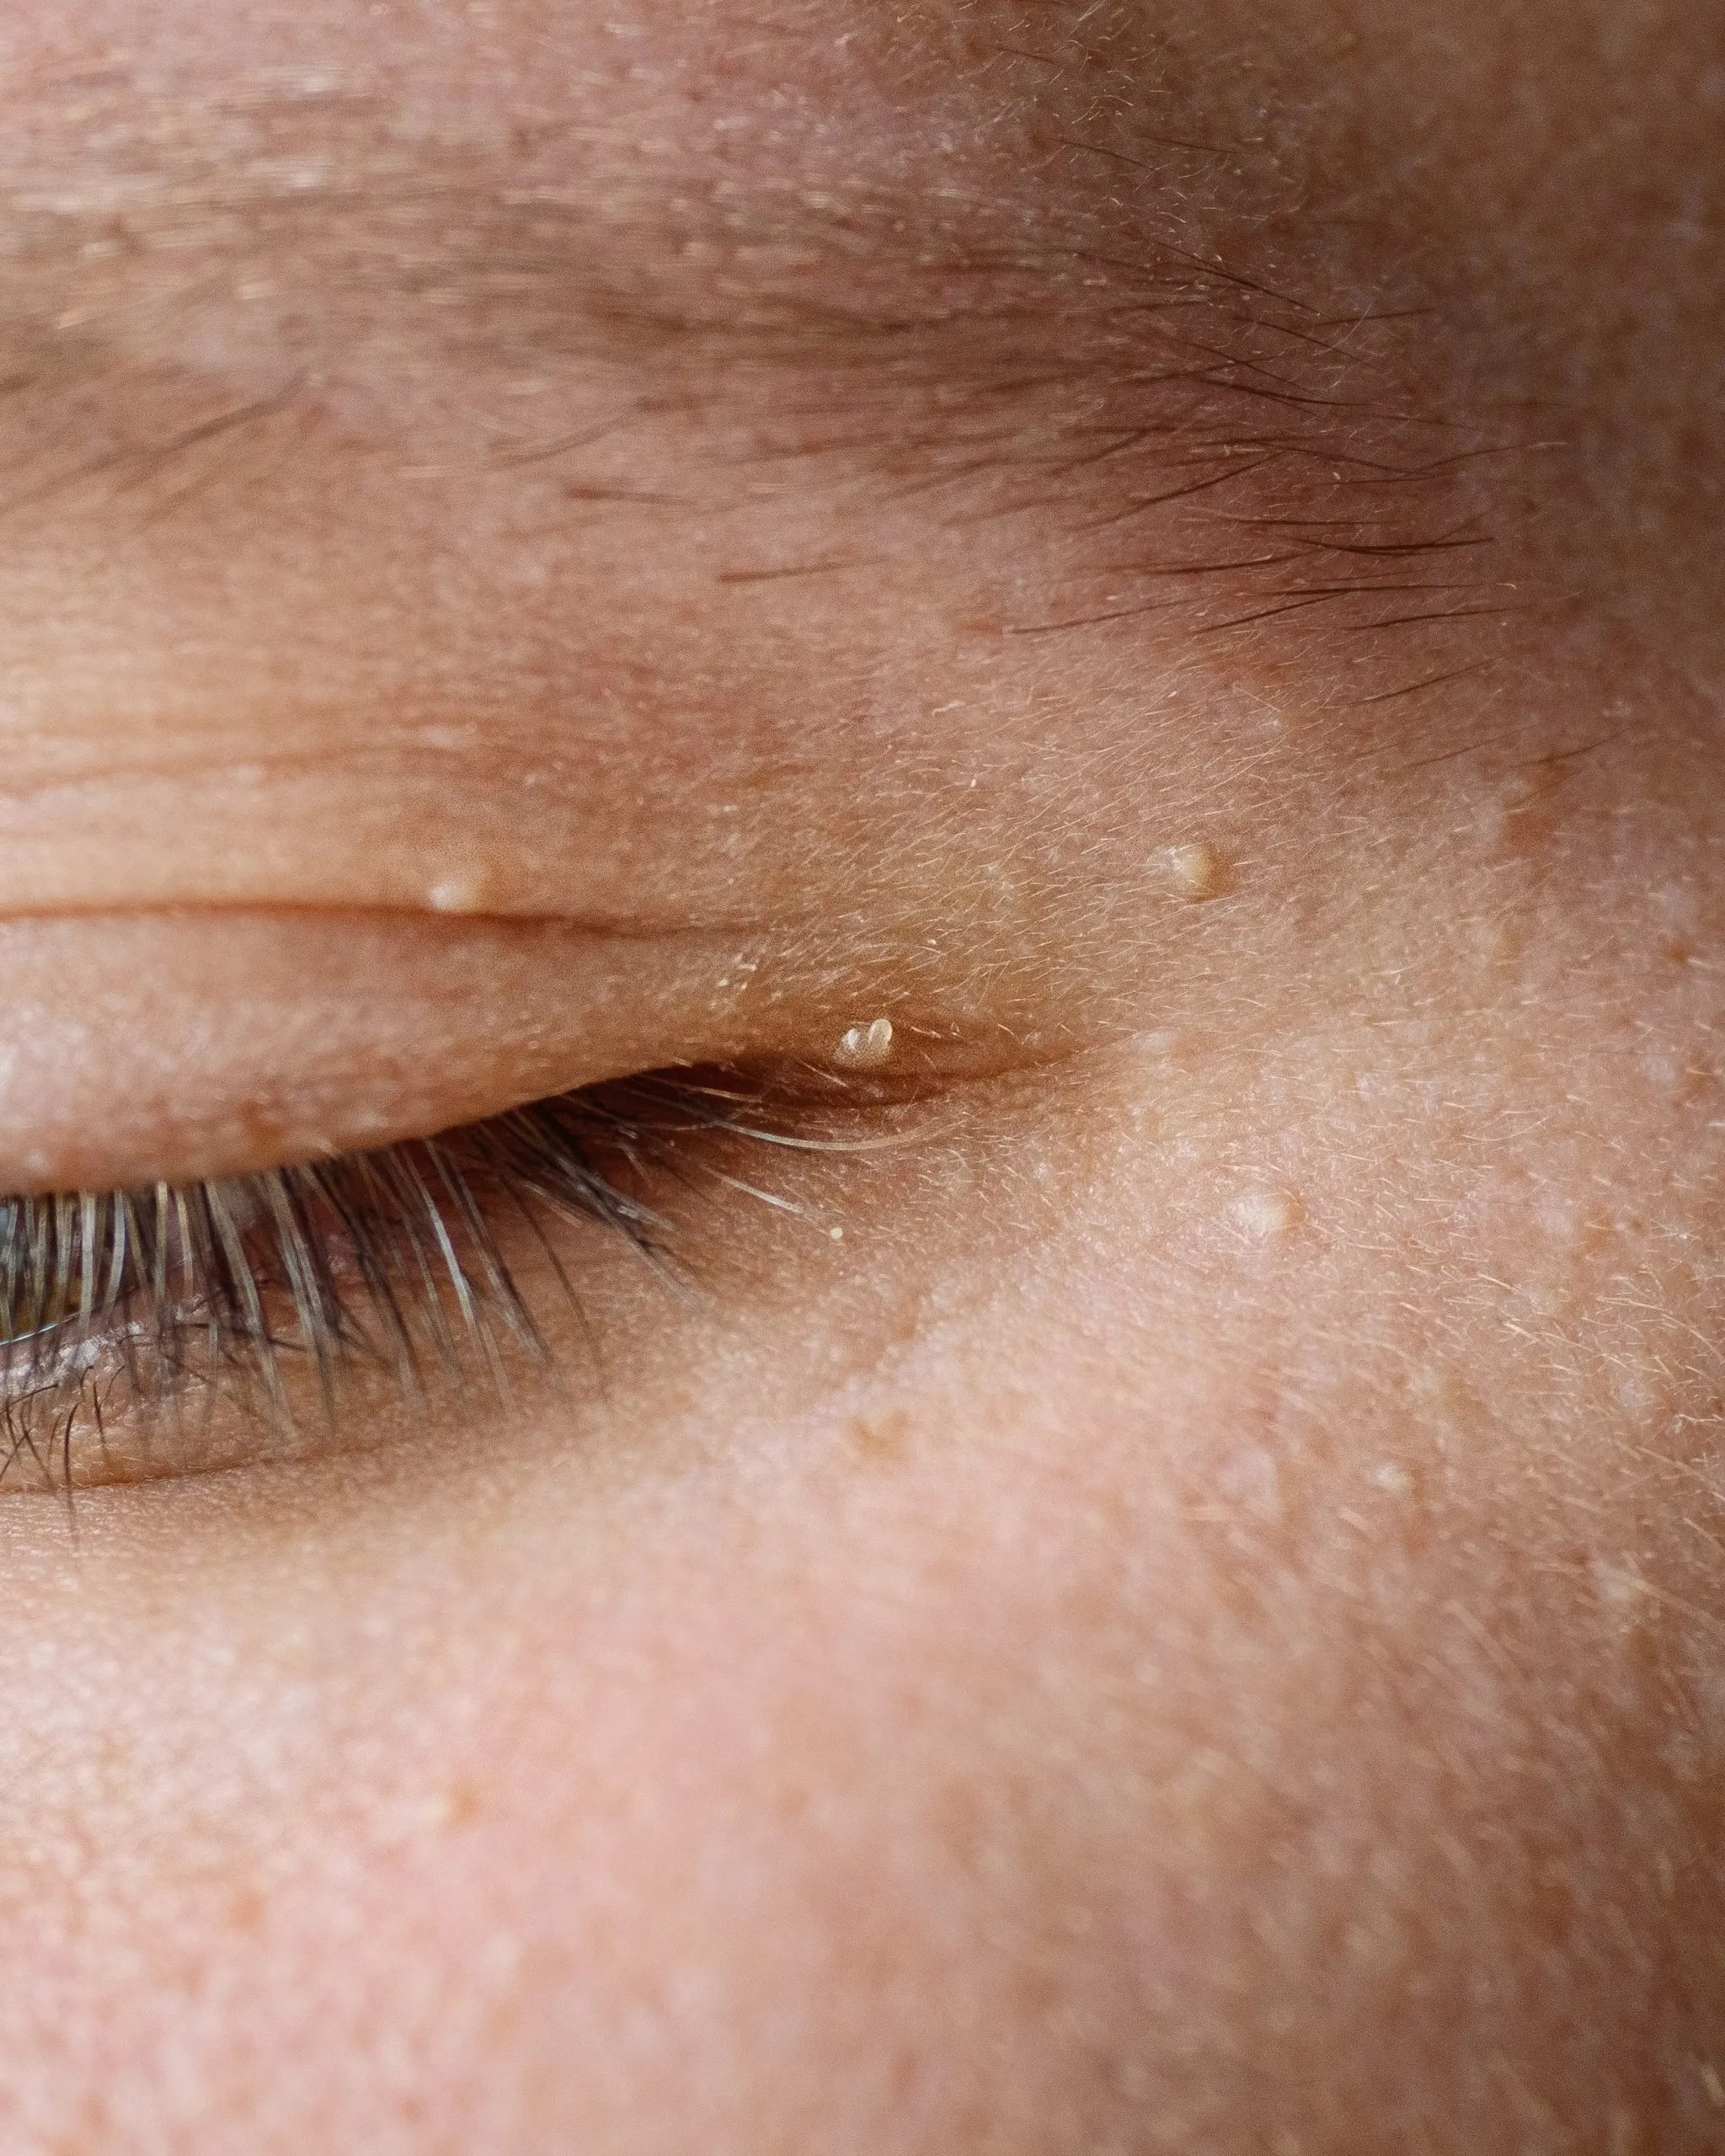
At the slit lamp, each milium is a smooth, dome-shaped papule of 1 to 2 mm.
The color is pearly white or pale yellow.
Its surface is intact, with no punctum and no umbilication.
On palpation it feels firm, like a grain of sand.
Finally, it does not transilluminate.
Eyelid Milia at the Lid Margin
Milia can sit near the lash line on the anterior lamella.
Here, consider cysts of Zeis, which arise from sebaceous glands attached to lashes.
Also inspect the meibomian orifices, because inspissated secretions can mimic a white bump.
In addition, a chalazion lies deeper in the tarsus and feels rubbery.
Milia Versus Hidrocystoma
Hidrocystomas are fluid-filled cysts of sweat gland origin (see eyelid hidrocystoma).
They look translucent or bluish, and they transilluminate with a penlight.
In contrast, milia are opaque and solid white.
Also, apocrine types often sit at the margin, while eccrine types may multiply in hot weather.
Milia Versus Molluscum Contagiosum
Molluscum lesions are waxy, flesh-colored papules with a central umbilication.
However, they can shed virus into the tear film and cause chronic follicular conjunctivitis (see molluscum contagiosum).
Therefore, evert the lids and examine the conjunctiva in any patient with lid papules.
Milia, by contrast, never inflame the conjunctiva.
Other Differentials for Eyelid Milia
- Syringoma: small skin-colored papules, mostly on lower lids
- Also xanthelasma: soft yellow plaques, often medial
- Then sebaceous hyperplasia: yellow lobulated papule with a central dell
- However, basal cell carcinoma is a pearly nodule with telangiectasia that grows or bleeds
When Eyelid Milia Need a Biopsy
Typical milia need no tissue diagnosis.
However, a lone lesion that grows, ulcerates, bleeds or causes lash loss needs biopsy.
Also, plaque-like clusters (milia en plaque) deserve histology and dermatology review.
Counseling the Patient
First, explain that milia are harmless and do not turn into cancer.
Many fade slowly, especially in children.
However, warn against squeezing at home, because this risks infection, scarring and eye injury.
Also, mention that new lesions may appear later.
Safe Removal of Eyelid Milia
Extraction is quick and well tolerated in the clinic.
First, clean the skin with dilute povidone-iodine.
Next, nick the cyst roof with a fine sterile needle or a No. 11 blade.
Then express the keratin core with two cotton-tipped applicators or a comedone extractor.
Local anesthetic is rarely needed.
Protecting the Globe
First, position the patient supine with the head supported.
Then hold the needle tangential to the skin and point it away from the eye.
For margin lesions, a lid plate or chalazion clamp stabilizes the tissue.
In addition, ask the patient to fixate away from the lesion.
Other Treatment Options
Topical retinoids can loosen superficial milia; however, they irritate periocular skin.
Therefore, keep them away from the lid margin.
Electrodesiccation and ablative laser suit numerous lesions, but they can cause scarring or hypopigmentation.
Aftercare and Recurrence
First, apply a bland ointment for a few days.
Most sites heal within a week without a mark.
However, new milia can appear if the trigger persists, so review steroid creams and heavy cosmetics.
Pitfalls to Avoid
- Do not label a translucent cyst a milium before transilluminating it
- Also, do not miss molluscum in chronic follicular conjunctivitis
- Therefore, never point a blade toward the globe
- Then biopsy any growing pearly nodule with telangiectasia
- However, avoid retinoids on the lid margin


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Berk DR, Bayliss SJ. Milia: a review and classification. J Am Acad Dermatol. 2008;59:1050-1063.
- Sarabi K, Khachemoune A. Hidrocystomas: a brief review. MedGenMed. 2006;8(3):57.
- Chen X, Anstey AV, Bugert JJ. Molluscum contagiosum virus infection. Lancet Infect Dis. 2013;13:877-888.
- Pe’er J. Pathology of eyelid tumors. Indian J Ophthalmol. 2016;64:177-190.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 7: Oculofacial Plastic and Orbital Surgery. San Francisco: AAO; 2023.
- Bowling B. Kanski’s Clinical Ophthalmology: A Systematic Approach. 8th ed. Edinburgh: Elsevier; 2016.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.