
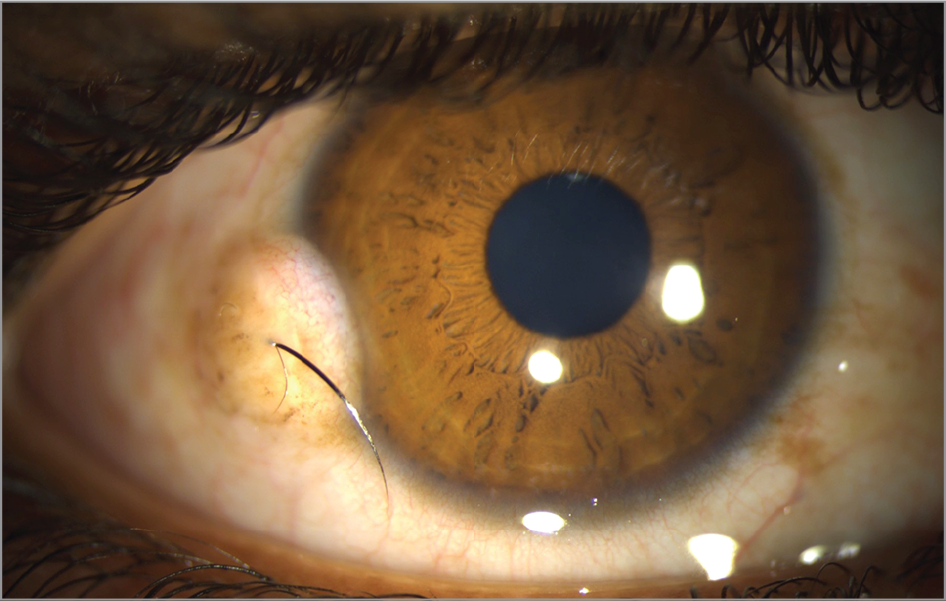
A limbal dermoid is a congenital lesion present from birth, a choristoma, meaning tissue that is histologically normal but located somewhere it does not belong, in this case composed of tissue elements such as skin adnexal structures, hair follicles, and sometimes fat, situated at the corneoscleral limbus rather than in its normal location.
What a Choristoma Actually Is
Unlike a hamartoma, which represents disorganized proliferation of tissue that does belong in that location, a choristoma like the limbal dermoid consists of tissue entirely normal in its own right, skin and its associated adnexal structures, simply present in an abnormal location, the corneoscleral limbus, as a result of an error in embryonic tissue development rather than any later acquired or degenerative process.
Clinical Appearance
- A smooth, round or oval, whitish or yellowish, elevated mass typically located at or straddling the inferotemporal limbus, this being the most classically described and most common location
- Surface hairs are sometimes visible growing from the lesion, a distinctive finding reflecting the skin-derived tissue elements this choristoma contains
- Size and degree of corneal involvement vary considerably, ranging from small, limited lesions to larger dermoids extending more substantially onto the corneal surface
- Most commonly unilateral, though bilateral involvement can occur, particularly in the context of an associated systemic condition
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteAssociated Systemic Conditions
Limbal dermoid has a well-recognized association with Goldenhar syndrome (oculoauriculovertebral spectrum), which also includes preauricular skin tags, vertebral anomalies, and other craniofacial features, and identification of a limbal dermoid, particularly when other suggestive craniofacial or vertebral findings are present, should prompt appropriate evaluation for this and related associated conditions.
Why Size and Location Drive Management Decisions
The central clinical concern with limbal dermoid is not typically the lesion’s oncologic behavior, which is benign and essentially always stable rather than progressive, but rather the astigmatism it can induce, given its location straddling the cornea, and the associated risk of amblyopia this astigmatism can produce if the lesion is large and left unaddressed during the critical period of visual development in early childhood.
Diagnostic Evaluation
- Slit-lamp examination characterizing the lesion’s size, exact location, and degree of corneal involvement
- Refraction and assessment for astigmatism, given the central role this plays in the amblyopia risk this condition presents in young children
- Examination and, when suggestive features are present, appropriate referral for evaluation of associated systemic conditions, particularly Goldenhar syndrome
- Monitoring visual development closely in young children with this diagnosis, given the amblyopia risk associated with significant lesion-induced astigmatism
Management
Observation for Small, Visually Insignificant Lesions
Small limbal dermoids without significant associated astigmatism or visual impact can be managed with observation, given their benign, stable natural history, with ongoing monitoring of refractive status particularly important during early childhood.
Addressing Astigmatism and Amblyopia Risk
Appropriate refractive correction and, when indicated, amblyopia treatment are important for children with dermoid-associated astigmatism, following standard pediatric amblyopia management principles adapted to this specific underlying cause.
Surgical Excision
Surgical excision, generally via superficial keratectomy, is considered for larger lesions, those causing significant astigmatism or amblyopia risk, or for cosmetic concerns, with the surgical approach tailored to the depth and extent of corneal involvement, and with appropriate counseling that excision, while addressing the visible lesion, does not necessarily reverse astigmatism that has already become established, particularly if amblyopia has already developed.
What the work-up involves
In a child with a limbal dermoid, look for preauricular tags, ear anomalies, a small jaw, vertebral anomalies, and hearing problems, since these suggest Goldenhar syndrome. A pediatric assessment, hearing test, and sometimes cardiac and renal evaluation are advised. Check for epibulbar lipodermoids and eyelid colobomas, which are also part of the spectrum.
Surgical details
Excision by superficial lamellar keratectomy removes the visible lesion, but deeper lesions may require a patch graft or lamellar keratoplasty. A rim of scar and some residual astigmatism are common after surgery, and the surgeon should explain that the cosmetic result may be imperfect. Postoperative drops and monitoring are needed.
Amblyopia care
Refract the child every few months in the first years, correct astigmatism, and patch if amblyopia develops. Parents should understand that the glasses and patching are as important as the surgery.
Prognosis
Limbal dermoid, once identified, generally carries a good overall prognosis, with the primary management focus centered on monitoring and addressing any associated astigmatism to prevent amblyopia during the critical early childhood period of visual development.
Early identification and, when needed, prompt, appropriate refractive and amblyopia management, rather than surgical excision as a default first response, generally offers the best approach to preserving visual function in affected children, reserving surgery for cases where the lesion’s size, visual impact, or associated concerns specifically warrant it.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Mansour AM, Barber JC, Reinecke RD, Wang FM. Ocular choristomas. Surv Ophthalmol. 1989;33:339-358.
- Pirouzian A. Management of pediatric corneal limbal dermoids. Clin Ophthalmol. 2013;7:607-614.
- Baum JL, Feingold M. Ocular aspects of Goldenhar’s syndrome. Am J Ophthalmol. 1973;75:250-257.
- Panton RW, Sugar J. Excision of limbal dermoids. Ophthalmic Surg. 1991;22:85-89.
