CASE REPORT
A 42-year-old male presented to the ophthalmology clinic with chief complaints of blurred vision and floaters in both eyes.
His medical history revealed no significant systemic illnesses, but his occupational history included frequent exposure to dust and soil.
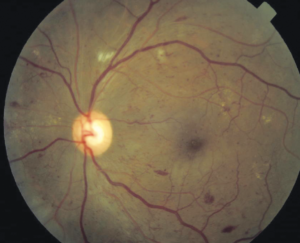
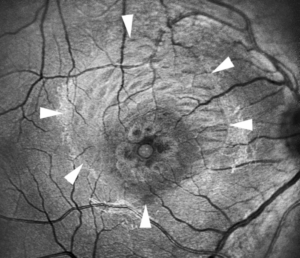
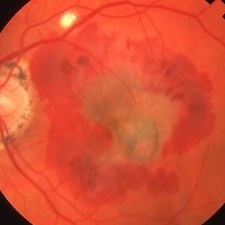
Examination findings indicated visual acuity of 20/40 in the right eye and 20/50 in the left eye, mild conjunctival injection in both eyes, clear corneas with no evidence of active inflammation, and characteristic fundus findings such as bilateral peripapillary atrophy and multiple chorioretinal scars scattered throughout the macular region.
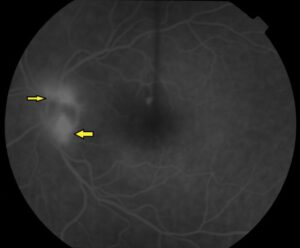
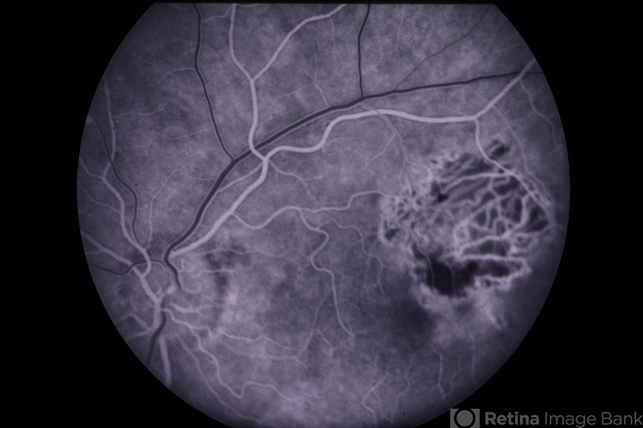
Fluorescein angiography confirmed the absence of active leakage or neovascularization.
Diagnostic testing included documented chorioretinal scars through fundus photography, a negative chest X-ray for acute pulmonary histoplasmosis infection, and the absence of histopathological examination due to the patient’s asymptomatic systemic status.
Based on these findings, the patient was diagnosed with Presumed Ocular Histoplasmosis Syndrome (POHS).
DISEASE entity
Presumed ocular histoplasmosis syndrome (POHS) occurs secondary to infection with the yeast form of Histoplasma capsulatum.
The disease is characterized by atrophic chorioretinal scars, peripapillary atrophy (PPA), and the absence of vitritis. POHS is asymptomatic until choroidal neovascularization (CNV) or sequelae such as disciform scars develop.
There is considerable controversy over the cause of Presumed ocular histoplasmosis syndrome (POHS). Classically, POHS is caused by infection with the yeast form of H. capsulatum, which is a dimorphic fungus that lives in the soil.
It is endemic to states that contain the Ohio and Mississippi river valleys. Although distributed worldwide, POHS has only been reported in a few non-U.S. countries including Mexico, India, the United Kingdom, and the Netherlands.
It is carried on the feathers of chickens, pigeons, and blackbirds as well as in the droppings from infected bats.
Infection in humans occurs after inhalation of the spore or conidia form, classically associated with cave exploration and exposure to infected bats as well as birds, followed by hematogenous spread of the organism to the choroid.
The link between H. capsulatum and POHS comes from epidemiological studies where POHS was linked to a positive histoplasmin skin antigen test.
However, a study in the Netherlands found that all patients with clinical POHS were histoplasmin skin antigen test negative.
POHS is different from “Disseminated Histoplasmosis” which is the exudative/productive H. capsulatum infection of ocular tissues, seen in immunocompromised adults or infants.
Since Presumed ocular histoplasmosis syndrome (POHS) is linked to HLA haplotypes DRw2 and B7, some hypothesize that it could also represent an autoimmune inflammatory reaction triggered by certain organisms, including H. capsulatum.
HLA DRw2 has been found in higher concentrations in patients with disciform and peripheral scars compared to the normal population.
Similarly, nearly 78% of patients with clinical POHS and macular disciform scars in at least one eye are positive for HLA-B7. The absence of vitritis in the clinical criteria for POHS also supports an inflammatory rather than an active infectious etiology.

The diagnosis of Presumed ocular histoplasmosis syndrome (POHS) is based upon a fundoscopic exam for the four cardinal features and fluorescein angiography for the characterization of CNV.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteSigns of Presumed ocular histoplasmosis syndrome (POHS)
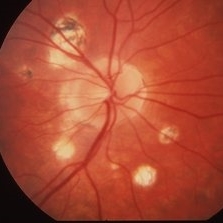
Three characteristic findings of POHS are typically found on fundoscopic exams: multiple white atrophic chorioretinal scars or histo spots, PPA, and the absence of vitritis.
These findings may or may not be associated with CNV, which often appears as greenish-yellow subretinal discoloration with a surrounding pigmented ring at the macula.
Confluent atrophic chorioretinal scars in a linear or curvilinear pattern of variable length, width, and pigmentation can be found in the mid-periphery in approximately 5% of patients. In advanced cases, CNV can progress to a disciform scar with subretinal fibrovascular tissue. POHS changes can be found bilaterally in up to 60% of cases.
Presumed ocular histoplasmosis syndrome (POHS) Symptoms
Prior to CNV development, Presumed ocular histoplasmosis syndrome (POHS) was asymptomatic. POHS often presents with the classic symptoms of CNV, including painless vision loss, metamorphopsia, blurred central vision, and central or paracentral scotomas.
Presumed ocular histoplasmosis syndrome (POHS) MANAGEMENT
Presumed ocular histoplasmosis syndrome (POHS) without CNV is observed and counseling for monitoring of CNV. Because POHS is not truly an infectious process, early attempts at anti-fungal therapy yielded no benefit.
Treatment is generally guided toward early detection of CNV via Amsler grid screening and routine dilated fundoscopic exams. Once CNV develops, the approach is similar to the treatment of AMD.
Medical therapy
The Macular Photocoagulation Study (MPS) evaluated laser photocoagulation forextrafoveal, juxtafoveal, and peripapillary CNV.
The MPS found that laser photocoagulation decreased the risk of severe vision loss from 44% to 9% at 5-year follow-up for extrafoveal CNV and 28% to 12% for juxtafoveal CNV.
The major complication of this treatment is the permanent scotoma caused by laser photocoagulation, limiting its utility in subfoveal CNV.
This concern was addressed by Verteporfin for the Ocular Histoplasmosis trial that evaluated photodynamic therapy (PDT) for subfoveal CNV.
The authors found that 45% of patients had improved vision, while 9% suffered severe vision loss after 2 years of follow-up.
With the advent of using anti-vascular endothelial growth factor (VEGF) therapy for AMD, many case reports and case series have investigated anti-VEGF therapy for CNV from POHS.
A large retrospective study found that average visual acuity (VA) improved from 20/53 to 20/26 in 54 eyes treated over a 26-month period with either intravitreal bevacizumab or ranibizumab.

The average number of injections required was 4.5 per year of treatment. OCT-A has been shown to be very effective for tracking the efficacy of anti-VEGF therapy, similar to neovascular AMD, detecting changes in vascular flow suggestive of CNV where FA and SD-OCT showed stability.
Multiple studies have looked at the effect of bevacizumab alone in CNV for patients with POHS. One such case series retrospectively evaluated VA in 28 eyes with subfoveal or juxtafoveal POHS-related CNV treated with intravitreal bevacizumab.
Of these eyes, 16 had PDT failures, 5 received bevacizumab within two weeks of PDT (combination treatment), and 7 were PDT-naive.
Seventy-one percent of patients showed VA improvement, while 14% stabilized and the remaining 14% had decreased VA after a mean follow-up of 11 weeks and an average of 1.8 injections.
Of note, the 14% with decreased vision were PDT failures with progressive vision loss. A separate study evaluated the effect of intravitreal bevacizumab in 24 treatment-naive eyes with subfoveal or juxtafoveal CNVs secondary to POHS.
After following patients for 12 months, VA was found to improve from 0.86±0.35 to 0.34±0.33 logMAR units, with an average of 6.8 injections per year. Over 50% of eyes had a final VA of 20/40 or better.
With regards to the efficacy of intravitreal ranibizumab, a randomized study investigated the benefit of monthly ranibizumab injections versus three monthly doses followed by “as needed” injections in patients with non-AMD-related CNV. Of the 30 enrolled patients, 9 had a diagnosis of POHS.
Although the study did not stratify results based on diagnosis, it reported a gain of 15 or more letters in VA at 6 and 12 months for 66.7% of patients in the monthly injection group and similar gains in 64.3% and 57.1% of patients in the as-needed group at 6 and 12 months, respectively.
A retrospective study investigated the effect of intravitreal triamcinolone for CNV resulting from POHS. Five patients received 0.1 mg of triamcinolone for subfoveal CNVs and 5 patients received the same dosing for juxtafoveal CNVs.
The results showed that 30% gained ≥5 ETDRS letters, 20% lost ≥5 ETDRS letters, and 50% remained stable after a median of 17 months follow-up.
Although transient increases in intraocular pressure (4 of 9 patients) and progression of cataracts (4 out of 9 phakic patients) were reported, the study concluded that intravitreal triamcinolone was a relatively safe treatment option.
However, the small study size and reported adverse events render these conclusions difficult to generalize.
Most recently, the effect of intravitreal aflibercept for the treatment of CNVs secondary to POHS was evaluated in the HANDLE study.
In an open-label randomized Phase I/II study thirty-nine eyes from 39 patients were randomized in a 1:1 ratio to 2 groups. The Sustained Group eyes (n = 19) underwent monthly intravitreal aflibercept for 3 months, then mandatory intravitreal aflibercept every 2 months for 12 months (with an option for monthly PRN dosing, if needed).
The PRN Group eyes (n = 20) received 1 intravitreal aflibercept at randomization, then monthly PRN for 12 months. At the 12-month follow-up, Sustained Group’s average visual acuity was 84.9 letters (74-94) and Snellen’s equivalent was 20/21 (20/13-20/32), indicating an average improvement of 12 letters (6 letters loss to 36 letters gain) (P < 0.01). The PRN Group’s 12-month average visual acuity was 80.9 letters (60-94) and Snellen equivalent was 20/26 (20/13-20/63), indicating an average gain of 19 letters (4-75) (P < 0.01).
The Sustained Group’s mean baseline CST was 383 μm and the mean 12-month CST was 268 μm (P < 0.01). The mean baseline CST of the PRN Group was 360.8 μm, with the final mean CST of 260.5 μm (P < 0.01).
No reported endophthalmitis, retinal tears, detachments, vitreous hemorrhage, or adverse thrombotic events were reported.
The authors concluded that intravitreal aflibercept resulted in improved visual and anatomical outcomes with a favorable safety profile. PRN intravitreal aflibercept dosing required fewer injections with similar visual and anatomical outcomes compared with sustained dosing.
Even though the use of intravitreal anti-VEGF therapy in treating POHS CNV is considered off-label, it has become a first-line treatment based on its availability and studies demonstrating efficacy and safety.
Historically, systemic amphotericin-B has been studied as a treatment agent for OHS. A small case series initially reported improvement in the lesions after intravenous amphotericin-B, but this was later refuted by a larger study that reported a lack of marked VA improvement and potential adverse side effects such as nephrotoxicity.
Since inflammation is thought to play a role in the pathogenesis of OHS, oral corticosteroids as well as periocular steroids have also been investigated as therapy agents.
The existing studies suggest that there is no benefit to final VA outcomes. Recently, a prospective and interventional study evaluated the effect of fluocinolone acetonide implants in non-AMD CNVs.
Seven of the 14 patients had a diagnosis of POHS and were assigned to high-dose sustained delivery devices of either 2 mg or 6 mg dosing. After a 33-month mean follow-up period, 10 eyes demonstrated VA improvement or stabilization.
Nevertheless, all patients developed elevated intraocular pressures and cataracts while 4 eyes experienced non-ischemic central retinal vein occlusions.
The relative success of laser photocoagulation and anti-VEGF injections in conjunction with these known side effects of corticosteroid use have discouraged their role in treating POHS.
Medical follow up
In patients receiving intravitreal anti-VEGF therapy, it is customary for patients to be followed every 4 weeks as treatment is initiated.
Follow-up can then be slowly extended as determined by the response to treatment and the amount of sub-retinal fluid on clinical exam and ancillary optical coherence tomography testing.
Surgery
Submacular surgery was investigated prior to the PDT and anti-VEGF era for the treatment of subfoveal CNV. The first study to describe a surgical approach to removing subfoveal CNV in POHS showed that 83% of treated eyes had visual acuity improvement or stabilization and a recurrence rate of 37%.
A similar study by the same group demonstrated similar findings with a 44% CNV recurrence rate among 117 POHS patients undergoing subfoveal surgery.
However, after a median follow-up period of 13 months, 35% of patients were found to have postoperative VA of 20/40 or better.
A separate study followed the surgical results of 17 eyes with POHS and CNV for a duration of 32 months. Seven of the 14 eyes with subfoveal CNV achieved a postoperative VA of 20/40 or better while all three extrafoveal CNVs had a final VA of 20/20 vision.
In the submacular surgery trials (SST), the ninth report investigated the benefit of submacular surgery versus observation in patients with classic subfoveal CNV secondary to POHS or other idiopathic causes.
At 24 months, there was no significant difference in median visual acuity between the observation arm (20/250) and the surgery arm (20/160) and 58% of the treated eyes had CNV recurrence.

The authors concluded that there was no benefit for submacular surgery unless VA was worse than 20/100. Nevertheless, submacular surgery is not currently performed routinely for subfoveal CNV due to the availability and success of medical treatments using anti-VEGF therapy.
Macular translocation is an alternative surgical intervention that has been studied as a treatment for subfoveal CNV in POHS patients.
The procedure involves rotating the macula to a healthier RPE and choroidal bed. This approach has been abandoned, however, because studies have shown that VA outcomes are not superior to anti-VEGF injections, Additionally, there are high risks for perioperative complications such as proliferative vitreoretinopathy development.
Complications
Complications of CNV associated with POHS includes formation of disciform scar at the macula, resulting in loss of central vision.
The complications of intravitreal anti-VEGF therapy are similar to those for AMD. These complications include endophthalmitis, subconjunctival hemorrhage, traumatic cataract formation, retinal tears or detachments, and increased intraocular pressure.
Prognosis
Patients with no classical signs of POHS in their fellow eye have a 1% chance of developing CNV. Patients with PPA have a 4% risk of developing CNV. Patients with histo spots in the macula have a 25% risk of CNV development.[1]


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteREFERENCES
- Ophthalmology, A.A.o. in Basic and Clinical Sciences Course (Lifelong Education for the Ophthalmologist, San Fransisco, CA, 2006)
- Oliver, A., Ciulla, T.A. & Comer, G.M. 2005. New and classic insights into presumed ocular histoplasmosis syndrome and its treatment. Curr Opin Ophthalmol 16: 160-5.
- Prasad, A.G. & Van Gelder, R.N. 2005. Presumed ocular histoplasmosis syndrome. Curr Opin Ophthalmol 16: 364-8.
- Ongkosuwito, J.V., Kortbeek, L.M., Van der Lelij, A., Molicka, E., Kijlstra, A., de Smet, M.D. & Suttorp-Schulten, M.S. 1999. Aetiological study of the presumed ocular histoplasmosis syndrome in the Netherlands. Br J Ophthalmol 83: 535-9.
- Giles, C.L. & Falls, H.F. 1961. Further evaluation of amphotericin-B therapy in presumptive histoplasmosis chorioretinitis. Am J Ophthalmol 51: 588-98.
- Krypton laser photocoagulation for neovascular lesions of ocular histoplasmosis. Results of a randomized clinical trial. Macular Photocoagulation Study Group. Arch Ophthalmol. 1987 Nov;105(11):1499-507.
- Rosenfeld PJ, Saperstein DA, Bressler NM, et al. Photodynamic therapy with verteporfin in ocular histoplasmosis: uncontrolled, open-label 2-year study. Ophthalmology. 2004 Sep;111(9):1725-33.
- Nielsen JS, Fick TA, Saggau DD, Barnes CH. Intravitreal anti-vascular endothelial growth factor therapy for choroidal neovascularization secondary to ocular histoplasmosis syndrome. Retina. 2012 Mar;32(3):468-72.
- Lott MN, Schiffman JC, Davis JL. Bevacizumab in inflammatory eye disease. Am J Ophthalmol. 2009 Nov;148(5):711-717.e2.
- Mansour AM, Mackensen F, Arevalo JF, et al. Intravitreal bevacizumab in inflammatory ocular neovascularization. Am J Ophthalmol. 2008;146:410-6.
Test yourself
A few questions straight from this article.
-
Presumed ocular histoplasmosis syndrome is classically attributed to infection with which organism?
POHS is classically attributed to infection with the yeast form of Histoplasma capsulatum, a dimorphic fungus that lives in the soil. -
Which combination of fundoscopic findings characterises presumed ocular histoplasmosis syndrome?
POHS is characterised by multiple white atrophic chorioretinal scars (histo spots), peripapillary atrophy and the absence of vitritis. -
Presumed ocular histoplasmosis syndrome is endemic to which geographic region?
POHS is endemic to the states containing the Ohio and Mississippi river valleys, and has been reported in only a few non-US countries including Mexico, India, the United Kingdom and the Netherlands. -
How does Histoplasma capsulatum reach the choroid in presumed ocular histoplasmosis syndrome?
Infection follows inhalation of the spore or conidia form, classically with cave exploration and exposure to infected bats or birds, after which the organism spreads haematogenously to the choroid. -
What did a Netherlands study find regarding histoplasmin skin antigen testing in clinical POHS?
Although epidemiological studies linked POHS to a positive histoplasmin skin antigen test, a Netherlands study found that all patients with clinical POHS were histoplasmin skin antigen negative, fuelling the controversy over causation. -
Which observation supports an autoimmune inflammatory rather than actively infectious basis for POHS?
POHS is linked to HLA haplotypes DRw2 and B7, leading some to hypothesise an autoimmune inflammatory reaction triggered by organisms including H. capsulatum. -
Choroidal neovascularisation in presumed ocular histoplasmosis syndrome characteristically appears as what?
CNV in POHS often appears at the macula as a greenish-yellow subretinal discoloration surrounded by a pigmented ring, and may progress to a disciform scar with subretinal fibrovascular tissue. -
In what proportion of presumed ocular histoplasmosis syndrome cases are the changes bilateral?
POHS changes can be found bilaterally in up to 60% of cases. -
How does disseminated histoplasmosis differ from presumed ocular histoplasmosis syndrome?
Disseminated histoplasmosis is the exudative or productive H. capsulatum infection of ocular tissues seen in immunocompromised adults or infants, unlike POHS. -
Presumed ocular histoplasmosis syndrome remains asymptomatic until which development occurs?
POHS is asymptomatic until CNV or sequelae such as disciform scars develop, at which point patients report painless vision loss, metamorphopsia, blurred central vision and central or paracentral scotomas.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.