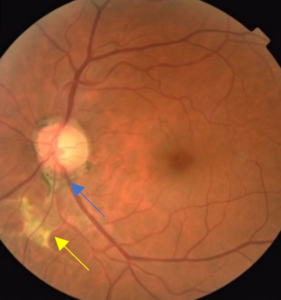
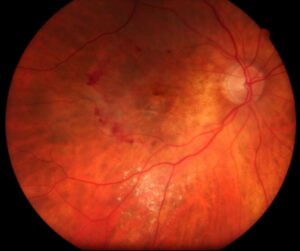
Photopsia is the perception of flashes, sparks, or shimmering light in the absence of a matching external stimulus.
It is a positive visual phenomenon, and its cause may lie anywhere from the vitreous to the occipital cortex.
The most urgent cause is vitreoretinal traction from a retinal tear, but migraine aura, optic neuritis, retinal inflammatory disease, and medications also produce photopsia.
A structured history usually points to the site of the problem before any test is done.
How Photopsia Arises
Photoreceptors and downstream neurons can be triggered by mechanical, electrical, or metabolic stimulation instead of light.
Traction on the retina by the vitreous stimulates retinal neurons directly.
Inflammation or dysfunction of the outer retina or optic nerve produces abnormal spontaneous firing.
Cortical hyperexcitability produces complex visual patterns in migraine and seizures.
Because the origin varies so much, the description of the flashes matters more than their presence.
History: The Clues That Localize the Problem
Useful questions include:
- Is it in one eye or both? Covering each eye in turn answers this
- How long does each episode last? Seconds suggests the retina or optic nerve, while 15 to 30 minutes suggests migraine
- Does it occur in the dark or with eye movement? Traction flashes are more obvious in the dark and with saccades
- What color and shape? Zigzag or shimmering arcs that expand suggest migraine, while brief white lightning streaks in the temporal field suggest vitreous traction
- Is it followed by a scotoma, curtain, or drop in vision?
- Are there new floaters?
- Which medications is the patient taking?
The same flashes recurring in a fixed location for weeks may point to a localized retinal lesion.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteCauses
Vitreoretinal Traction
Acute posterior vitreous detachment causes flashes and floaters, and a tear or detachment can follow (see posterior vitreous detachment and horseshoe tears).
The flashes are typically brief, monocular, and temporal, and they are more noticeable in dim light.
Migraine Aura
Migraine aura is binocular, builds over minutes, and often shows a scintillating zigzag margin that slowly moves across the visual field.
It lasts five to sixty minutes and may occur without headache.
Onset after age 50, unusually prolonged or monocular episodes, or associated weakness require further investigation.
Retinal and Choroidal Disease
Photopsia can be a prominent symptom in several outer retinal disorders:
- Acute zonal occult outer retinopathy and related conditions (see AZOOR)
- Multiple evanescent white dot syndrome (see MEWDS)
- Birdshot chorioretinopathy (see birdshot chorioretinopathy)
- Autoimmune and paraneoplastic retinopathies
- Bilateral diffuse uveal melanocytic proliferation (see BDUMP)
- Choroidal tumors and posterior scleritis
These conditions often have a normal-looking fundus early on, so OCT, autofluorescence, visual fields, and electroretinography have a role when the history is suggestive.
Optic Nerve Disease
Optic neuritis may produce photopsia, and some patients notice flashes triggered by eye movement, which are known as movement phosphenes (see optic neuritis).
These are accompanied by pain on eye movement, a relative afferent pupillary defect, and reduced color vision.
Cortical Causes
Occipital seizures cause brief, stereotyped, colored flashes, often in one hemifield.
Occipital ischemia and vascular malformations can produce similar symptoms.
Medications and Toxins
Several drugs are associated with visual disturbances, including digoxin, voriconazole, sildenafil and related drugs, and some antiepileptics.
A careful medication review is worthwhile in patients with new bilateral flashes and a normal examination.
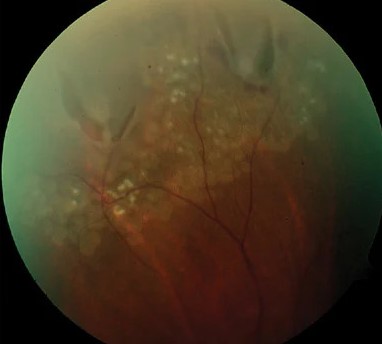
Pseudophakic Dysphotopsia
After cataract surgery, some patients notice arcs or streaks of light (positive dysphotopsia) or a temporal dark shadow (negative dysphotopsia).
These are related to the interaction of light with the intraocular lens edge and the anatomy of the anterior segment, and both often improve with neural adaptation.
Normal Phenomena
Pressure phosphenes on rubbing the eyes, a brief flash on a sudden head movement, and afterimages are physiologic.
Evaluation
The examination is tailored to the history.
- Dilated fundus examination with scleral depression for any new unilateral flashes
- OCT of the macula and, where indicated, autofluorescence
- Visual fields when a scotoma is reported
- Full-field electroretinography when an inherited or autoimmune retinopathy is suspected
- MRI and neurologic assessment for atypical migraine features, binocular episodes with focal deficits, or suspected optic nerve disease
Flashes with no obvious cause and a normal ocular examination should not be dismissed if they persist.
Repeat examination after a few weeks is reasonable when the first examination was normal and the history suggests traction.
Special Situations
Children
Photopsia is uncommon in children and is harder to interpret, because young patients may not describe it clearly.
Migraine, occipital epilepsy, and inherited or inflammatory retinal disease are the leading considerations, and a child with persistent unexplained flashes should have a full dilated examination and often electrophysiology.
Older Adults
New photopsia after age 50 is most often traction from PVD, but occipital ischemia and vertebrobasilar insufficiency also cause positive visual phenomena.
Flashes that are brief, binocular, and accompanied by dizziness, diplopia, or limb symptoms need a neurologic assessment.
Patients With Normal Examination
Some patients have persistent flashes despite a normal fundus, normal OCT, and normal fields.
Repeat examination and electrophysiology may then be considered, and the possibility of an autoimmune retinopathy should be kept in mind when the flashes are bilateral, progressive, and associated with field loss or night vision difficulty.
Management
Treatment depends on the cause.
- Retinal tears are treated with laser retinopexy or cryotherapy, and detachment needs surgical repair (see laser retinopexy)
- Migraine aura is managed with reassurance, trigger avoidance, and preventive treatment when frequent
- Inflammatory and autoimmune retinopathies require specialist care and often systemic therapy
- Drug-related photopsia may resolve with dose adjustment or a change in medication
- Dysphotopsia is managed by reassurance, and rarely by IOL exchange or secondary piggyback lens
Patients with benign traction flashes should be told what changes to report.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Hollands H, Johnson D, Brox AC, Almeida D, Simel DL, Sharma S. Acute-onset floaters and flashes: is this patient at risk for retinal detachment? JAMA. 2009;302:2243-2249.
- Coffee RE, Westfall AC, Davis GH, Mieler WF, Holz ER. Symptomatic posterior vitreous detachment and the incidence of delayed retinal breaks: case series and meta-analysis. Am J Ophthalmol. 2007;144:409-413.
- Headache Classification Committee of the International Headache Society. The International Classification of Headache Disorders, 3rd edition. Cephalalgia. 2018;38:1-211.
- Davis FA, Bergen D, Schauf C, McDonald I, Deutsch W. Movement phosphenes in optic neuritis: a new clinical sign. Neurology. 1976;26:1100-1104.
- Masket S, Fram NR. Pseudophakic dysphotopsia: review of incidence, cause, and treatment of positive and negative dysphotopsia. Ophthalmology. 2021;128:e195-e205.
Test yourself
A few questions straight from this article.
-
How is photopsia defined?
Photopsia is the perception of flashes, sparks or shimmering light with no matching external stimulus, a positive visual phenomenon arising anywhere from vitreous to occipital cortex. -
Photopsia lasting only seconds per episode points to a problem at which site?
Episodes measured in seconds suggest a retinal or optic nerve origin, whereas episodes lasting many minutes point instead toward migraine. -
Which pattern of flashes suggests vitreoretinal traction?
Traction flashes are brief, monocular and temporal, and patients notice them more in dim light and with saccades. -
How long does a typical migraine aura last?
Migraine aura is binocular, builds over minutes with a scintillating zigzag margin, lasts five to sixty minutes, and may occur with no headache at all. -
Which feature of a visual aura calls for further investigation?
Onset after 50, unusually prolonged or monocular episodes, and associated weakness are the features that take an aura outside the expected pattern. -
Flashes triggered by eye movement in optic neuritis are accompanied by which findings?
Movement phosphenes in optic neuritis come with pain on eye movement, a relative afferent pupillary defect and reduced colour vision. -
Which pattern of photopsia suggests an occipital seizure?
Occipital seizures produce brief, stereotyped, coloured flashes often confined to one hemifield; occipital ischaemia and vascular malformations can look similar. -
Which medication is associated with visual disturbance including photopsia?
Digoxin, voriconazole, sildenafil and related drugs, and some antiepileptics are linked to visual disturbance, so a medication review is worthwhile with new bilateral flashes. -
What is negative dysphotopsia after cataract surgery?
Positive dysphotopsia is arcs or streaks of light and negative dysphotopsia a temporal dark shadow; both relate to light striking the intraocular lens edge and often ease with neural adaptation. -
How is a retinal tear found while assessing new photopsia treated?
Retinal tears are sealed with laser retinopexy or cryotherapy, while an established detachment requires surgical repair.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.