Occult macular dystrophy (OMD), also called Miyake disease, is an inherited macular disorder in which central vision declines progressively while the fundus, fluorescein angiogram, and, at first, the OCT look normal.
Patients are often labeled as having amblyopia, optic neuropathy, or functional visual loss for years before the diagnosis is made.
The key to diagnosis is recognizing that a normal-looking macula does not exclude macular disease, and that electrophysiology can settle the question.
What Is Occult Macular Dystrophy?
Miyake and colleagues described the condition in 1989 in patients with bilateral central vision loss, a normal fundus, and abnormal focal macular electroretinograms.
The disease usually begins between childhood and middle age, and it is bilateral and symmetric in most cases.
Dominant mutations in the RP1L1 gene were identified as a cause of the familial disease in 2010, and the gene product is expressed in photoreceptors.
Many patients have no family history or mutation, and sporadic cases exist.
The disorder is rare, and it is likely underdiagnosed.
Clinical Features
Patients report slow, painless, bilateral loss of central vision, often with a central scotoma.
Visual acuity may range from mild to severe reduction, and color vision and contrast are often affected.
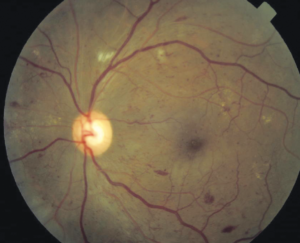
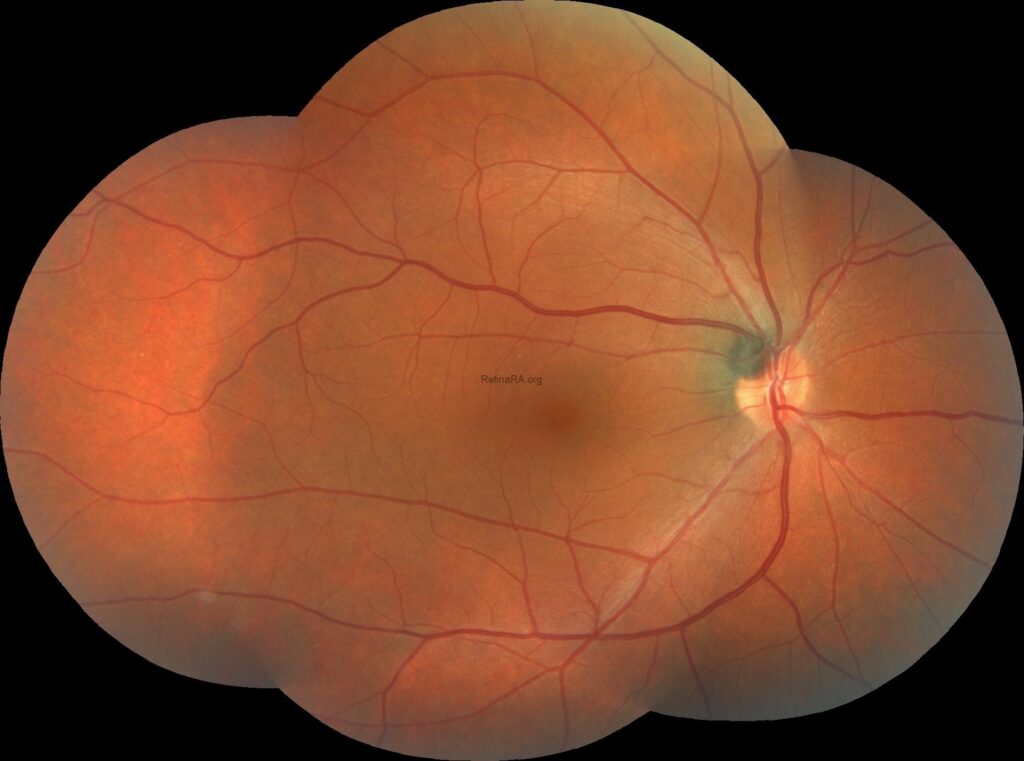
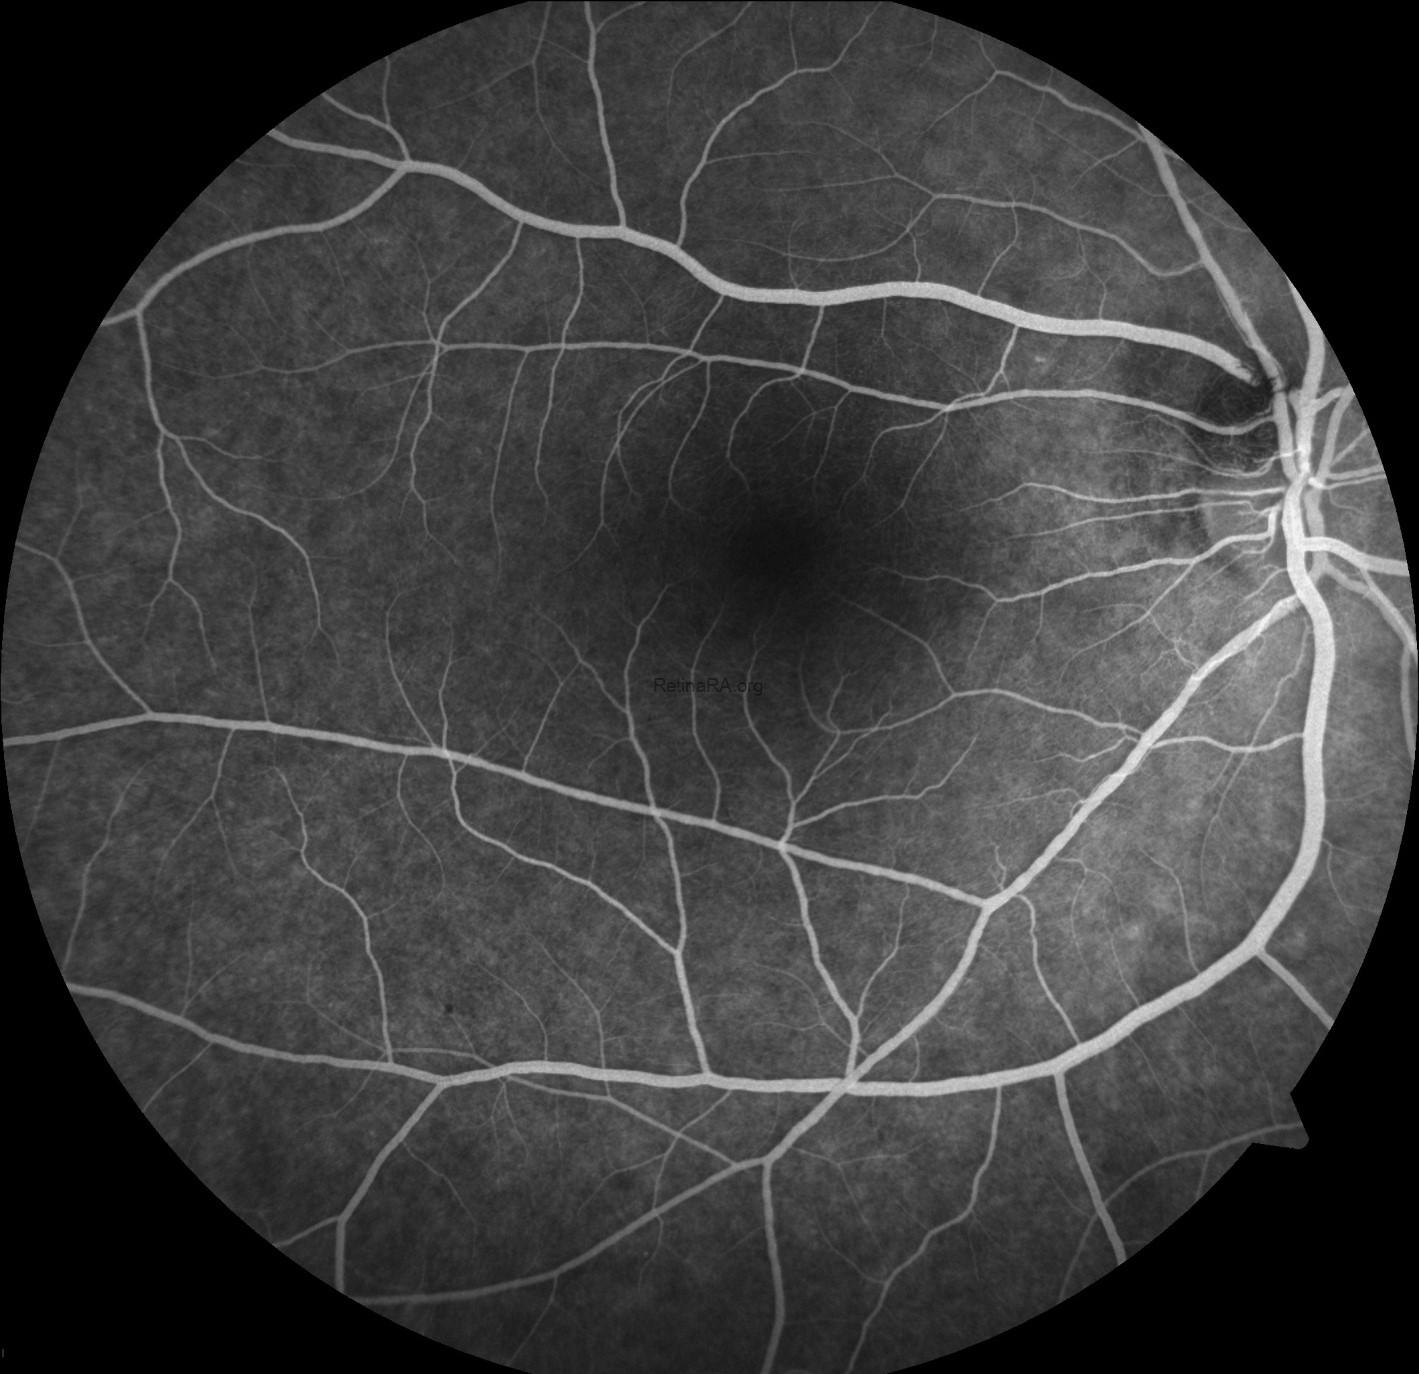
The fundus appears normal, and fluorescein angiography and autofluorescence are usually normal.
Peripheral vision is preserved.
Full-field ERG is normal, which separates OMD from generalized retinal dystrophies.
Visual field testing shows a central scotoma.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteImaging and Electrophysiology
OCT
OCT is the key structural test.
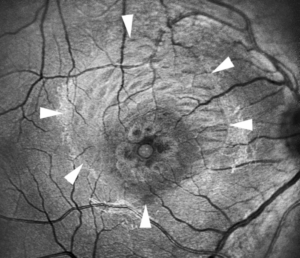
In early disease the retina may look normal, although careful examination can show subtle abnormalities of the outer retinal bands.
Typical findings include:
- Disruption or blurring of the ellipsoid zone in the fovea
- Loss or irregularity of the interdigitation zone
- Thinning of the outer nuclear layer at the fovea
The abnormalities are limited to the central macula, and they may be subtle enough to be missed unless the scan is examined layer by layer (see fundus autofluorescence for the complementary functional imaging).
Multifocal and Focal ERG
Multifocal ERG shows reduced amplitudes in the central macula with preserved peripheral responses.
Focal macular ERG shows a reduced response, and the pattern helps confirm the diagnosis when full-field ERG is normal.
Pattern ERG is usually reduced in the macular component.
Differential Diagnosis
The main differential diagnoses include:
- Optic neuropathies such as dominant optic atrophy and Leber hereditary optic neuropathy, which affect optic nerve function and cause disc pallor or RNFL loss (see dominant optic atrophy and LHON)
- Early Stargardt disease, in which fundus flecks and autofluorescence changes may appear later (see Stargardt disease)
- Cone and cone-rod dystrophies, which cause abnormal full-field photopic ERG (see cone-rod dystrophy)
- Toxic maculopathy, including hydroxychloroquine retinopathy (see hydroxychloroquine toxicity)
- Acute zonal occult outer retinopathy and other outer retinopathies (see AZOOR)
- Amblyopia and functional visual loss
A normal fundus with unexplained bilateral central loss should trigger high-resolution OCT and electrophysiology before a functional diagnosis is made.
Why the Diagnosis Is Delayed
Several features conspire to delay the diagnosis.
The macula looks normal on examination, so the visual loss is attributed to amblyopia, refractive error, or a psychological cause.
Young patients may be dismissed as having functional visual loss, particularly when the fundus and optic nerve are unremarkable.
Tests that would reveal the problem, such as high-quality OCT and multifocal ERG, are not part of routine care.
A useful rule is to look for structural and functional evidence before accepting a functional label in any patient with unexplained, symmetric central loss.
Optic neuropathy is excluded with visual evoked potentials, RNFL analysis, and if needed MRI.
A normal MRI and normal RNFL in a patient with a central scotoma should prompt macular electrophysiology.
Genetics
RP1L1 mutations, particularly the p.Arg45Trp variant, cause autosomal dominant OMD.
Penetrance and expressivity vary within families.
Genetic testing helps confirm the diagnosis, and it allows counseling of relatives.
Negative testing does not exclude OMD, since a large proportion of patients do not carry an RP1L1 mutation.
Approach to Unexplained Bilateral Central Vision Loss
A structured approach helps when the fundus looks normal.
- Confirm refraction and rule out media opacity, keratoconus, and amblyopia
- Check pupils, color vision, and visual fields, and look for a relative afferent pupillary defect
- Measure RNFL and ganglion cell thickness on OCT to exclude optic neuropathy
- Review the foveal outer retinal bands scan by scan, and compare with the fellow eye
- Ask about family history, medications such as hydroxychloroquine, and possible toxic or nutritional causes
- Arrange full-field and multifocal ERG when structural tests are normal or equivocal
- Consider genetic testing for RP1L1 and for other macular dystrophy genes
The ophthalmologist should avoid attributing the loss to a functional cause until these steps have been completed.
Management and Prognosis
There is currently no treatment that halts or reverses the disease.
Care consists of:
- Confirming the diagnosis to avoid unnecessary investigations for optic nerve or brain disease
- Genetic counseling for the patient and family
- Low-vision assessment, magnification, and lighting advice
- Regular monitoring of visual acuity and OCT
- Counseling on driving and occupational limits when vision falls
The rate of progression varies.
Some patients remain stable for years, while others lose central vision to a level that limits reading.
Peripheral vision is not affected, and patients stay independent in mobility.
Gene-based therapies for inherited retinal disease are under development, and patients with a confirmed genetic diagnosis may be candidates for future trials (see gene therapy in inherited retinal disease).


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Miyake Y, Ichikawa K, Shiose Y, Kawase Y. Hereditary macular dystrophy without visible fundus abnormality. Am J Ophthalmol. 1989;108:292-299.
- Akahori M, Tsunoda K, Miyake Y, et al. Dominant mutations in RP1L1 are responsible for occult macular dystrophy. Am J Hum Genet. 2010;87:424-429.
- Brockhurst RJ, Sandberg MA. Optical coherence tomography findings in occult macular dystrophy. Am J Ophthalmol. 2007;143:516-518.
- Piao CH, Kondo M, Tanikawa A, Terasaki H, Miyake Y. Multifocal electroretinogram in occult macular dystrophy. Invest Ophthalmol Vis Sci. 2000;41:513-517.
- Kabuto T, Takahashi H, Goto-Fukuura Y, et al. A new mutation in the RP1L1 gene in a patient with occult macular dystrophy associated with a depolarizing pattern of focal macular electroretinograms. Mol Vis. 2012;18:1031-1039.
Test yourself
A few questions straight from this article.
-
Which presentation is characteristic of occult macular dystrophy?
Occult macular dystrophy causes slow, painless, bilateral central visual loss with a central scotoma, while the fundus, fluorescein angiogram and autofluorescence look normal. -
Which result separates occult macular dystrophy from generalized retinal dystrophies?
Full-field ERG is normal in occult macular dystrophy, which distinguishes it from generalized retinal dystrophies, and peripheral vision is preserved. -
What does multifocal ERG show in occult macular dystrophy?
Multifocal ERG shows reduced amplitudes in the central macula with preserved peripheral responses, and focal macular ERG is also reduced. -
Which gene carries the dominant mutations that cause occult macular dystrophy?
Dominant RP1L1 mutations, particularly the p.Arg45Trp variant, cause autosomal dominant occult macular dystrophy, and the gene product is expressed in photoreceptors. -
Which OCT change is typical of occult macular dystrophy?
Typical findings are blurring or disruption of the foveal ellipsoid zone, loss of the interdigitation zone and outer nuclear layer thinning, confined to the central macula. -
Which labels are commonly but wrongly applied to patients with occult macular dystrophy?
Because the macula looks normal, the loss is attributed to amblyopia, refractive error or a psychological cause for years before the diagnosis is made. -
A patient has a central scotoma with a normal MRI and normal RNFL thickness. What should follow?
A normal MRI and normal RNFL in a patient with a central scotoma should prompt macular electrophysiology rather than acceptance of a functional diagnosis. -
Which feature helps distinguish early Stargardt disease from occult macular dystrophy?
In early Stargardt disease fundus flecks and autofluorescence abnormalities may appear later, whereas in occult macular dystrophy autofluorescence stays normal. -
What does a negative RP1L1 genetic test mean in suspected occult macular dystrophy?
Negative testing does not exclude occult macular dystrophy, because a large proportion of patients do not carry an RP1L1 mutation and sporadic cases exist. -
What does management of occult macular dystrophy consist of?
No treatment halts or reverses the disease, so care means confirming the diagnosis to avoid needless brain and optic nerve investigation, genetic counselling, low-vision support and monitoring.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.