CASE REPORT
A 61-year-old woman with rheumatoid arthritis treated with 400 mg/kg hydroxychloroquine daily for 6 years (daily dose, 5.72 mg/real body weight or 6.5 mg/kg ideal body weight; cumulative dose, 876 g) experienced progressive central vision loss and a scotoma affecting her reading ability and was referred to the Retina service.
Prior to the yearly examination, only Ishihara color vision and Amsler grid testing were normal.
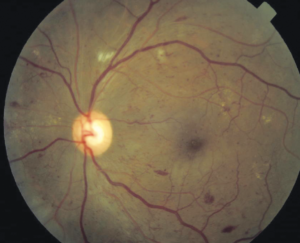
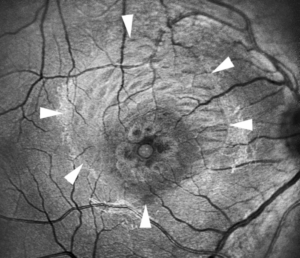
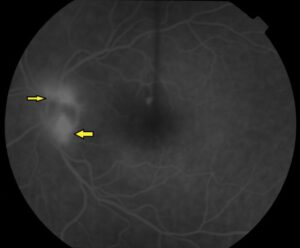
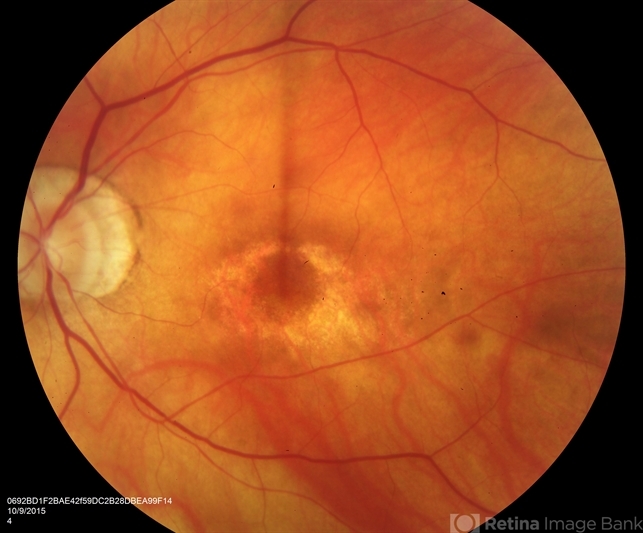
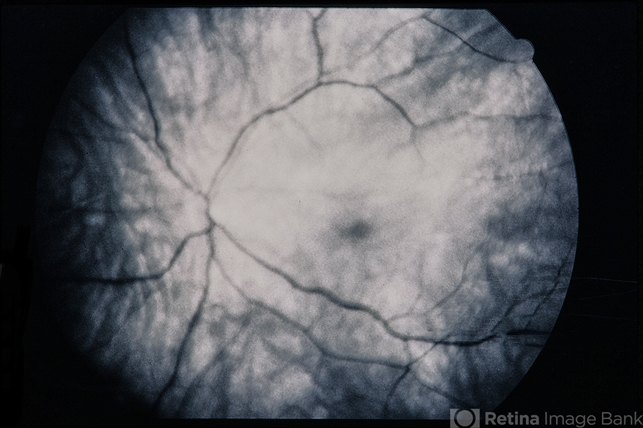
On examination, visual acuity was 20/40 in the right eye and 20/30 in the left eye. A fundus examination showed bilateral bull’s-eye maculopathy, a classic finding of hydroxychloroquine retinal toxicity.
DISEASE
Hydroxychloroquine is a well-tolerated medication for various rheumatologic and dermatologic conditions.
It has also been used off-label as a potential therapy for the novel coronavirus, COVID-19, although data to support its efficacy is mixed and primarily anecdotal due to the lack of large controlled trials. Its main side effects are gastrointestinal upset (vomiting, diarrhea, stomach cramps), skin rash, headache, dizziness, and ocular toxicity.
However, serious side effects including arrhythmia, bronchospasm, angioedema, and seizures can rarely occur. Within the eye, hydroxychloroquine can adversely impact the cornea, ciliary body, and retina.
Hydroxychloroquine (Plaquenil) and chloroquine cause ocular toxicity to various parts of the eye such as the cornea, ciliary body, and retina.
Its toxic effects on the retina are seen in the macula. While early toxicity may be asymptomatic, patients with a more advanced stage of toxicity may complain of color vision changes or paracentral scotomas.
Advanced hydroxychloroquine toxicity presents as a bullseye maculopathy. Since retinal toxicity is usually irreversible, early detection of retinal toxicity and cessation of the offending agent is the best treatment.
Corneal toxicity presents as an intraepithelial deposition of the drug into the cornea, which rarely affects vision. Ciliary body dysfunction disturbs accommodation and is rare.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteDiagnosis
History:
For retinopathy, patients should be asked about poor central vision, change in color vision, central blind spots, difficulty reading, and metamorphopsia.
For keratopathy, patients should be asked about halos around light, decreased visual acuity, or photophobia. For ciliary body dysfunction, patients should be asked about difficulty with reading and other activities that require accommodation.
To assess risk factors, they should be asked questions such as when they started taking Plaquenil, what their current dosage is, what their current body weight is, whether or not they have had an ophthalmic examination in the past, how often they see their rheumatologist, whether they have liver or kidney disease, and whether they are taking other drugs associated with retinal toxicity, such as tamoxifen.
Physical examination:
Physical exam should focus on the condition that requires hydroxychloroquine therapy to be initiated.
Knowing the status of the primary disease process will be helpful to determine if cessation of treatment or lowering of medication is indicated.

Signs:
Hydroxychloroquine retinopathy is caused by a build-up of the systemic drug and thus the findings are bilateral and symmetric.
The early signs of hydroxychloroquine toxicity are macular edema and/or bilateral granular depigmentation of the RPE in the macula.
With continued exposure to the drug, this can progress to an atrophic bullseye maculopathy with concentric rings of hypopigmentation and hyperpigmentation surrounding the fovea.
As mentioned above, these findings may be in the peripheral macula near the arcades in patients of Asian descent.
These changes can progress with additional drug exposure to include other areas of the fundus, causing widespread atrophy.
At this point, attenuation of retinal arterioles and optic disc pallor can also be evident. Hydroxychloroquine keratopathy presents as an intraepithelial deposit.
The deposits may take the form of whirls, linear opacities, or punctate lesions. Ciliary body dysfunction can be detected by poor near vision.
Symptoms
In the initial stages of hydroxychloroquine toxicity, patients are often asymptomatic. If they do have symptoms they complain of visual color deficits, specifically red objects, missing central vision, difficulty reading, reduced or blurred vision, glare, flashing lights, and metamorphopsia.
The symptoms are often in both eyes. In keratopathy, patients complain of halos around light and photophobia. In ciliary body dysfunction, patients will not be able to read or do other activities requiring accommodation.
MANAGEMENT
General treatment
At the first signs of retinal toxicity, hydroxychloroquine should be stopped to prevent further retinal damage and visual loss.
Medical therapy:
There is no diet or medical therapy to prevent or treat this type of retinal toxicity; the best approach is primary prevention.
Often, by the time a true bullseye maculopathy becomes visible on examination, the disease has already been progressing for years.
When recommending cessation of the drug, it is important to work with the patient’s rheumatologist (or prescriber of the drug) so that systemic control of the disease is also addressed and optimized.

Medical follow-up:
Patients should be examined before starting hydroxychloroquine. Patients should be re-examined at 5 years of therapy and annually thereafter, unless risk factors are present for which then annual visits should commence earlier.
Surgery:
There is no surgical therapy.
Prognosis
In general, hydroxychloroquine and chloroquine retinopathy are not reversible, and even following drug cessation, cellular damage appears to continue for a certain period of time.
However, the earlier the retinopathy is recognized, the greater the chance of visual preservation. Keratopathy has been reported to be fully reversible.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteREFERENCES
- Gbinigie K, Frie K. Should chloroquine and hydroxychloroquine be used to treat COVID-19? A rapid review. BJGP Open 2020. 2020;Epub ahead of press.
- Yam, J.C. & Kwok, A.K. 2006. Ocular toxicity of hydroxychloroquine. Hong Kong Med J 12: 294-304.
- Marmor MF, Kellner U, Lai TYY, Melles RB, Mieler WF, for the American Academy of Ophthalmology. Recommendations on Screening for Chloroquine and Hydroxychloroquine Retinopathy. Ophthalmology. 2016;123:1386-94.
- Lang, G.K. Ophthalmology: A Pocket Textbook Atlas (Thieme, Stuttgart, 2007).
- Lee Y, Vinayagamoorthy N, Han K, et al. Association of polymorphisms of cytochrome P450 2D6 with blood hydroxychloroquine levels in patients with systemic lupus erythematosus. Arthritis Rheumatol. 2016;68:184-90.
Test yourself
A few questions straight from this article.
-
Which ocular structures can hydroxychloroquine and chloroquine damage?
Hydroxychloroquine and chloroquine cause ocular toxicity in the cornea, the ciliary body and the retina, with the retinal effects concentrated in the macula. -
Why are the retinal findings of hydroxychloroquine toxicity bilateral and symmetric?
Hydroxychloroquine retinopathy results from build-up of the systemically administered drug, so the retinal findings are bilateral and symmetric. -
How does advanced hydroxychloroquine retinopathy appear on fundus examination?
With continued exposure the retinopathy progresses to an atrophic bull's-eye maculopathy, with concentric rings of hypopigmentation and hyperpigmentation surrounding the fovea. -
In patients of Asian descent, where may hydroxychloroquine retinal changes appear?
In patients of Asian descent the toxic changes may lie in the peripheral macula near the arcades rather than in the central macula, which matters when planning screening tests. -
Which background factors should be sought when assessing hydroxychloroquine retinal toxicity risk?
Risk assessment includes the start date, current dose, body weight, previous eye examinations, liver or kidney disease, and other drugs associated with retinal toxicity such as tamoxifen. -
What examination schedule is advised for patients taking hydroxychloroquine?
Patients should be examined before starting hydroxychloroquine, re-examined at 5 years of therapy and annually thereafter, with annual visits beginning earlier when risk factors are present. -
What should happen at the first signs of hydroxychloroquine retinal toxicity?
Hydroxychloroquine should be stopped at the first signs of retinal toxicity to prevent further damage, in conjunction with the rheumatologist or prescriber so the systemic disease remains controlled. -
Which symptoms do patients with more advanced hydroxychloroquine retinal toxicity report?
Early toxicity is often asymptomatic; at a more advanced stage patients complain of colour vision change, particularly for red objects, paracentral scotomas, difficulty reading and metamorphopsia, usually in both eyes. -
What is the prognosis of established hydroxychloroquine retinopathy after the drug is stopped?
Hydroxychloroquine and chloroquine retinopathy are not reversible and cellular damage appears to continue for some time even after cessation, so the earlier it is recognised the greater the chance of preserving vision. -
How does hydroxychloroquine keratopathy present and behave?
Keratopathy appears as intraepithelial drug deposits forming whorls, linear opacities or punctate lesions, rarely affects vision, and has been reported to be fully reversible.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.