Diabetic retinopathy classification gives clinicians a common language for the stage of disease. It also links each stage to a referral interval and a treatment decision.
Two systems dominate practice. The ETDRS scale was built for research, while the International Clinical scale was designed for the clinic.
Therefore, knowing both helps you read reports, talk with colleagues, and apply the guidelines.
Diabetic Retinopathy Classification: The Two Systems
The Early Treatment Diabetic Retinopathy Study graded fundus photographs in seven fields. Its severity scale has many steps, and each step predicts the risk of progression.
The scale remains the research standard. However, a scale with that many levels is not practical at the bedside.
In 2003, an international consensus group proposed a simpler clinical scale. It has five levels of retinopathy and a separate scale for macular edema.
The group built the scale from ETDRS data. As a result, clinicians can teach it and apply it without photographs.
The International Clinical Scale
- No apparent retinopathy: the retina shows no abnormalities
- Mild nonproliferative: the retina shows microaneurysms only
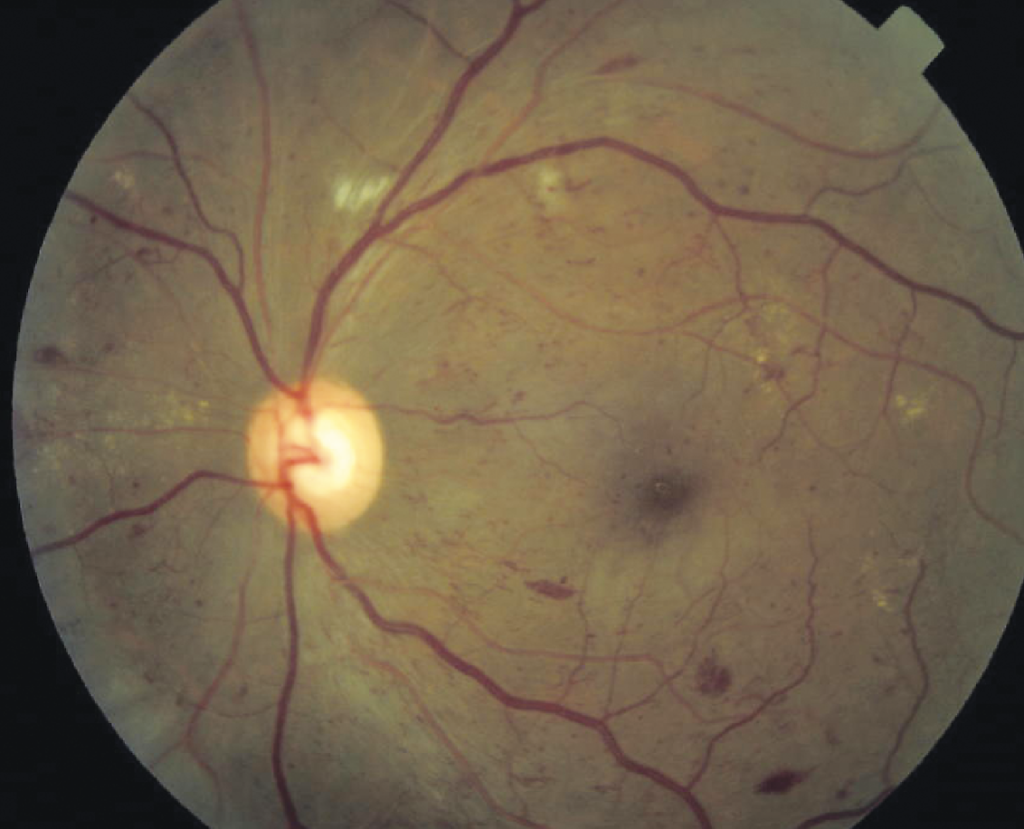
- Moderate nonproliferative: the retina shows more than microaneurysms but less than severe disease, such as dot and blot hemorrhages, hard exudates, and cotton wool spots
- Severe nonproliferative: the retina meets any one of the 4-2-1 criteria
- Proliferative: the eye shows neovascularization, vitreous hemorrhage, or preretinal hemorrhage
Clinicians grade macular edema as absent, mild, moderate, or severe. The grade depends on the distance of the exudates or thickening from the center of the macula.
The scale applies to retinopathy seen on clinical examination. Therefore, OCT findings alone do not change the grade.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteThe 4-2-1 Rule in Diabetic Retinopathy Classification
Severe nonproliferative retinopathy is present when any one of the following appears.
- 4: severe intraretinal hemorrhages and microaneurysms in all four quadrants
- 2: venous beading in two or more quadrants (see venous beading)
- 1: intraretinal microvascular abnormalities in one or more quadrants (see intraretinal microvascular abnormalities)
The rule comes from an ETDRS finding. These features carried a high risk of progression to proliferative disease within one year.
Because of that risk, clinicians often treat these eyes or follow them closely, depending on the other risk factors.
Why Diabetic Retinopathy Classification Changes Management
First, each stage carries a different risk of progression and a different follow-up interval.
Eyes with no or mild disease can return at yearly intervals. Moderate disease usually needs shorter intervals, depending on the guideline in use.
Severe and proliferative disease call for referral to a retina specialist. That specialist then decides between laser and anti-VEGF therapy (see proliferative diabetic retinopathy and panretinal photocoagulation).
Macular edema that involves the center needs treatment whatever the retinopathy level (see diabetic macular edema).
Practical Notes
- Dilate the pupil and examine all four quadrants, since peripheral lesions can raise the grade
- Use photographs, and widefield imaging when available, because documented findings are easier to compare over time (see ultra-widefield retinal imaging)
- Always record both the retinopathy grade and the macular edema grade in the chart
- Remember that screening programs in many countries use their own simplified grades, such as R and M levels, which map onto the clinical scale
- Re-grade after a significant change in glycemic control, pregnancy, or cataract surgery
Moreover, telling the patient the stage of disease improves adherence to follow-up. It also helps control of blood glucose, blood pressure, and lipids.
Screening Programs and Referral
National screening programs use grades that correspond to the clinical scale. These grades decide who needs a specialist and how soon.
In general, clinicians refer eyes with proliferative disease, severe nonproliferative disease, or central macular edema urgently, within a few weeks.
Eyes with moderate disease may return at shorter intervals, while eyes with mild or no disease return at routine intervals.
The ophthalmologist who receives a referral should review the images and regrade them, because screening images can underestimate peripheral disease.
Limitations
The clinical scale grades only what the fundus shows. It leaves out OCT thickness, nonperfusion on angiography, and peripheral lesions visible only on widefield images.
Recent widefield studies suggest that mainly peripheral lesions may carry extra risk, so the scale may evolve.
For now, use the classification as a guide, and combine it with the whole clinical picture. Include systemic risk factors, pregnancy, and the speed of change.
When you write the report, state the grade for each eye separately, because the two eyes can differ. Also state whether macular edema is present and where.
Overall, a clear, consistent grade in the chart makes the next visit more useful to every clinician who sees the patient.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Wilkinson CP, Ferris FL III, Klein RE, et al. Proposed international clinical diabetic retinopathy and diabetic macular edema disease severity scales. Ophthalmology. 2003;110:1677-1682.
- Early Treatment Diabetic Retinopathy Study Research Group. Grading diabetic retinopathy from stereoscopic color fundus photographs: an extension of the modified Airlie House classification. ETDRS report number 10. Ophthalmology. 1991;98:786-806.
- Ryan SJ, Schachat AP, Wilkinson CP, et al, eds. Retina. 6th ed. Elsevier; 2018.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 12: Retina and Vitreous. AAO; current edition.
Test yourself
A few questions straight from this article.
-
How many levels of retinopathy does the International Clinical diabetic retinopathy scale contain?
The international consensus scale has five levels of retinopathy plus a separate scale for macular edema, and was derived from Early Treatment Diabetic Retinopathy Study data. -
How do the ETDRS and International Clinical diabetic retinopathy scales differ in purpose?
The ETDRS scale, graded from fundus photographs, has too many steps for the bedside, so a simpler consensus scale was built for clinical use. -
What defines mild nonproliferative diabetic retinopathy on the International Clinical scale?
Mild nonproliferative disease means microaneurysms alone; anything more, short of the severe criteria, becomes moderate disease. -
Which single finding is enough to classify an eye as severe nonproliferative diabetic retinopathy?
Any one arm of the 4-2-1 rule suffices: severe hemorrhages in four quadrants, venous beading in two or more, or intraretinal microvascular abnormalities in one or more. -
Eyes meeting the 4-2-1 criteria carry a high risk of which outcome, and over what period?
The rule comes from an ETDRS observation that these features predicted a high rate of progression to proliferative disease within a year. -
What defines proliferative diabetic retinopathy on the International Clinical scale?
The proliferative level is reached once neovascularization, vitreous hemorrhage or preretinal hemorrhage appears. -
On what does the diabetic macular edema grade depend in the International Clinical scale?
Macular edema is graded absent, mild, moderate or severe according to how close the exudates or thickening lie to the centre of the macula. -
How do OCT findings affect the International Clinical retinopathy grade?
The scale grades retinopathy seen on clinical examination, so OCT thickness alone does not move the retinopathy level. -
Which eyes should be referred urgently, within a few weeks, under diabetic screening pathways?
Severe nonproliferative disease, proliferative disease and central macular edema are the urgent referrals; milder grades return at routine or shortened intervals. -
At what interval can eyes with no retinopathy or mild disease usually be reviewed?
No apparent and mild nonproliferative disease can be seen at yearly intervals, while moderate disease needs shorter intervals set by the local guideline.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.