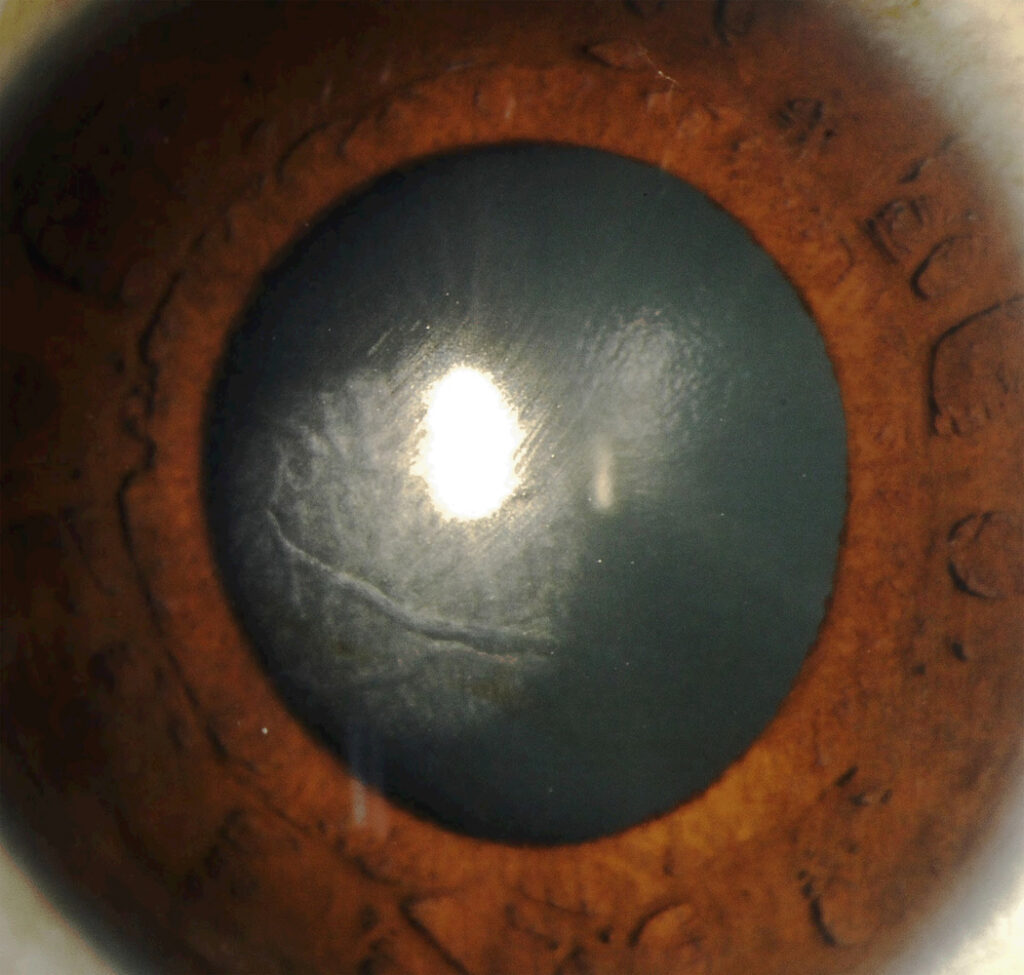
Central toxic keratopathy (CTK) is an acute, noninflammatory central stromal opacity that follows laser refractive surgery.
Sonmez and Maloney described it as a distinct syndrome in 2007. Because it resembles severe diffuse lamellar keratitis, clinicians often treat it as inflammation, however its course and management differ, and early recognition spares the patient unnecessary steroid exposure.
What Is Central Toxic Keratopathy?
CTK is a dense central stromal opacity after LASIK, with corneal flattening and a hyperopic shift. Reports also describe it after PRK, so a flap is not essential, and the eye is usually quiet, with few or no interface cells.
When Central Toxic Keratopathy Appears
Onset typically falls within the first postoperative week, often after a few uneventful days, and then the central cornea changes over a short period. As a result, a normal first-day visit does not exclude it, and it may affect one eye or both eyes after bilateral surgery.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteSymptoms Patients Report
Most patients notice blurred vision and poorer quality of vision. Pain is mild or absent, which fits the noninflammatory picture, and some describe glare or ghosting around lights, while distance vision drifts as the refraction moves toward hyperopia.
Slit Lamp Signs of Central Toxic Keratopathy
- Dense central or paracentral stromal opacity
- Fine striae, sometimes described as a mud-cracked pattern
- Minimal interface cellular infiltrate
- Little or no anterior chamber reaction
- Intact or rapidly healing epithelium
Why the Hyperopic Shift Occurs
Pachymetry and topography usually show central stromal thinning and flattening, because loss of central tissue flattens the anterior curvature. Therefore, the refraction moves in a hyperopic direction, and authors suspect keratocyte loss and collagen remodeling, although the mechanism is unproven.
Possible Causes
The cause of CTK remains unknown, and the name reflects a suspected toxic injury to central keratocytes. For example, authors have proposed chemical exposure during surgery and laser-related factors, however no single trigger has been confirmed.
Central Toxic Keratopathy vs DLK Stage 4
Diffuse lamellar keratitis is a sterile interface inflammation graded in four stages, and stage 4 brings dense central opacity, stromal melting and a hyperopic shift. In DLK, however, earlier stages with visible interface cells usually precede it, often within days, while CTK tends to appear without that inflammatory build-up.
DLK cells stay at the interface, while CTK opacity is central and may involve stroma beyond it. Finally, DLK responds to intensive steroids, whereas CTK usually does not.
Excluding Infection
Any new opacity after LASIK raises concern for microbial keratitis, and infection usually brings pain, a focal infiltrate, an epithelial defect and anterior chamber reaction. In that case, culture and treat infection first (see post-LASIK keratitis).
Atypical mycobacteria and fungi may present late, so keep a low threshold for flap lift and culture.
Other Mimics
Pressure-induced stromal keratopathy develops during steroid treatment and shows interface haze or fluid. Epithelial ingrowth shows gray cell nests extending from the flap edge (see epithelial ingrowth), and a pre-existing stromal dystrophy may also become more visible after surgery.
Imaging in Central Toxic Keratopathy
Anterior segment OCT documents opacity depth and central thinning, while topography confirms flattening and tracks the hyperopic shift over time. In addition, serial pachymetry shows whether thinning has stabilized, but thin corneas can underestimate intraocular pressure, so interpret readings with caution.
Treatment of Central Toxic Keratopathy
No specific therapy has proven benefit, and intensive steroids do not appear to hasten recovery in typical cases. Therefore, most surgeons continue routine postoperative drops and observe.
Prolonged high-dose steroids also add risk of pressure rise and delayed healing. Some surgeons have tried flap lift with irrigation, but supporting evidence is weak.
Expected Course
Most cases improve slowly over several months, sometimes longer than a year. The opacity usually fades first, and then the hyperopic shift often regresses partly, although residual hyperopia may persist, while best corrected vision usually recovers well.
Counseling the Patient
Explain that the haze is not an infection and rarely needs surgery. Patients worry about permanence, so describe the slow natural improvement.
Also warn that spectacle prescriptions may change several times, and regular visits with measured topography help them see progress.
Enhancement Decisions
Avoid enhancement while the cornea is still changing, and wait until refraction and topography are stable on repeated visits. Then reassess residual stromal thickness and ectasia risk (see post-LASIK ectasia).
In many patients, stabilization removes the need for retreatment.
Pitfalls to Avoid
- Escalating steroids indefinitely for a quiet central opacity
- Skipping cultures when pain or infiltrates suggest infection
- Performing early enhancement for the hyperopic shift
- Trusting a single pressure reading on a thinned cornea
- Forgetting baseline pachymetry and topography at the first visit


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Sonmez B, Maloney RK. Central toxic keratopathy: description of a syndrome in laser refractive surgery. Am J Ophthalmol. 2007;143:420-427.
- Smith RJ, Maloney RK. Diffuse lamellar keratitis: a new syndrome in lamellar refractive surgery. Ophthalmology. 1998;105:1721-1726.
- Linebarger EJ, Hardten DR, Lindstrom RL. Diffuse lamellar keratitis: diagnosis and management. J Cataract Refract Surg. 2000;26:1072-1077.
- Moshirfar M, Hazin R, Khalifa YM. Central toxic keratopathy. Curr Opin Ophthalmol. 2010;21:274-279.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 13: Refractive Surgery. San Francisco: AAO; 2023.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.