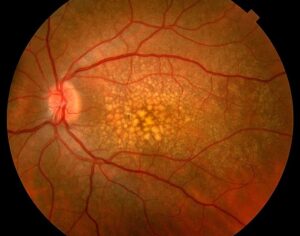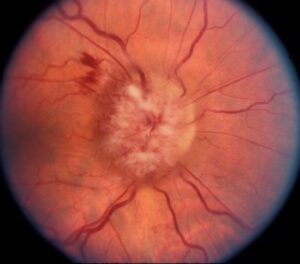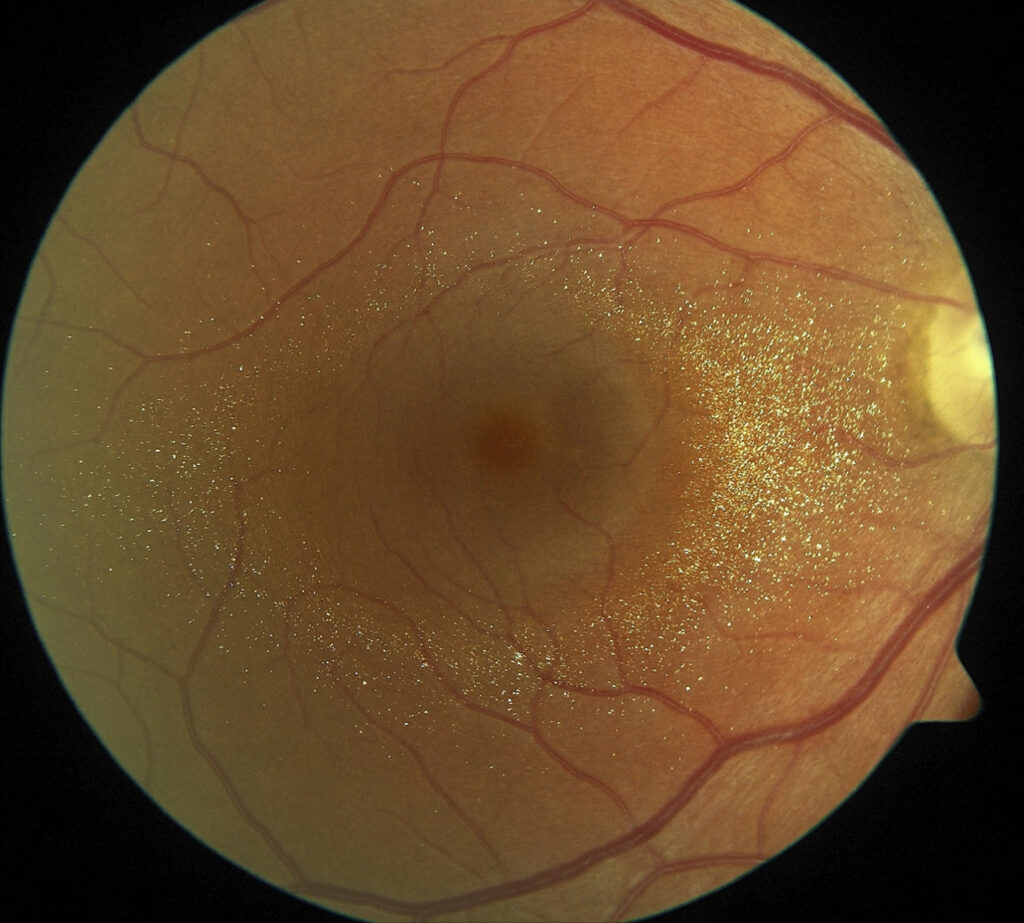
Crystalline retinopathy describes refractile deposits within the retina or retinal pigment epithelium (RPE).
The causes include drugs, emboli, metabolic disease and inherited dystrophies.
Therefore, crystal location, medication history and systemic findings guide the differential.
What Crystalline Retinopathy Looks Like
Examiners usually see small, glistening yellow or white points.
Many crystals sit around the fovea, while others spread across the posterior pole.
However, symptoms vary from none to blurred vision, metamorphopsia or night blindness.
Localizing Crystals on Examination
First, note whether the crystals lie in a ring, along vessels or diffusely.
Next, examine the cornea, because corneal crystals point toward cystinosis or Bietti dystrophy.
Finally, compare both eyes, since systemic and inherited causes tend to be bilateral.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteImaging in Crystalline Retinopathy
Near-infrared reflectance often makes crystals easier to see.
OCT also shows the depth of the deposits and any cavitation or atrophy.
In addition, fluorescein angiography can reveal leakage or nonperfusion.
History in Crystalline Retinopathy
A targeted history often narrows the list quickly.
For example, ask about cancer treatment, tanning pills, long-term antibiotics and intravenous drug use.
Also ask about kidney stones, renal failure and ethylene glycol exposure.
Family history and consanguinity may suggest an inherited disorder.
Drug Causes of Crystalline Retinopathy
Tamoxifen retinopathy typically produces inner retinal perifoveal crystals, sometimes with macular edema or foveal cavitation.
Canthaxanthin, used in oral tanning products, deposits in a ring around the macula.
Long-term nitrofurantoin has also been linked to crystals, although reports remain limited.
Vision may stay good, so the medication history carries much of the diagnostic weight.
Talc and Injection Drug Use
Injected crushed tablets can carry talc particles into the retinal circulation.
As a result, tiny refractile deposits collect in small perifoveal vessels.
Advanced cases may develop nonperfusion and neovascularization (see talc retinopathy).
Patients may not volunteer this history, therefore ask directly.
Oxalate Crystalline Retinopathy
Calcium oxalate crystals can occur in primary hyperoxaluria and in secondary oxalosis.
Secondary causes include methoxyflurane anesthesia, ethylene glycol poisoning and chronic renal failure.
Because the eye may reflect systemic oxalate burden, check renal function and involve nephrology.
Cystinosis and Retinal Crystals
Cystinosis results from defective lysosomal cystine transport.
Patients typically develop corneal crystals, and many also show RPE mottling.
Oral cysteamine lowers cellular cystine, while topical cysteamine treats the corneal deposits.
Sjogren-Larsson Syndrome
This autosomal recessive disorder arises from fatty aldehyde dehydrogenase deficiency.
Patients classically have ichthyosis, spasticity and intellectual disability.
Glistening perifoveal dots often accompany these features.
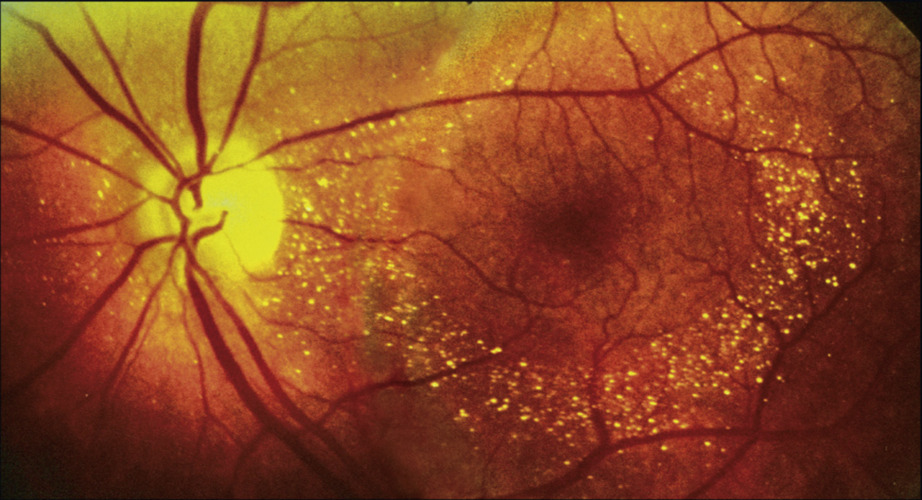
Bietti Crystalline Dystrophy
Biallelic CYP4V2 variants cause this progressive chorioretinal dystrophy.
Crystals scatter across the posterior pole, and some patients also have limbal corneal crystals.
Over time, RPE and choriocapillaris atrophy expand, while night vision and fields decline.
However, crystals may fade as atrophy advances, so their absence does not exclude late disease (see Bietti crystalline dystrophy).
Macular Telangiectasia in Crystalline Retinopathy
Macular telangiectasia type 2 can produce fine crystals in the superficial parafoveal retina.
Temporal graying, blunted venules and OCT cavitations also support this diagnosis.
Tamoxifen can produce a similar picture, so always review the medication list.
Mimics of Crystalline Retinopathy
Several refractile lesions can imitate true retinal crystals.
- Calcified drusen
- Cholesterol emboli at arteriolar bifurcations
- Hard exudates near leaking vessels
- Silicone oil droplets after retinal surgery
Workup for Crystalline Retinopathy
Start with a dilated examination, a corneal slit lamp assessment, OCT and near-infrared imaging.
Then add fluorescein angiography when you suspect leakage or ischemia.
Likewise, suspected inherited disease warrants electroretinography and genetic testing.
Treating the Underlying Cause
No single treatment removes retinal crystals, so management follows the diagnosis.
For tamoxifen, discuss findings with the oncologist before anyone changes therapy.
Systemic treatment of cystinosis or hyperoxaluria addresses the metabolic disease, although established retinal damage may not recover.
Gene therapy for Bietti dystrophy remains investigational.
Counseling the Patient
Explain that crystals are a sign, and that their cause determines the outlook.
In contrast, Bietti dystrophy usually progresses, so patients benefit from low vision support and genetic counseling.
Also tell patients to report new distortion promptly.
Follow-Up Planning
Follow-up depends on the cause and on visible activity.
However, edema, neovascularization or ischemia call for closer review.
Serial OCT and autofluorescence also help document progression.
Pitfalls to Avoid
- Do not skip the corneal examination in a patient with retinal crystals
- Never stop tamoxifen without consulting the oncologist
- Do not label refractile lesions as crystals before excluding emboli


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Drenser K, Sarraf D, Jain A, Small KW. Crystalline retinopathies. Surv Ophthalmol. 2006;51:535-549.
- Kaiser-Kupfer MI, Kupfer C, Rodrigues MM. Tamoxifen retinopathy: a clinicopathologic report. Ophthalmology. 1981;88:89-93.
- Li A, Jiao X, Munier FL, et al. Bietti crystalline dystrophy is caused by mutations in the novel gene CYP4V2. Am J Hum Genet. 2004;74:817-826.
- Tse DT, Ober RR. Talc retinopathy. Am J Ophthalmol. 1980;90:624-640.
- Small KW, Letson R, Scheinman J. Ocular findings in primary hyperoxaluria. Arch Ophthalmol. 1990;108:89-93.
- Gahl WA, Thoene JG, Schneider JA. Cystinosis. N Engl J Med. 2002;347:111-121.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.