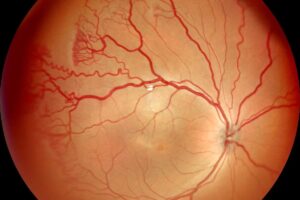
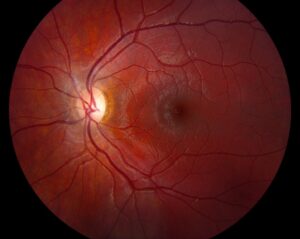
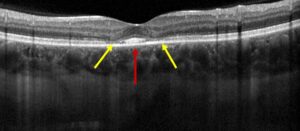
Fingolimod macular edema is a dose-related complication of an oral drug for relapsing multiple sclerosis.
It usually appears within the first three to four months and often responds to stopping the drug.
Therefore, a baseline and an early follow-up examination form the core of safe prescribing.
How Fingolimod Macular Edema Occurs
Fingolimod binds sphingosine-1-phosphate receptors, which also sit on vascular endothelial cells.
Also, receptor modulation may increase vascular permeability in the macula.
As a result, fluid accumulates in the retina, and vision blurs.
Jain and Bhatti reviewed the evidence and described a typical onset in the first months.
Incidence of Fingolimod Macular Edema
In the phase 3 trials, FREEDOMS and TRANSFORMS, macular edema occurred in under 1 percent at 0.5 mg.
It was more frequent at the higher 1.25 mg dose.
Zarbin and colleagues reviewed the ophthalmic data from these studies.
Because 0.5 mg is the approved dose, the absolute risk is low.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteRisk Factors for Fingolimod Macular Edema
- Diabetes mellitus (see diabetic macular edema)
- A history of uveitis (see uveitic macular edema)
- Higher doses and, possibly, older age
Patients with these factors need closer monitoring and a baseline optical coherence tomography.
Screening for Fingolimod Macular Edema
Examine the fundus and the macula before starting treatment.
Then repeat the examination three to four months after the start.
Also examine at any time when vision changes.
Add optical coherence tomography for patients with diabetes or prior uveitis.
Symptoms and Signs of Fingolimod Macular Edema
Many patients have no symptoms, so screening catches cases early.
Others report blurred or distorted central vision.
Because optic neuritis also occurs in multiple sclerosis, OCT helps to separate the two (see demyelinating optic neuropathy).
Management of Fingolimod Macular Edema
Stop the drug and discuss alternatives with the neurologist.
Edema resolves in most patients within weeks to months.
Also, topical steroids or nonsteroidal drops may speed recovery in persistent cases.
Finally, avoid rechallenge unless the neurologic benefit is compelling and the eye is monitored.
Other Ocular Concerns on Fingolimod
Patients with multiple sclerosis also develop optic neuritis and intermediate uveitis.
Therefore, unexplained visual loss deserves a full examination and not an assumption about the drug.
Also, infections such as herpes zoster ophthalmicus occur more often on immunomodulating drugs.
Because the list is long, take a careful history.
Newer S1P Modulators
Siponimod, ozanimod, and ponesimod act on the same pathway.
Their labels also carry warnings about macular edema.
Also, patients who switch between agents keep their risk factors.
Therefore, apply the same screening principles to the whole class.
Coordination With the Neurologist
Ask the neurologist to arrange the baseline examination before the first dose.
Then agree who performs the three-month review.
Also share the OCT results, since they help later decisions.
Because patients may see several clinicians, give them a written plan.
Patient Education
Tell patients to report blurred vision, distortion, or a dark spot promptly.
Also explain that the risk is low and treatable.
Because many do not notice early changes, stress the scheduled visits.
Pitfalls in Diagnosis
Edema in multiple sclerosis may come from pars planitis, which is more frequent in this disease.
Therefore, examine the vitreous and the peripheral retina before blaming the drug.
Also check the diabetic status and the blood pressure.
Key Points for the Clinician
Fingolimod macular edema is uncommon at the standard dose and usually reversible.
Also, a baseline and a three-month examination detect most cases.
Because diabetes and uveitis increase risk, monitor these patients more closely.
Imaging Findings
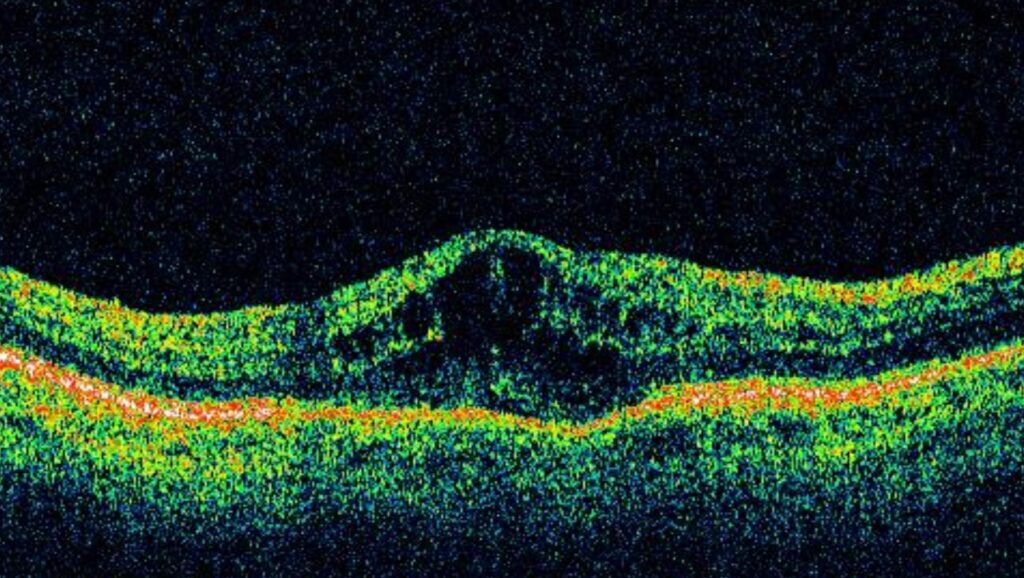
OCT shows intraretinal cysts in the central macula.
Also, the thickness map displays a rise in central subfield thickness.
Fluorescein angiography shows leakage in many cases, which separates it from nonleaking drug cysts.
Because both studies are widely available, use them together when the diagnosis is uncertain.
Special Situations
Pregnancy and breastfeeding affect the choice of drug, so coordinate with the neurologist.
Also consider patients with a single eye, since macular edema in that eye has a greater effect on daily life.
Therefore, monitor these patients with extra care.
Outcome After Stopping
Most patients recover vision within weeks to months of stopping the drug.
Also, a few have residual thinning of the macula.
Because early detection reduces the chance of lasting change, stick to the schedule.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Jain N, Bhatti MT. Fingolimod-associated macular edema: incidence, detection, and management. Neurology. 2012;78:672-680.
- Zarbin MA, Jampol LM, Jager RD, et al. Ophthalmic evaluations in clinical studies of fingolimod (FTY720) in multiple sclerosis. Ophthalmology. 2013;120:1432-1439.
- Kappos L, Radue EW, O’Connor P, et al. A placebo-controlled trial of oral fingolimod in relapsing multiple sclerosis. N Engl J Med. 2010;362:387-401.
- Cohen JA, Barkhof F, Comi G, et al. Oral fingolimod or intramuscular interferon for relapsing multiple sclerosis. N Engl J Med. 2010;362:402-415.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.