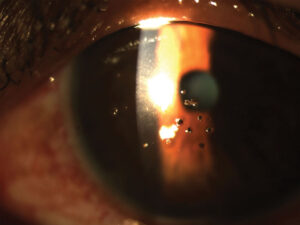
Nummular keratitis describes a recognizable pattern rather than a single disease: multiple small, round, coin-shaped (nummular, from the Latin for coin) subepithelial infiltrates scattered across the cornea, and while the term is most classically tied to a specific viral cause, recognizing it as a pattern that several distinct processes can produce is what keeps the differential diagnosis appropriately broad.
The Classic Association: Adenoviral Keratoconjunctivitis
The most well-recognized cause of nummular keratitis is epidemic keratoconjunctivitis, caused by adenovirus, in which multiple small, round, subepithelial infiltrates develop in the cornea, typically appearing during the second to third week after the onset of the acute conjunctivitis, well after the initial, most contagious phase of the infection has passed.
This delayed appearance reflects the immune-mediated nature of these infiltrates, representing an inflammatory response to viral antigen persisting in the corneal tissue rather than ongoing active viral replication at the time the infiltrates become visible, similar in underlying concept to the immune-mediated mechanism of herpetic disciform keratitis, though arising from a different virus and typically producing a different, multifocal pattern.
Clinical Features
- Multiple, discrete, round or coin-shaped, white-gray subepithelial infiltrates scattered across the cornea, typically sparing a completely clear surrounding stroma between lesions
- Reduced vision, glare, and photophobia correlating with the number, size, and central location of the infiltrates
- A preceding history of acute conjunctivitis, often with the characteristic features of adenoviral epidemic keratoconjunctivitis, including watery discharge, follicular conjunctival reaction, and preauricular lymphadenopathy, occurring one to a few weeks before the infiltrates develop
- Infiltrates can persist for months to occasionally years, and while many eventually fade, some patients experience a prolonged, relapsing course with recurrent infiltrate activity
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteOther Causes of a Nummular Pattern
While adenoviral keratoconjunctivitis is the classic and most commonly encountered cause, a similar multifocal, coin-shaped infiltrate pattern has been described in association with other conditions, and the broader clinical picture, particularly the presence or absence of a preceding viral conjunctivitis episode, helps direct the evaluation toward the correct underlying cause in a given patient.
Diagnostic Evaluation
- A history specifically asking about any preceding acute conjunctivitis episode, including its features and timing relative to the onset of visual symptoms, since this history is often the single most informative piece of information supporting an adenoviral cause
- Slit-lamp examination characterizing the number, size, depth, and distribution of the infiltrates
- Diagnosis is generally made clinically based on this characteristic pattern and history, without routine need for corneal scraping or culture when the presentation is classic for post-adenoviral infiltrates
Management
Observation
Many cases of adenoviral-associated nummular keratitis are mild and can be observed, particularly when visual symptoms are minimal, given the tendency for gradual spontaneous improvement over time in many patients.
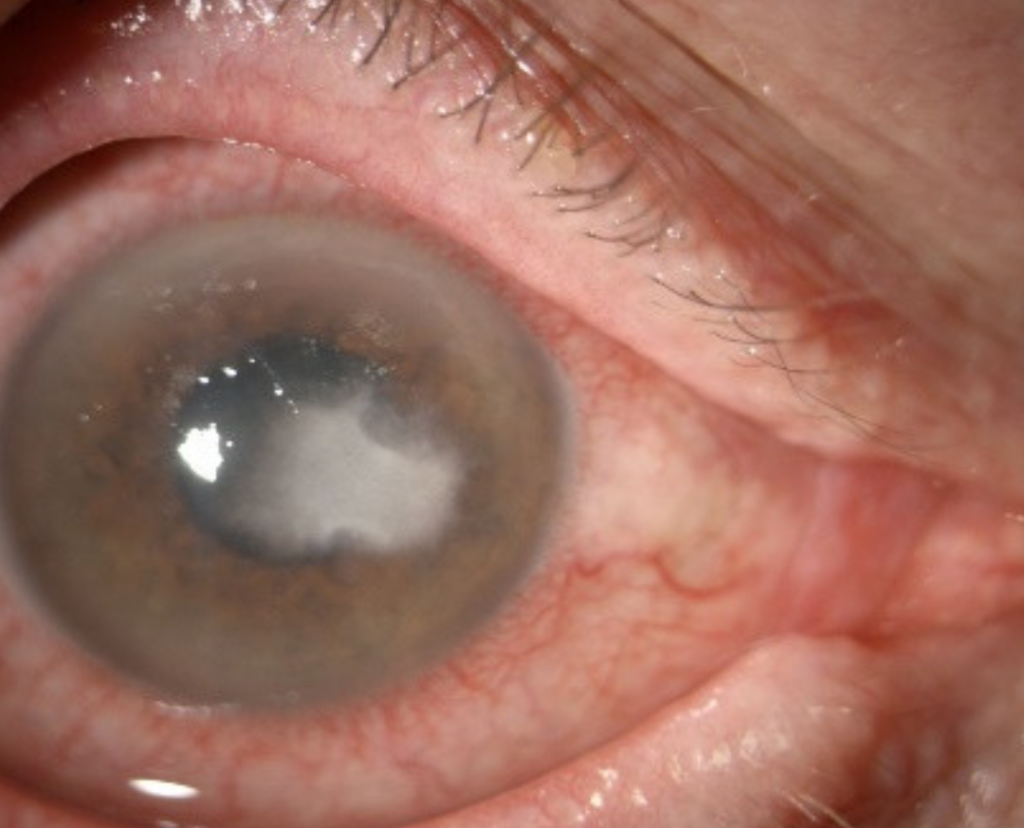
Topical Corticosteroids
For infiltrates causing significant visual symptoms, glare, or reduced acuity, particularly when centrally located, topical corticosteroids are effective at reducing the inflammatory infiltrates and improving symptoms, though they are generally used judiciously, at the lowest effective dose and duration, given the tendency for infiltrates to recur once steroids are tapered or discontinued in some patients.
Managing a Relapsing Course
Some patients experience a genuinely relapsing course, with infiltrates recurring each time corticosteroid treatment is tapered, requiring a more prolonged, carefully managed tapering schedule, and in some cases, alternative anti-inflammatory approaches such as topical cyclosporine have been used as a steroid-sparing option for chronic, relapsing disease.
Distinguishing the causes
Small round granular infiltrates may follow adenoviral keratoconjunctivitis, where they are subepithelial and appear one to two weeks after the red eye, or herpes zoster ophthalmicus, where they are often in the anterior stroma and occur with a history of a rash. A history of a recent conjunctivitis points to adenovirus, and a dermatomal rash or scars point to zoster. Look for decreased corneal sensation, which is typical of herpes viruses and supports that diagnosis.
Treatment and counselling
Many cases resolve with lubrication. Low-dose topical steroids are used when the infiltrates reduce vision, and the lowest effective dose is chosen, since the infiltrates may return when the steroid is stopped. Explain that resolution can take months, that glare and blur may fluctuate, and that scarring is minimal in most patients. Review the pressure when steroids are used.
Prognosis
The majority of patients with adenoviral-associated nummular keratitis experience gradual improvement over months, with most infiltrates eventually fading and good visual recovery in the great majority of cases.
A smaller subset experience a more prolonged, relapsing course requiring sustained management, but even in this group, the long-term prognosis for visual recovery is generally favorable with appropriately patient, carefully tapered anti-inflammatory treatment over time.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Dawson C, Jawetz E, Hanna L. Epidemic keratoconjunctivitis. Multiple viral etiologies. Arch Ophthalmol. 1970;84:497-502.
- Laibson PR. Current therapy for adenovirus keratoconjunctivitis. Trans Am Ophthalmol Soc. 1972;70:78-88.
- Jhanji V, Chan TC, Li EY, Agarwal K, Vajpayee RB. Adenoviral keratoconjunctivitis. Surv Ophthalmol. 2015;60:435-443.
- Hillenkamp J, Reinhard T, Ross RS, et al. The effects of cidofovir 1% with and without cyclosporin a 1% as a topical treatment of acute adenoviral keratoconjunctivitis. Ophthalmology. 2002;109:845-850.
Test yourself
A few questions straight from this article.
-
Nummular keratitis describes which corneal pattern?
The term denotes a pattern rather than one disease: multiple small, round, coin-shaped subepithelial infiltrates scattered across the cornea, which several processes can produce. -
Which condition is the most well-recognized cause of nummular keratitis?
Epidemic keratoconjunctivitis caused by adenovirus is the classic and most commonly encountered cause of the nummular infiltrate pattern. -
What accounts for the subepithelial infiltrates of post-adenoviral nummular keratitis?
The infiltrates are immune-mediated, an inflammatory response to viral antigen persisting in corneal tissue rather than ongoing viral replication when they become visible. -
What does the stroma between nummular corneal infiltrates typically look like?
The infiltrates are discrete white-grey lesions that typically spare a completely clear surrounding stroma between them. -
Which features characterize the conjunctivitis preceding post-adenoviral nummular keratitis?
The preceding acute episode typically carries the features of adenoviral epidemic keratoconjunctivitis: watery discharge, a follicular conjunctival reaction and preauricular lymphadenopathy. -
How is post-adenoviral nummular keratitis usually diagnosed?
When the presentation is classic, diagnosis rests on the characteristic infiltrate pattern plus the history of a preceding conjunctivitis, without routine scraping or culture. -
Which finding points to herpes zoster rather than adenovirus behind round corneal infiltrates?
Zoster infiltrates sit more often in the anterior stroma and come with a dermatomal rash or its scars, and decreased corneal sensation is typical of herpes viruses. -
Why are topical corticosteroids for nummular keratitis used at the lowest effective dose?
Steroids reduce the infiltrates effectively but they tend to recur as treatment is tapered or stopped, so the lowest effective dose and duration are used and pressure is reviewed. -
Which steroid-sparing option has been used for chronic, relapsing nummular keratitis?
For patients whose infiltrates recur each time steroids are tapered, topical cyclosporine has been used as an alternative anti-inflammatory, steroid-sparing approach. -
What is the usual prognosis of adenoviral-associated nummular keratitis?
Most patients improve gradually over months with the infiltrates fading and good visual recovery, and scarring is minimal in most, although a smaller subset run a prolonged relapsing course.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.