
DISEASE “Mooren’s Ulcer”
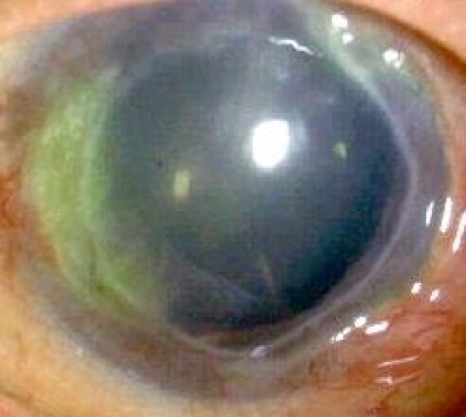
Mooren’s ulcer is characterized by painful peripheral corneal ulceration of unknown etiology. The disease generally begins with intense limbal inflammation and swelling in the episclera and conjunctiva.

Corneal changes begin within 2-3 mm from the limbus, first appearing as grey swellings that rapidly furrow, affecting the superficial one-third of the cornea and then proceeding circumferentially and centrally over 4-12 months.
The bed of the furrow becomes vascularized, with vessels advancing into the base of the undermined edges of the ulcers. These ulcers are often described as crescent-shaped and can leave behind an opaque and edematous central cornea.
Alternatively, they can completely consume the corneal stroma, replacing it with a thin fibrovascular membrane. Inflammation is not seen in the sclera adjacent to the peripheral ulcers, nor does it affect the underlying Descemet’s membrane.
Destruction of the cornea generally affects stromal tissue only, leaving behind an intact endothelium and epithelium.
The ulcer’s central edges can develop an overhanging edge with or without opacification, and cornea neovascularization can occur, extending from the limbus into the ulcer bed.
Neovascularization can occur up to the advancing edge of the ulcer but not beyond it.
Risk Factors of Mooren’s Ulcer
Risk factors for Mooren’s ulcer include corneal surgery, previous trauma, and infection. Although corneal surgery is a well-described risk factor, one study of 242 eyes affected by Mooren’s ulcer in South India described an interesting caveat.
An association has also been demonstrated between Mooren’s ulceration and hookworm infection. Certain helminths express receptors for calgranulin C, suggesting that there may be a helminthic antigen that cross-reacts with calgranulin C.
A previous infection has also been found to be a risk factor. An association with pyoderma gangrenosum has been described, implying potential common pathogenesis between the two processes since both pyoderma gangrenosum and Mooren’s ulcer show aseptic neutrophilic inflammation and both respond well to immunosuppression.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteMANAGEMENT of Mooren’s Ulcer
Benign MU often doesn’t need to be treated if it doesn’t cause pain or doesn’t have any risk of complications.
If treatment is needed, both benign and malignant MU may be treated using one or more of the following:
- topical treatments to keep tissue from degenerating
- antibiotics, such as moxifloxacin (Vigamox), to prevent infections
- interferon a2b for hepatitis C infections, sometimes combined with the antiviral medication ribavirin (Rebetron)
- resection, or surgical removal of tissues surrounding the ulcer
- cryotherapy, which involves freezing and surgically removing ulcer tissue
- tissue adhesion, which involves placing materials near the ulcer to stop it from spreading


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteREFERENCES
- Watson, P.G., Management of Mooren’s ulceration. Eye (Lond), 1997. 11 ( Pt 3): p. 349-56.
- Chen, J., et al., Mooren’s ulcer in China: a study of clinical characteristics and treatment. Br J Ophthalmol, 2000. 84(11): p. 1244-9.
- Srinivasan, M., et al., Clinical characteristics of Mooren’s ulcer in South India. Br J Ophthalmol, 2007. 91(5): p. 570-5.
- Sangwan, V.S., P. Zafirakis, and C.S. Foster, Mooren’s ulcer: current concepts in management. Indian J Ophthalmol, 1997. 45(1): p. 7-17.
- Taylor, C.J., et al., HLA and Mooren’s ulceration. Br J Ophthalmol, 2000. 84(1): p. 72-5.
- Gottsch, J.D., et al., Cytokine-induced calgranulin C expression in keratocytes. Clin Immunol, 1999. 91(1): p. 34-40.
- Liang, C.K., et al., Association of HLA type and Mooren’s Ulcer in Chinese in Taiwan. Br J Ophthalmol, 2003. 87(6): p. 797-8.
Test yourself
A few questions straight from this article.
-
Mooren's ulcer is characterised by which corneal presentation?
Mooren's ulcer is defined as painful peripheral corneal ulceration of unknown cause, opening with intense limbal inflammation and swelling of the episclera and conjunctiva. -
Where do the corneal changes of Mooren's ulcer first appear?
Changes begin within 2 to 3 mm of the limbus as grey swellings that rapidly furrow, involving the superficial one-third of the cornea. -
Over what period does Mooren's ulcer spread circumferentially and centrally?
After the initial furrowing near the limbus, the ulcer proceeds circumferentially and centrally over a period of 4 to 12 months. -
Which corneal layers does the destructive process of Mooren's ulcer typically affect?
Destruction generally affects stromal tissue alone, leaving an intact endothelium and epithelium, and Descemet's membrane is not involved. -
Which finding argues against Mooren's ulcer when assessing peripheral corneal ulceration?
In Mooren's ulcer the sclera next to the peripheral ulceration is not inflamed, so adjacent scleral inflammation points away from the diagnosis. -
Which group of risk factors is described for Mooren's ulcer?
The recognised risk factors listed are corneal surgery, previous trauma and previous infection, with corneal surgery the best described of the three. -
Which infection is linked to Mooren's ulceration through cross-reactivity with calgranulin C?
An association with hookworm infection is described: certain helminths express receptors for calgranulin C, suggesting a helminthic antigen that cross-reacts with it. -
What do Mooren's ulcer and pyoderma gangrenosum share that suggests a common pathogenesis?
Both conditions show aseptic neutrophilic inflammation and both respond well to immunosuppression, implying a shared underlying mechanism. -
When may a benign Mooren's ulcer reasonably be left untreated?
Benign disease often needs no treatment provided it is not painful and carries no risk of complications; treatment is reserved for symptomatic or threatening ulcers. -
Which systemic agent is listed for Mooren's ulcer in the setting of hepatitis C infection?
Interferon a2b is listed for hepatitis C infection, sometimes combined with the antiviral ribavirin, among the treatment options for Mooren's ulcer.
