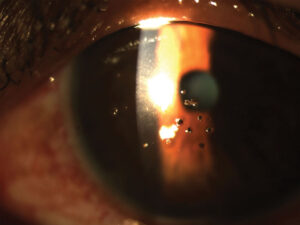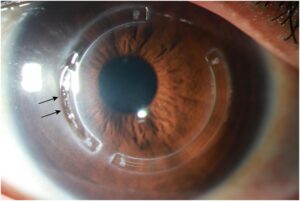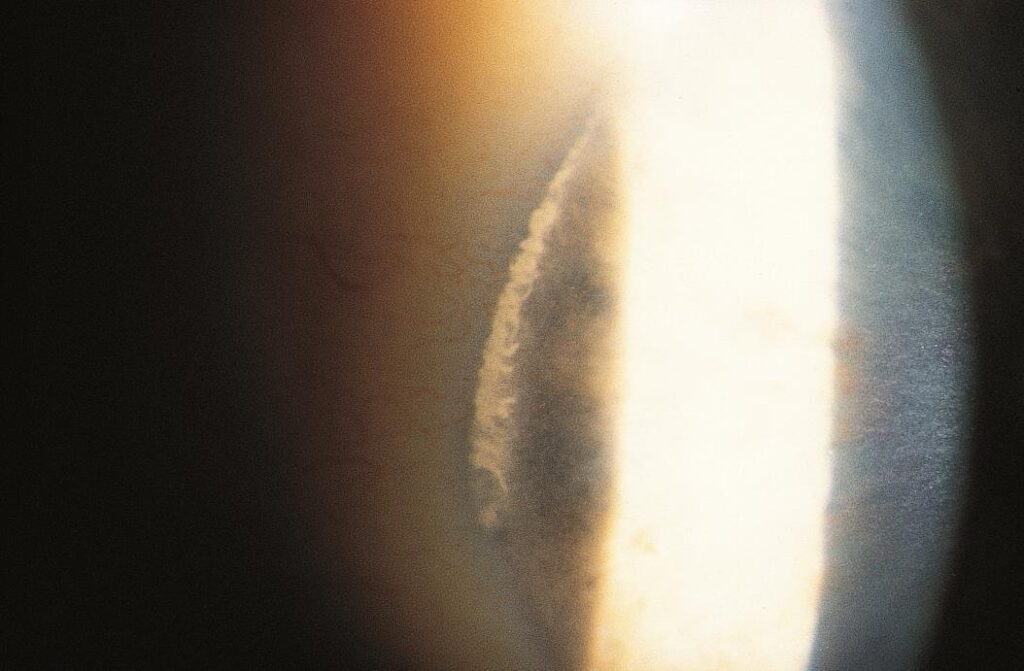
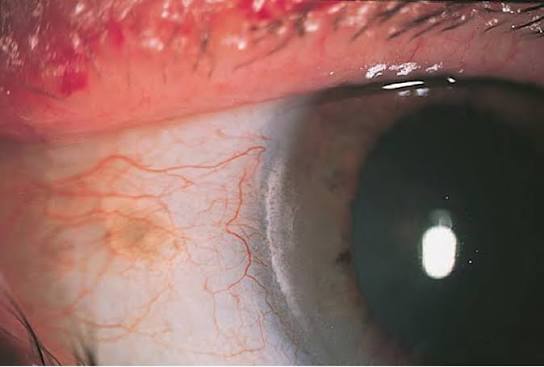
In many people over 40, a thin crescent of white or yellowish opacity appears at the edge of the cornea, nasally and temporally, in the area that is exposed between the eyelids.
This is the white limbal girdle of Vogt.
It is benign, and recognizing it saves patients from unneeded concern, since it is often confused with arcus senilis or with early corneal disease.
What it is
The girdle is a band of degenerative change in the superficial cornea, at the level of Bowman layer and the anterior stroma, near the limbus.
Histologically, it shows elastotic degeneration of collagen, and in some cases calcium deposition.
It develops in the interpalpebral zone, which is exposed to ultraviolet light and drying, and this is why it is more common in people who spend time outdoors.
Alfred Vogt, the Swiss ophthalmologist who pioneered slit-lamp examination, described the finding in the early twentieth century.
Two types
- Type I has a clear zone of cornea between the opacity and the limbus. It is made of a dense, white, crescent-shaped band with small, chalk-like flecks in it, and it can be quite striking.
- Type II has no clear zone. The opacity touches the limbus, and it appears as a hazy, white or gray crescent without flecks.
The two types are different in appearance, but they have the same clinical significance.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteWhere it occurs
The girdle lies horizontally at the 3 and 9 o’clock positions, in the part of the limbus exposed by the lids.
It is usually bilateral and symmetrical, although one eye may be more affected than the other.
It becomes more common and more visible with age, and it is found in a large proportion of elderly patients.
How to tell it from arcus senilis
Arcus (see arcus senilis) is a lipid deposit that starts at the top and bottom of the cornea, before forming a complete ring.
It lies deeper in the stroma, has a lucid interval from the limbus, and is a white-to-gray ring.
The girdle is at the sides, superficial, and is crescentic and not circumferential.
Arcus in a young person warrants a lipid profile (see arcus juvenilis), whereas the girdle does not.
Other conditions to consider include Terrien marginal degeneration, which causes gutter thinning, and band keratopathy, which starts at the same interpalpebral zone but extends to the central cornea (see band keratopathy).
Clinical significance
The girdle does not cause symptoms, does not affect vision, and does not require tests or treatment.
It does not signal metabolic or systemic disease.
Its importance lies in correct recognition, which allows a clinician to reassure the patient and avoid unnecessary referrals.
When to look further
- Opacity that is unilateral, asymmetric, or growing
- An irregular, vascularized, or elevated limbal lesion
- Pain, redness, or other signs of inflammation
- Opacity extending toward the center of the cornea
These features suggest other conditions, and the patient needs a full examination.
Management
Reassure the patient.
Record the finding in the notes, ideally with a photograph, to establish a baseline.
No treatment is needed.
Ultraviolet-protective eyewear is a reasonable general recommendation, since sun exposure may accelerate degenerative changes in the exposed cornea.
Appearance at the slit lamp
In Type I, the girdle looks like a crescent of white, chalky material with tiny flecks, separated from the limbus by a clear interval, and it lies in the superficial stroma and Bowman layer. In Type II, the opacity is thinner and hazy, and it extends right up to the limbus. Retroillumination shows the area as a dark or gray patch. The girdle may be bilateral and symmetrical, or one side may be more developed.
Why it forms
The anatomical site is the interpalpebral limbus, which is exposed to ultraviolet light and wind. Elastotic degeneration of collagen and deposition of calcium produce the whitish appearance. The same process underlies pinguecula and pterygium, and some patients with a girdle also have a pinguecula.
Practical points
- Avoid calling the girdle “arcus”, because it has different causes and implications
- Do not order lipid tests solely because of a girdle
- Reassure the patient and record the finding
- Remember that a girdle can be confused with limbal stem cell deficiency or with early band keratopathy when it is thick or irregular
A note on terminology
The terms “limbal girdle” and “arcus” are sometimes used interchangeably in notes. Using the correct term helps other clinicians understand what was seen, and avoids needless tests. When in doubt, describe the appearance: location, color, shape, and relation to the limbus.
Prognosis
Benign and stable.
The girdle may become more visible with time, but it does not threaten vision.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Hogan MJ, Alvarado JA, Weddell JE. Histology of the Human Eye. Philadelphia: Saunders; 1971.
- Krachmer JH, Mannis MJ, Holland EJ, eds. Cornea. 3rd ed. Philadelphia: Elsevier; 2011.
- Kanski JJ, Bowling B. Clinical Ophthalmology: A Systematic Approach. 7th ed. London: Elsevier; 2011.
- Yanoff M, Duker JS. Ophthalmology. 5th ed. Philadelphia: Elsevier; 2018.
Test yourself
A few questions straight from this article.
-
At which corneal depth does the white limbal girdle of Vogt lie?
The girdle is a band of degenerative change in the superficial cornea at the level of Bowman layer and the anterior stroma, close to the limbus. -
Which histological change underlies the white limbal girdle of Vogt?
Histology shows elastotic degeneration of collagen, with calcium deposition in some cases, in interpalpebral cornea exposed to ultraviolet light and drying. -
Where does the white limbal girdle of Vogt appear on the cornea?
The girdle lies horizontally at the 3 and 9 o'clock positions in the part of the limbus exposed between the lids, and is usually bilateral and symmetrical. -
What separates Type I from Type II white limbal girdle of Vogt?
Type I is a dense white flecked crescent separated from the limbus by a clear zone, while Type II is hazy and touches the limbus; both carry the same clinical significance. -
Which feature distinguishes the white limbal girdle of Vogt from arcus senilis?
Arcus is a deeper stromal lipid deposit that starts superiorly and inferiorly before completing a ring, whereas the girdle is superficial, crescentic and sits nasally and temporally. -
Which peripheral corneal finding in a young patient warrants a lipid profile?
Arcus in a young person warrants a lipid profile, whereas the limbal girdle of Vogt does not signal metabolic or systemic disease and needs no tests. -
Which condition starts in the same interpalpebral zone as the limbal girdle but extends centrally?
Band keratopathy begins in the same interpalpebral zone but extends toward the central cornea, unlike the girdle, which stays at the limbus. -
The degenerative process behind the limbal girdle of Vogt also underlies which lesions?
The same interpalpebral elastotic degeneration underlies pinguecula and pterygium, and some patients with a girdle also have a pinguecula. -
What is the appropriate management of a typical white limbal girdle of Vogt?
The girdle causes no symptoms and needs no treatment; the finding should be recorded, ideally with a photograph, and ultraviolet-protective eyewear is a reasonable general recommendation. -
What is the natural history of the white limbal girdle of Vogt?
The girdle is benign and stable; it may become more visible with age but it never threatens vision.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.