Glycemic control is the foundation of diabetic retinopathy prevention.
Landmark trials proved that lower HbA1c means less eye disease.
However, rapid change can briefly worsen the retina.
Why Glycemic Control Matters for the Retina
High glucose damages capillary walls and pericytes.
Leakage and ischemia follow over years.
Better control slows this process.
Therefore, eye outcomes depend on long-term glucose levels.
Evidence From the DCCT
The Diabetes Control and Complications Trial studied type 1 diabetes.
Intensive therapy lowered the risk of retinopathy onset by about three quarters.
It also slowed progression in patients with early disease.
So tight control is beneficial early.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteEvidence From the UKPDS
The UK Prospective Diabetes Study studied type 2 diabetes.
Intensive glycemic control reduced microvascular complications.
Blood pressure control also helped the retina.
Also, benefits persisted in long-term follow-up.
Metabolic Memory
Early good control gives lasting protection.
Early poor control leaves a lasting risk.
This is often called metabolic memory.
Therefore, start good control as early as possible.
ACCORD Eye Study
ACCORD Eye tested intensive glycemic control in high-risk type 2 patients.
Intensive control slowed retinopathy progression over four years.
Fenofibrate also reduced progression in the trial.
So lipids matter, too.
Early Worsening
A rapid fall in HbA1c can briefly worsen retinopathy.
This happened in a small group in DCCT.
The long-term effect was still beneficial.
However, patients with advanced disease need eye review before rapid change.
Glycemic Control and Newer Drugs
GLP-1 receptor agonists lower HbA1c quickly.
One trial of semaglutide reported more retinopathy complications.
The effect may reflect rapid glucose reduction.
Therefore, examine the eyes before and after starting these drugs.
Targets
Most adults aim for an HbA1c around seven percent.
Targets are individual and depend on age and comorbidity.
Aim for gradual reduction in those with advanced eye disease.
So coordinate with the physician.
Blood Pressure and Lipids
Control of blood pressure lowers progression.
Fenofibrate can reduce the need for laser in selected patients.
Smoking increases risk.
Also advise exercise and healthy weight.
Glycemic Control in Pregnancy
Pregnancy needs tight control, but too rapid a change is risky.
Retinopathy can worsen quickly.
Plan frequent eye examinations.
Therefore, coordinate care with obstetric and diabetes teams.
What Eye Doctors Can Do
Tell patients that the retina reflects glucose control.
Share findings with the primary physician.
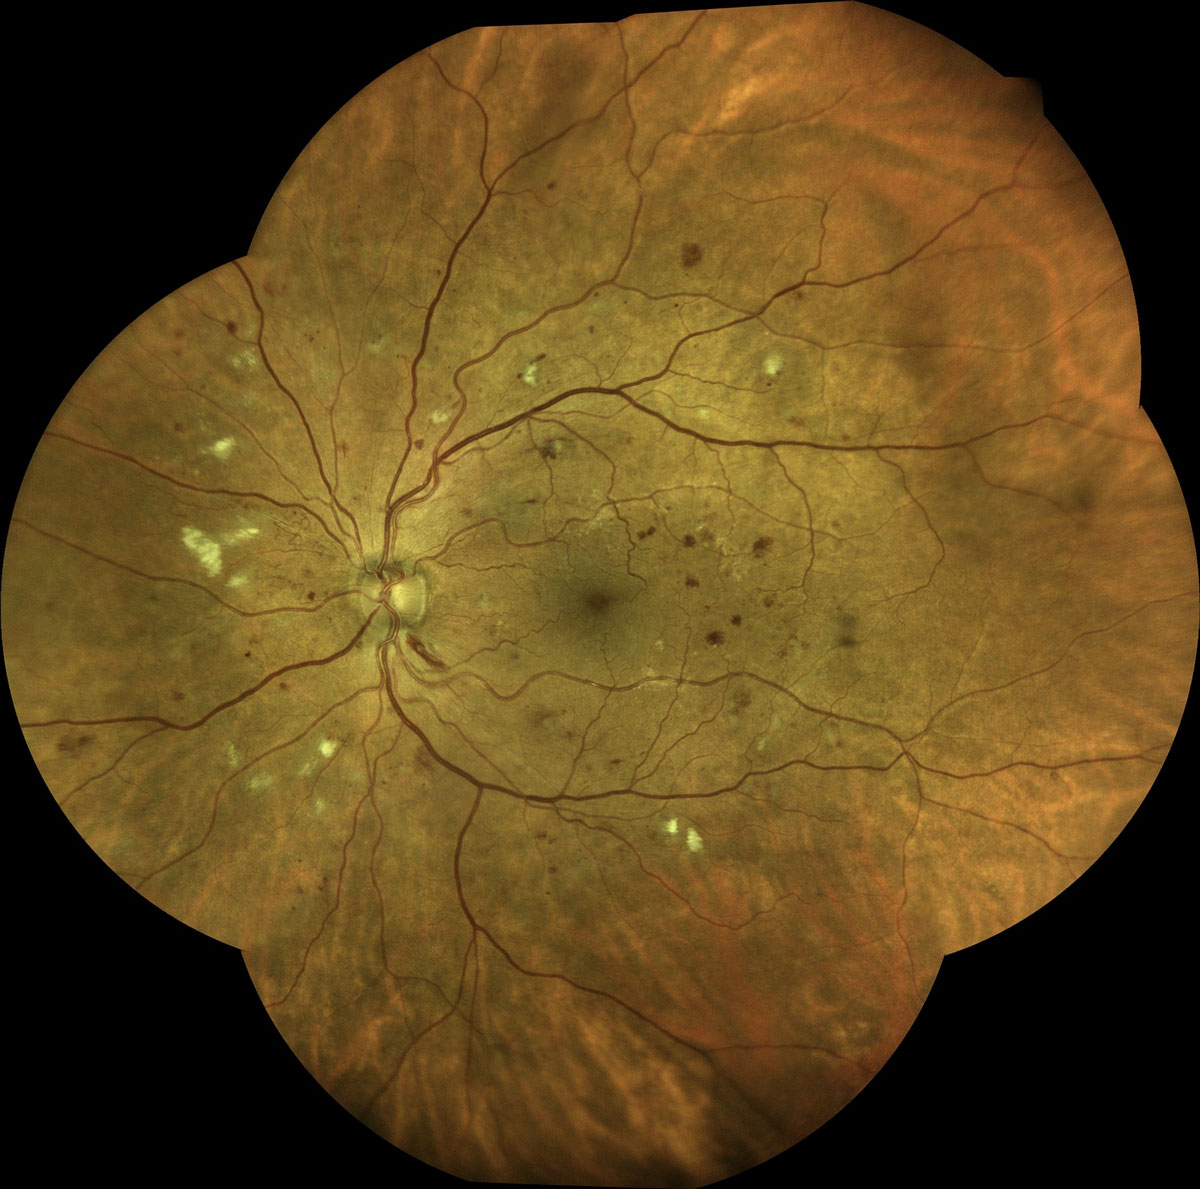
Motivate patients with their own images.
So the eye visit supports overall diabetes care.
Counseling Patients
Explain that better control protects vision.
Warn that eye exams remain necessary even with good control.
Encourage a stable, gradual approach.
Also address fears about needles and drugs.
Glycemic Control: Practical Summary
Aim for steady control and avoid sharp swings in advanced disease.
Review the retina before intensifying therapy.
Because lipids and pressure matter, manage them too.
Finally, repeat examinations on schedule.
Pitfalls to Avoid
- Do not assume good HbA1c ends the need for eye exams
- Never start rapid intensification without an eye review in advanced disease
- Avoid ignoring blood pressure
- Do not forget pregnancy
Glycemic Control and Time in Range
Continuous glucose monitors show time in range.
Higher time in range has been linked to less retinopathy.
Because HbA1c hides swings, these tools add detail.
Therefore, review glucose data during the retina visit.
Glycemic Control and Kidney Disease
Retinopathy and kidney disease often occur together.
If the kidneys are damaged, the retina is likely affected.
Because both reflect microvascular injury, screen for both.
Then share findings across specialties.
Glycemic Control in Older Adults
Older adults risk hypoglycemia with tight targets.
Aim for safe, individual goals.
Because some already have advanced eye disease, avoid abrupt changes.
Therefore, balance risks and benefits.
Glycemic Control and Anti-VEGF Response
Poor control reduces the benefit of injections.
When glucose improves, edema often settles.
Because injections are costly, support control as an adjunct.
So treat the metabolic problem as well as the eye.
Glycemic Control Support
Education, regular follow-up and access to medication help patients.
Peer support and digital tools also work.
If cost is a barrier, discuss options early.
Then refer to a diabetes educator.
Glycemic Control and Cataract Surgery
High glucose raises the risk of macular edema after surgery.
Optimize control before elective cataract surgery.
Because retinopathy can worsen after surgery, examine the retina first.
Therefore, plan follow-up for diabetic patients.
Glycemic Control: Key Message for Patients
Good control lowers the chance of vision loss.
It never replaces regular eye examinations.
Because both matter, plan both.
Finally, encourage steady progress over perfection.
For the latest studies, see the PubMed results for glycemic control.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Diabetes Control and Complications Trial Research Group. The effect of intensive treatment of diabetes on the development and progression of long-term complications in insulin-dependent diabetes mellitus. N Engl J Med. 1993;329:977-986.
- UK Prospective Diabetes Study Group. Intensive blood-glucose control with sulphonylureas or insulin compared with conventional treatment and risk of complications in patients with type 2 diabetes (UKPDS 33). Lancet. 1998;352:837-853.
- Chew EY, Davis MD, Danis RP, et al. The effects of medical management on the progression of diabetic retinopathy in persons with type 2 diabetes: the ACCORD Eye Study. Ophthalmology. 2014;121:2443-2451.
- Marso SP, Bain SC, Consoli A, et al. Semaglutide and cardiovascular outcomes in patients with type 2 diabetes. N Engl J Med. 2016;375:1834-1844.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.