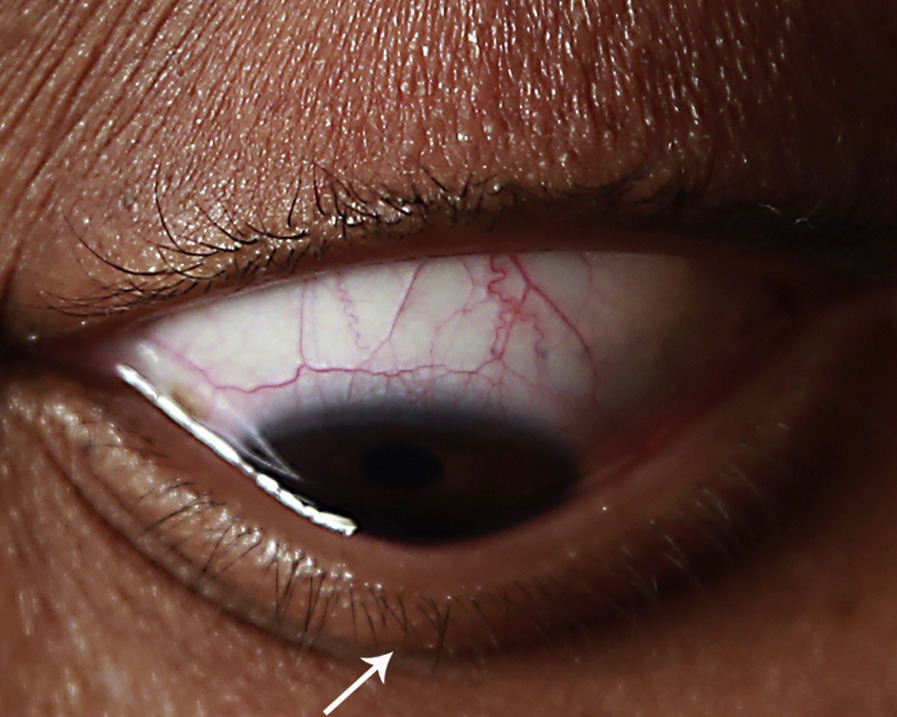
Munson’s sign is a V-shaped indentation of the lower eyelid when a patient with advanced keratoconus looks down.
The cone pushes the lid forward, so the lid margin follows the shape of the cornea.
Therefore, you can suspect advanced disease before you reach the slit lamp.
What Munson’s Sign Shows
Normally the lower lid sweeps in a smooth curve over the cornea on downgaze.
In a steep, protruding cone, the apex presses against the lid and creates an angle.
Because the cone has to be large and steep, the sign appears late in the disease.
Munson’s sign is specific for advanced ectasia but not sensitive for early disease.
How to Check Munson’s Sign
Seat the patient and ask them to look down slowly while you watch from the front and from the side.
Look at the lower lid margin, and note whether it forms a V instead of an even curve.
Also, check each eye separately, because keratoconus is often asymmetric.
Photograph the finding for the record.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteMunson’s Sign and Other External Signs
Several bedside signs accompany advanced keratoconus.
Rizzuti’s sign is a sharp conical light reflex near the nasal limbus when you shine a penlight from the temporal side.
The scissoring reflex on retinoscopy and the oil droplet reflex on distant direct ophthalmoscopy point to irregular astigmatism.
Because these signs depend on a steep cone, their absence says little in early disease, so use topography and tomography.
Management After Munson’s Sign
Advanced disease often needs rigid gas-permeable or scleral lenses, because spectacles cannot correct irregular astigmatism (see scleral lens fitting).
Corneal transplantation comes into play when lenses fail or scarring limits vision (see deep anterior lamellar keratoplasty).
Counsel the patient to avoid eye rubbing, since rubbing is linked to progression.
History Clues Behind the Sign
Ask about progressive blur, frequent spectacle changes, monocular diplopia and glare.
Also, ask about eye rubbing, atopy and family history.
Because Munson’s sign appears late, most patients report years of symptoms.
Examining the Cone
After you see the sign, look at the cornea for apical thinning, a Fleischer ring, Vogt’s striae and scarring.
Then measure keratometry and request tomography.
Also, check the fellow eye, because the disease is bilateral in most patients.
Documenting the Sign
A side-view photograph with the patient looking down records the angulation.
Also, a short video shows the lid movement.
Because the sign reflects the cone, a change over time suggests progression.
Risk of Hydrops
Advanced cones carry a risk of acute corneal hydrops, in which Descemet membrane breaks and the stroma swells (see acute corneal hydrops).
Therefore, tell patients to report sudden pain, redness or whitening of the cornea.
Pitfalls
Do not rely on the sign for screening, since it has low sensitivity.
Also, do not confuse a V-shaped lid with ptosis or lid retraction, so compare lid position in primary gaze.
Remember that a thick lid fold in downgaze can mimic the angle in some patients.
What the Sign Means for Contact Lens Use
A steep cone makes spectacle correction poor, so many patients rely on lenses by this stage.
Rigid lenses vault the cone, and scleral lenses clear it entirely.
Also, watch for apical touch, which can scar the cone.
When to Consider Surgery
Surgery is considered when contact lenses fail, when scarring limits vision, or after hydrops.
Deep anterior lamellar keratoplasty keeps the host endothelium and reduces rejection risk.
Penetrating keratoplasty remains an option when scars are deep.
Cross-Linking at an Advanced Stage
Cross-linking aims to stop progression and does not restore the shape.
Thin corneas may limit treatment, so measure the thinnest point (see crosslinking criteria).
Also, early treatment gives the best chance to preserve vision.
Patient Education
Explain that the cone is a structural change of the cornea.
Because progression often slows after the third or fourth decade, set realistic expectations.
Then schedule regular reviews.
Munson’s Sign and Visual Symptoms
Patients with this sign usually report glare, ghosting and poor night vision.
Also, they often complain of monocular diplopia that spectacles do not fix.
Because the cornea distorts the image, acuity falls with glasses and rises with a rigid lens.
Therefore, test vision with a pinhole and with an over-refraction through a rigid lens.
Lower Lid Mimics of Munson’s Sign
Other conditions can distort the lower lid on downgaze.
A chalazion or a lid tumor creates a focal bulge, and scars from old trauma can tether the margin.
Therefore, look at the cornea at the slit lamp to confirm that the cone causes the contour.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Rabinowitz YS. Keratoconus. Surv Ophthalmol. 1998;42:297-319.
- Gomes JAP, Tan D, Rapuano CJ, et al. Global consensus on keratoconus and ectatic diseases. Cornea. 2015;34:359-369.
- Jhanji V, Sharma N, Vajpayee RB. Management of keratoconus: current scenario. Br J Ophthalmol. 2011;95:1044-1050.
- Krachmer JH, Feder RS, Belin MW. Keratoconus and related noninflammatory corneal thinning disorders. Surv Ophthalmol. 1984;28:293-322.
Test yourself
A few questions straight from this article.
-
What is Munson's sign in keratoconus?
Munson's sign is a V-shaped angulation of the lower eyelid margin seen when a patient with advanced keratoconus looks down. -
What produces the lower lid angulation of Munson's sign in keratoconus?
A steep, protruding cone pushes the lid forward, so the margin follows the corneal shape and forms an angle instead of a smooth curve. -
What limits Munson's sign as a screening test for keratoconus?
The sign needs a large, steep cone, so it appears late: specific for advanced ectasia but insensitive early, when topography and tomography are needed. -
What is Rizzuti's sign in advanced keratoconus?
Rizzuti's sign is a sharp conical light reflex near the nasal limbus when a penlight is shone from the temporal side. -
In keratoconus, what do the scissoring reflex on retinoscopy and the oil droplet reflex indicate?
The scissoring reflex on retinoscopy and the oil droplet reflex on distant direct ophthalmoscopy both point to irregular astigmatism from the cone. -
Why does advanced keratoconus with Munson's sign usually need rigid gas-permeable or scleral lenses?
Spectacle correction is poor with a steep cone, so acuity falls with glasses and improves with a rigid lens; transplantation follows when lenses fail. -
What advantage does deep anterior lamellar keratoplasty offer in advanced keratoconus?
DALK preserves the host endothelium and reduces rejection risk, while penetrating keratoplasty remains an option when scars are deep. -
What happens in acute corneal hydrops complicating advanced keratoconus?
In hydrops Descemet membrane ruptures and the stroma swells, so patients should report sudden pain, redness or whitening of the cornea. -
What is the aim of corneal cross-linking in keratoconus?
Cross-linking aims to halt progression and does not restore shape; thin corneas may limit treatment, so the thinnest point is measured. -
A lower-lid contour change on downgaze could be Munson's sign or a chalazion. How is Munson's sign confirmed?
A chalazion or lid tumour creates a focal bulge and old scars can tether the margin, so the cornea is examined at the slit lamp to confirm the cone is responsible.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.