Optic neuritis MS risk is the question most patients ask after a first attack.
The eye usually recovers well, so the conversation quickly turns to the brain. Therefore, the ophthalmologist needs clear numbers and honest limits.
Why Optic Neuritis MS Risk Worries Patients
Many patients read online that optic neuritis always leads to multiple sclerosis, but that statement is incomplete.
Some patients develop MS within months, while others never have a second event. As a result, good counseling replaces fear with an individual estimate.
The ONTT Long-Term Data
The Optic Neuritis Treatment Trial followed patients with typical, isolated optic neuritis for 15 years. Overall, about half developed clinically definite MS during that period, but the baseline brain MRI divided the cohort sharply. For trial design and visual outcomes, see the Optic Neuritis Treatment Trial review.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteBrain MRI and Optic Neuritis MS Risk
Patients with one or more typical white matter lesions had a 15-year risk of about 72%, while patients with a normal brain MRI had a risk of about 25%.
Therefore, order gadolinium-enhanced brain MRI early in every new case, and request fat-suppressed orbital sequences to confirm nerve enhancement and its length.
Low-Risk Features With a Normal MRI
In the ONTT, some features predicted a low risk when the MRI showed no lesions. These included male sex, painless loss, no light perception, severe disc edema, hemorrhages and exudates. However, several of these features also suggest an atypical cause, so test antibodies before reassuring.
Typical Optic Neuritis MS Presentation
The classic patient is a young adult woman with unilateral subacute visual loss, and pain on eye movement usually precedes or accompanies the decline.
Then, the examiner finds a relative afferent pupillary defect, reduced color vision and a normal or mildly swollen disc. Recovery typically begins within a few weeks, even without treatment.
Red Flags That Point Away From MS
- Bilateral simultaneous or rapidly sequential involvement
- Severe loss to counting fingers or worse
- Marked disc edema with hemorrhages or exudates
- No recovery after several weeks
- Relapse when steroids are tapered
- Long-segment or chiasmal enhancement on MRI
- Systemic signs, such as intractable hiccups or transverse myelitis
AQP4 Antibody Testing
Aquaporin-4 IgG defines most cases of neuromyelitis optica spectrum disorder. These attacks are often severe, bilateral or chiasmal, and recovery may be poor. Some MS disease-modifying drugs may also worsen NMOSD, so test AQP4-IgG with a cell-based assay before anyone labels the patient as MS.
MOG Antibody Testing in Optic Neuritis MS Workup
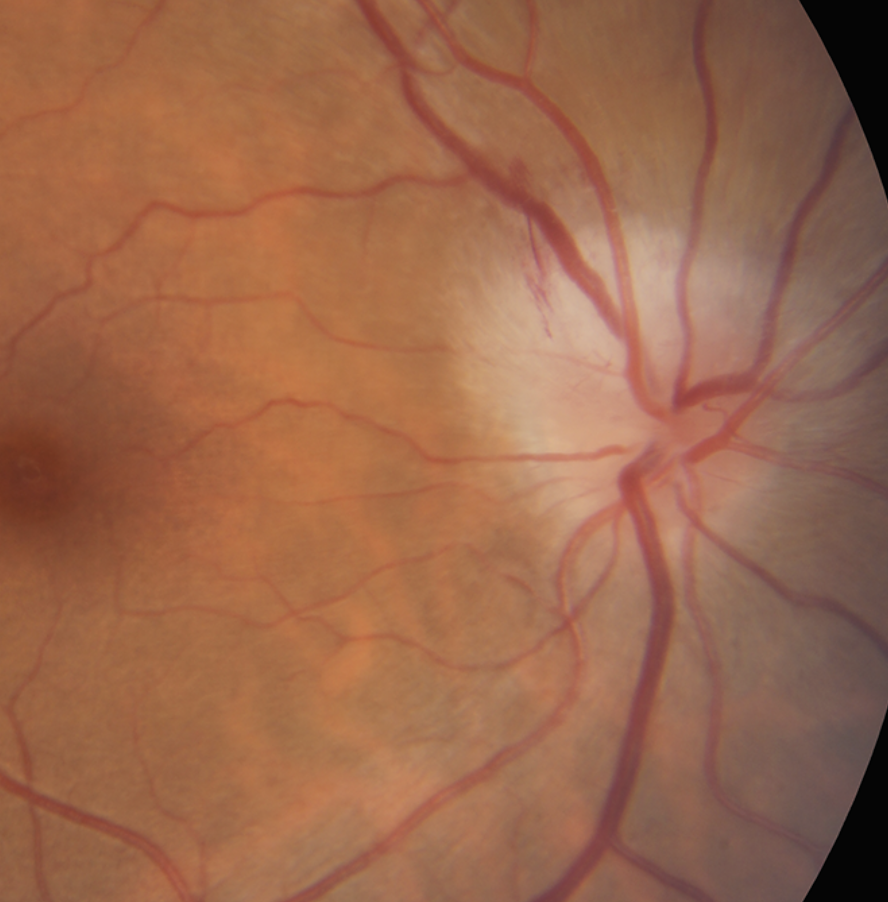
MOG-IgG associated disease often causes marked disc swelling and perineural enhancement, and it also tends to involve long segments of the anterior optic nerve.
Many neuro-ophthalmologists now test typical cases too, because a positive result changes management. However, interpret low MOG titers cautiously when the picture looks like MS (see MOG-IgG optic neuritis).
CSF and the McDonald Criteria
The 2017 McDonald criteria require dissemination in space and in time, although CSF oligoclonal bands can substitute for dissemination in time.
As a result, some patients meet MS criteria at the first attack, so next, the neurologist decides whether to start disease-modifying therapy.
Does Steroid Treatment Change Optic Neuritis MS Conversion?
In the ONTT, intravenous methylprednisolone reduced MS conversion over the first two years, but this benefit did not persist at later follow-up.
Oral prednisone alone gave no visual benefit and carried a higher recurrence rate. Therefore, present steroids as a way to speed recovery, without promising MS prevention.
How to Discuss Optic Neuritis MS Risk
First, explain that vision usually returns to good levels, and next, give the risk band that matches the MRI and antibody results.
Then, explain that a normal MRI lowers the risk without removing it. Finally, agree on a clear neurology referral and follow-up plan. Patients also cope better with a written summary, because anxiety limits recall.
Follow-Up After Optic Neuritis MS Counseling
Review vision, color and pupils during the first few months. OCT of the retinal nerve fiber layer documents thinning after the attack.
Ganglion cell layer thinning can also appear early and tracks function, while new symptoms in either eye, or new neurological symptoms, need urgent review.
Exclude Mimics Before Counseling
Ischemic, compressive, infectious and hereditary optic neuropathies can resemble optic neuritis. For example, painless loss in an older patient suggests ischemia. Because a wrong diagnosis leads to wrong counseling, review optic neuritis mimics before quoting MS numbers.
Pitfalls to Avoid
- Do not quote a single risk figure without the MRI result
- Never start MS drugs before AQP4 testing in atypical cases
- Do not ignore poor recovery after several weeks
- Avoid calling a normal MRI risk-free
- Do not skip neurology referral, even after full visual recovery


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Optic Neuritis Study Group. Multiple sclerosis risk after optic neuritis: final optic neuritis treatment trial follow-up. Arch Neurol. 2008;65:727-732.
- Beck RW, Cleary PA, Trobe JD, et al. The effect of corticosteroids for acute optic neuritis on the subsequent development of multiple sclerosis. N Engl J Med. 1993;329:1764-1769.
- Thompson AJ, Banwell BL, Barkhof F, et al. Diagnosis of multiple sclerosis: 2017 revisions of the McDonald criteria. Lancet Neurol. 2018;17:162-173.
- Wingerchuk DM, Banwell B, Bennett JL, et al. International consensus diagnostic criteria for neuromyelitis optica spectrum disorders. Neurology. 2015;85:177-189.
- Banwell B, Bennett JL, Marignier R, et al. Diagnosis of myelin oligodendrocyte glycoprotein antibody-associated disease: International MOGAD Panel proposed criteria. Lancet Neurol. 2023;22:268-282.
Test yourself
A few questions straight from this article.
-
In the ONTT, about what proportion of optic neuritis patients developed clinically definite MS over 15 years?
The Optic Neuritis Treatment Trial followed patients with typical, isolated optic neuritis for 15 years, and about half developed clinically definite MS. The baseline brain MRI divided the cohort sharply. -
In optic neuritis, what 15-year MS risk did the ONTT find for patients with a normal baseline brain MRI?
Patients with a normal brain MRI had a 15-year MS risk of about 25%, compared with about 72% for those with one or more typical white matter lesions. A normal MRI lowers the risk without removing it. -
Which imaging should be ordered early in every new case of optic neuritis to estimate MS risk?
The article advises early gadolinium-enhanced brain MRI in every new case. Fat-suppressed orbital sequences confirm nerve enhancement and its length. -
Which presentation is classic for typical optic neuritis related to MS?
The classic patient is a young adult woman with unilateral subacute visual loss, with pain on eye movement preceding or accompanying the decline. Painless loss in an older patient suggests ischemia instead. -
In optic neuritis, which finding is a red flag pointing away from MS?
Marked disc edema with hemorrhages or exudates is listed among the red flags pointing away from MS. A relative afferent pupillary defect and reduced color vision are part of the typical picture. -
Why should AQP4-IgG be tested with a cell-based assay in atypical optic neuritis before labeling it MS?
Aquaporin-4 IgG defines most NMOSD, which tends to cause severe, bilateral or chiasmal attacks with poor recovery. Some MS drugs may worsen NMOSD, so test before labeling the patient as MS. -
Which features are typical of MOG-IgG associated optic neuritis?
MOG-IgG associated disease often causes marked disc swelling and perineural enhancement, and tends to involve long segments of the anterior optic nerve. -
Under the 2017 McDonald criteria for MS, what can CSF oligoclonal bands substitute for?
The 2017 McDonald criteria require dissemination in space and in time, though CSF oligoclonal bands can substitute for dissemination in time. Some patients therefore meet MS criteria at the first attack. -
In the ONTT, how did intravenous methylprednisolone affect MS conversion after optic neuritis?
IV methylprednisolone reduced MS conversion over the first two years, but this did not persist later. Steroids should be presented as a way to speed recovery, not to prevent MS. -
In optic neuritis, what did the ONTT find about oral prednisone alone?
Oral prednisone alone gave no visual benefit and carried a higher recurrence rate. This supports counseling that steroids speed recovery without promising MS prevention.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.