Retinal drug toxicity means injury to the retina after exposure to a systemic, topical or intravitreal medication.
Most cases, however, fit one of five recognizable patterns, so sorting a drug by its pattern helps you predict the exam findings and plan screening.
Why Classify Retinal Drug Toxicity by Pattern
A medication list can contain dozens of names, however the fundus usually shows only a few injury patterns. As a result, the pattern guides the drug history, the imaging choice and the differential.
RPE and Photoreceptor Toxicity
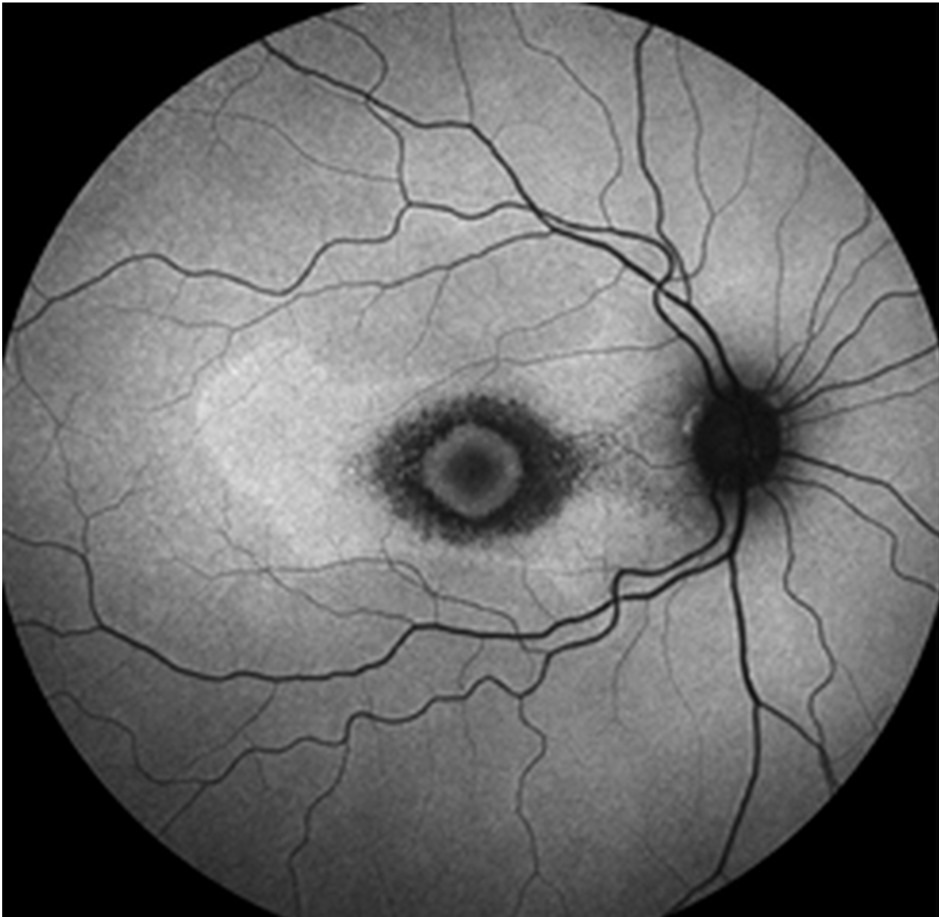
First, these drugs injure the retinal pigment epithelium or the outer retina directly, but early disease is often invisible on fundoscopy. Then, the examiner sees mottling, bull’s eye change or diffuse atrophy, and because the damage tends to be permanent, early detection has the greatest value.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteHydroxychloroquine in Retinal Drug Toxicity
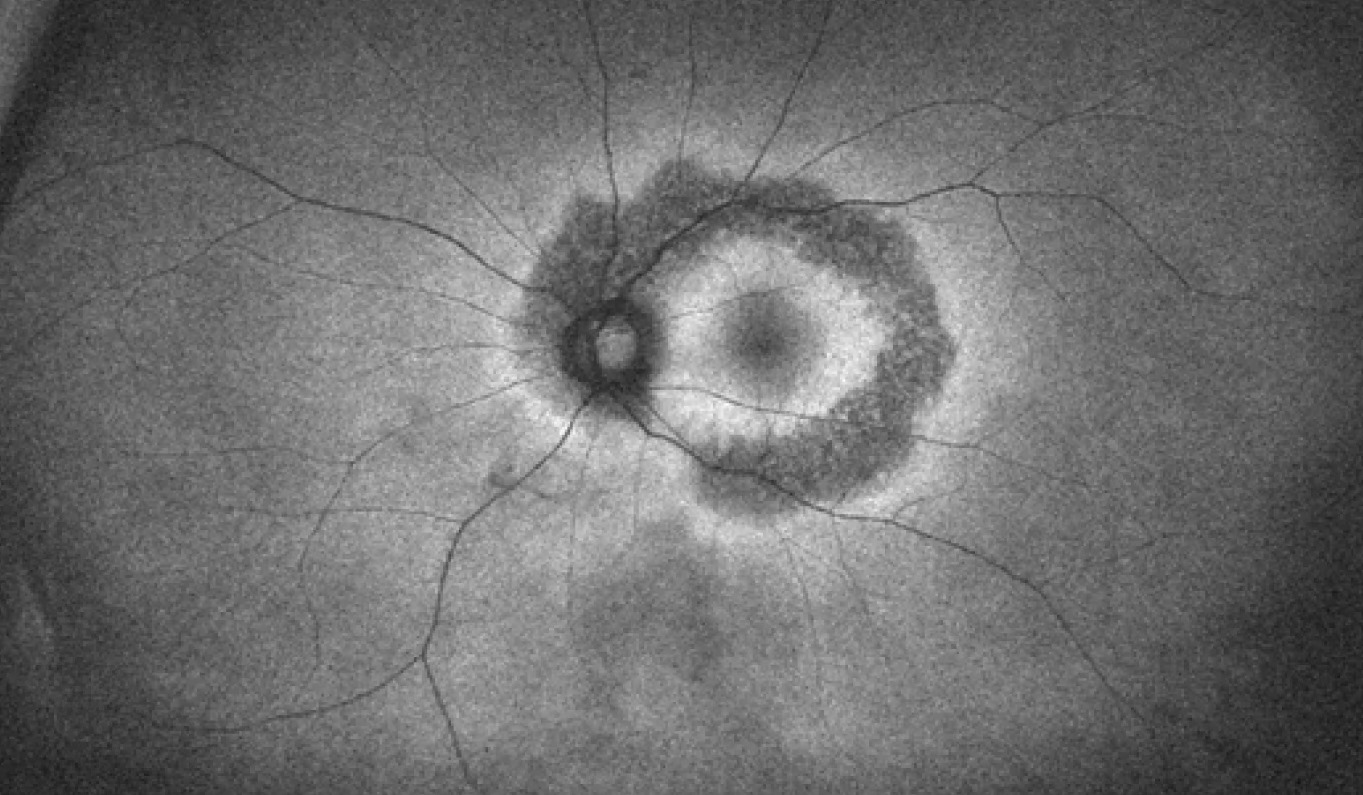
Hydroxychloroquine is the retinotoxic drug that clinicians screen most often, and the 2016 AAO recommendations advise a daily dose of 5 mg/kg real body weight or less. They also advise a baseline exam, then annual screening after five years of use.
Then, screening relies on SD-OCT and automated visual fields, with autofluorescence and mfERG as support, and in Asian patients, damage often starts in a pericentral ring, so wider field testing helps.
Phenothiazines, Pentosan and MEK Inhibitors
First, thioridazine can cause a salt and pepper pigmentary retinopathy, mainly at high doses, while chlorpromazine, however, more often deposits pigment in the lens and cornea.
In addition, pentosan polysulfate, used for interstitial cystitis, can produce a maculopathy that mimics pattern dystrophy. Finally, MEK inhibitors produce multifocal serous detachments that often resolve without stopping therapy.
Vascular Retinal Drug Toxicity
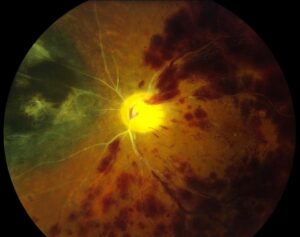
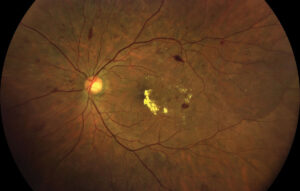
Vascular toxicity damages or blocks retinal vessels, so the examiner may see cotton wool spots, hemorrhages, arteriolar attenuation or frank occlusion. For example, interferon alfa can produce cotton wool spots and retinal hemorrhages, and in addition, people who inject crushed oral tablets may develop talc emboli and ischemia.
Quinine and Intraocular Aminoglycosides
Quinine overdose causes acute vision loss, then severe arteriolar narrowing and disc pallor, and electroretinography often shows inner retinal dysfunction (see quinine retinal toxicity).
Intravitreal gentamicin or amikacin can also cause macular infarction with whitening and hemorrhage. Therefore, avoid intraocular aminoglycosides when safer alternatives exist.
Crystalline Retinopathy Patterns
Crystalline toxicity leaves refractile deposits within the retina, and tamoxifen, for example, produces fine perifoveal crystals and sometimes foveal cavitation. Canthaxanthin, a tanning agent, also leaves golden crystals in a ring around the fovea, while talc, meanwhile, appears as glistening particles inside small arterioles.
Differential of Crystalline Retinal Drug Toxicity
However, crystals do not always point to a drug. For example, Bietti crystalline dystrophy, primary hyperoxaluria and cystinosis can look similar, so a careful drug and family history comes first.
Cystoid Macular Edema Patterns
Several drugs produce cystoid macular edema, sometimes with little or no angiographic leakage. For example, high dose niacin and taxanes such as paclitaxel cause this nonleaking pattern.
Glitazones and fingolimod can also cause macular edema, especially in diabetic or uveitic eyes (for general mechanisms, see cystoid macular edema).
Managing Cystoid Retinal Drug Toxicity
First, OCT confirms the edema and tracks central thickness, and then stopping the drug often allows resolution over weeks to months. However, any decision to stop chemotherapy belongs to the treating oncologist.
Inflammatory Retinal Drug Toxicity
Some drugs trigger uveitis or retinal vasculitis, and for example, rifabutin causes anterior uveitis, sometimes with hypopyon, especially with clarithromycin or fluconazole. Bisphosphonates can also cause anterior uveitis and scleritis, and in addition, cidofovir and immune checkpoint inhibitors may cause intraocular inflammation.
Intravitreal Agents and Occlusive Vasculitis
Intraocular drugs carry their own risks, and for example, reports link brolucizumab to retinal vasculitis with arterial occlusion. In addition, intracameral vancomycin can cause hemorrhagic occlusive retinal vasculitis after uneventful cataract surgery.
Drugs With Functional Retinal Effects
Some drugs alter retinal function with few fundus signs, and for example, vigabatrin causes concentric field loss that patients rarely notice (see vigabatrin toxicity). Sildenafil can also cause transient blue tinted vision and light sensitivity, while digoxin, finally, may produce yellow vision and glare at toxic levels.
Quick Reference by Pattern
- RPE and photoreceptor: hydroxychloroquine, chloroquine, thioridazine, pentosan polysulfate
- Serous detachment: MEK inhibitors
- Vascular: quinine, interferon alfa, talc, intraocular aminoglycosides
- Crystalline: tamoxifen, canthaxanthin, talc
- Cystoid edema: niacin, taxanes, glitazones, fingolimod
- Inflammatory: rifabutin, bisphosphonates, cidofovir, brolucizumab
Counseling Patients About Retinal Drug Toxicity
First, explain the specific risk without pushing the patient to stop a needed drug. Then, agree on a screening schedule and the tests you will use, and finally, coordinate any dose change with the prescribing physician.
Pitfalls to Avoid
- Do not rely on fundus appearance alone, because early hydroxychloroquine damage can be invisible
- Remember pericentral testing in Asian patients, because damage often starts outside the fovea
- Avoid labeling crystals as toxicity before you exclude dystrophy


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Marmor MF, Kellner U, Lai TY, Melles RB, Mieler WF. Recommendations on screening for chloroquine and hydroxychloroquine retinopathy (2016 revision). Ophthalmology. 2016;123:1386-1394.
- Pearce WA, Chen R, Jain N. Pigmentary maculopathy associated with chronic exposure to pentosan polysulfate sodium. Ophthalmology. 2018;125:1793-1802.
- Witkin AJ, Shah AR, Engstrom RE, et al. Postoperative hemorrhagic occlusive retinal vasculitis: expanding the clinical spectrum and possible association with vancomycin. Ophthalmology. 2015;122:1438-1451.
- Witkin AJ, Hahn P, Murray TG, et al. Occlusive retinal vasculitis following intravitreal brolucizumab. J Vitreoretin Dis. 2020;4:269-279.
- Bowling B. Kanski’s Clinical Ophthalmology: A Systematic Approach. 8th ed. Elsevier; 2016.
Test yourself
A few questions straight from this article.
-
What maximum daily hydroxychloroquine dose do the 2016 AAO recommendations advise to limit retinal toxicity?
The 2016 AAO recommendations advise a daily hydroxychloroquine dose of 5 mg/kg real body weight or less. -
What screening schedule do the 2016 AAO recommendations advise for patients taking hydroxychloroquine?
A baseline exam is advised, followed by annual screening after five years of hydroxychloroquine use. -
Why do Asian patients on hydroxychloroquine need wider-field screening tests?
In Asian patients hydroxychloroquine damage often starts in a pericentral ring outside the fovea, so wider field testing helps. -
Pentosan polysulfate, used for interstitial cystitis, causes a maculopathy that mimics which condition?
Pentosan polysulfate can produce a maculopathy that mimics pattern dystrophy, placing it among the RPE and photoreceptor toxicity drugs. -
Which tests form the core of hydroxychloroquine retinopathy screening?
Early damage is often invisible on fundoscopy, so screening relies on SD-OCT and automated visual fields, with autofluorescence and mfERG as support. -
Which picture follows quinine overdose as a vascular pattern of retinal drug toxicity?
Quinine overdose causes acute vision loss followed by severe arteriolar narrowing and disc pallor, with electroretinography often showing inner retinal dysfunction. -
Which crystalline retinopathy finding is linked to tamoxifen?
Tamoxifen produces fine perifoveal crystals and sometimes foveal cavitation, while talc appears as glistening particles inside small arterioles. -
Which inherited condition can mimic crystalline retinal drug toxicity?
Bietti crystalline dystrophy, primary hyperoxaluria and cystinosis can resemble drug crystals, so a careful drug and family history comes first. -
Which drugs cause cystoid macular edema with little or no leakage on fluorescein angiography?
High-dose niacin and taxanes such as paclitaxel cause a nonleaking cystoid macular edema pattern, and stopping the drug often allows resolution. -
Rifabutin-associated anterior uveitis, sometimes with hypopyon, is especially likely when combined with which drugs?
Rifabutin causes anterior uveitis, sometimes with hypopyon, especially when given with clarithromycin or fluconazole.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.