Scleral buckle versus vitrectomy is one of the most common decisions in retinal detachment surgery, and no single answer fits every eye.
Also, each operation approaches the break from a different side, with different strengths, different complications, and different recovery.
Trials and long experience help, but the choice rests on the features of the individual detachment and the skills of the surgeon.
Scleral Buckle Versus Vitrectomy: How the Two Operations Work
A scleral buckle indents the wall of the eye from outside with a silicone band or sponge, bringing the retinal pigment epithelium and choroid toward the break (see scleral buckle surgery).
The break is also sealed with cryotherapy or laser, and subretinal fluid is sometimes drained.
Vitrectomy removes the vitreous gel that exerts traction and fills the eye with gas or silicone oil, which tamponades the break from within (see pars plana vitrectomy).
Surgeons also apply laser or cryotherapy around the breaks, and the patient positions to keep the bubble against the break.
Scleral Buckle Versus Vitrectomy: Features That Favor a Scleral Buckle
- Young, phakic patients with a firmly attached, formed vitreous
- Inferior breaks, and dialysis without posterior vitreous detachment
- Multiple small breaks or lattice-related detachment in the periphery
- Eyes with a clear lens, since buckle surgery does not cause cataract
- Situations in which the patient cannot posture, because buckles do not depend on a bubble
The buckle avoids the cataract that follows vitrectomy in phakic eyes, which is a real advantage in younger patients.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteFeatures That Favor Vitrectomy
- Pseudophakic or aphakic eyes, where lens removal is not a concern
- Posterior or giant tears, and breaks that are hard to see or treat from outside
- Significant vitreous hemorrhage or media opacity
- Proliferative vitreoretinopathy and traction
- Macular hole detachments
- Eyes in which the retina cannot be reached with a buckle
Vitrectomy, in contrast, gives direct control of traction and allows repair of complex detachments (see proliferative vitreoretinopathy).
Scleral Buckle Versus Vitrectomy: What the Evidence Says
The Scleral Buckling versus Primary Vitrectomy in Rhegmatogenous Retinal Detachment study compared the two operations in randomized fashion.
Its results suggested that the best procedure depends on lens status, with differences between phakic and pseudophakic eyes.
A Cochrane review of simple detachments concluded that the evidence on which operation gives better anatomic and visual results is also of low quality, and that the choice remains a matter of judgment.
A randomized trial comparing pneumatic retinopexy with vitrectomy in selected detachments found better visual outcomes with pneumatic retinopexy, though it needed more reoperations (see pneumatic retinopexy).
In addition, newer surgical systems and techniques continue to change the balance, and the surgeon’s experience with each procedure matters.
Scleral Buckle Versus Vitrectomy: Complications to Weigh
- Buckle: diplopia from muscle disturbance, refractive change toward myopia, pain, extrusion, infection, and anterior segment ischemia
- Vitrectomy: cataract in phakic eyes, raised pressure, gas-related problems, endophthalmitis, and the need for positioning (see vitrectomy complications)
- Both: redetachment, proliferative vitreoretinopathy, epiretinal membrane, and macular edema
Combined Approaches
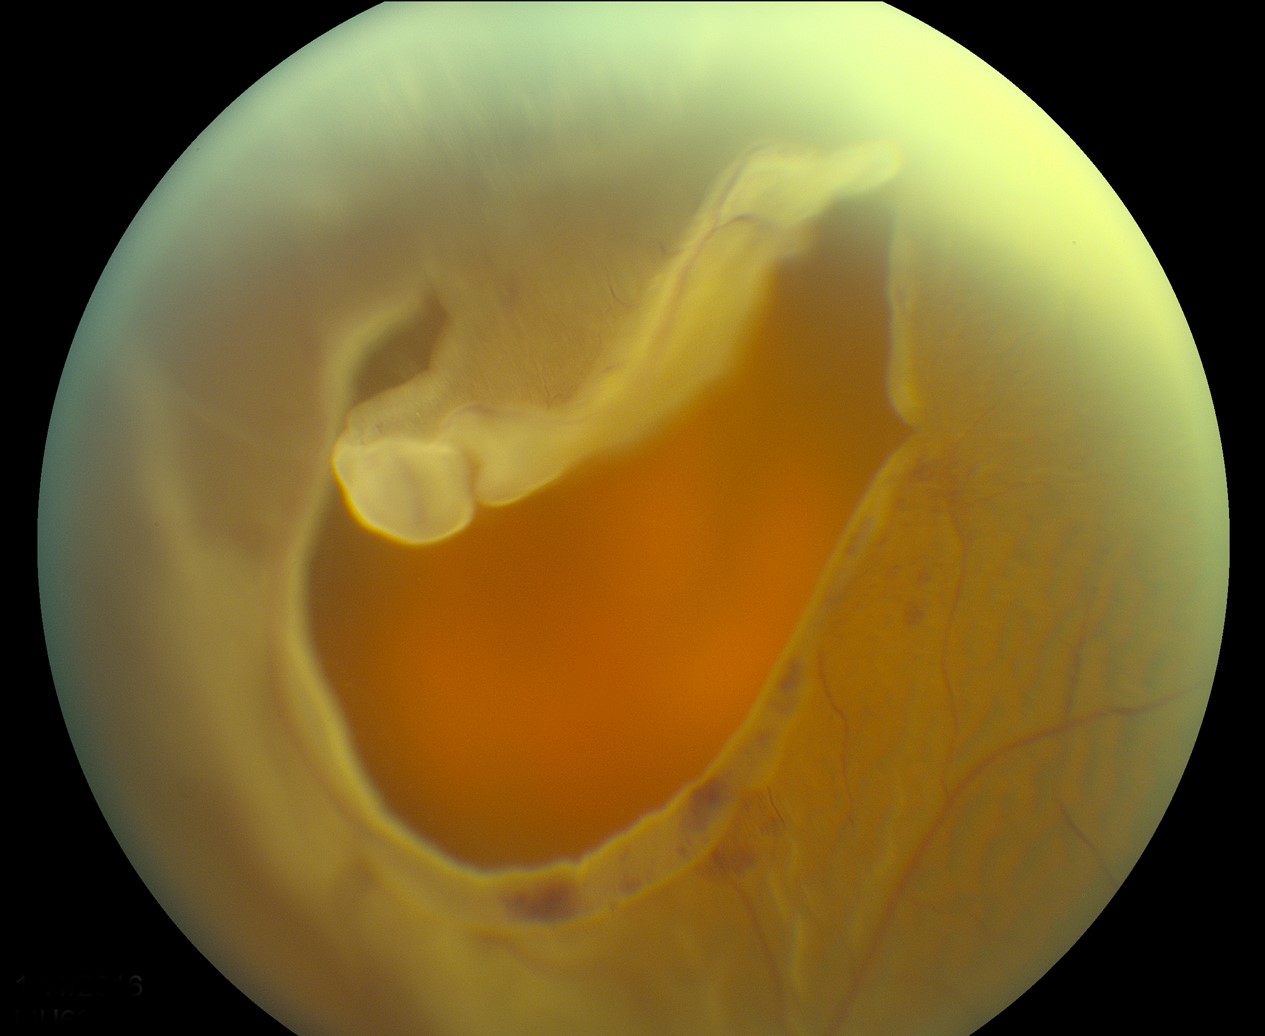
Some complex detachments call for a combination of a buckle and a vitrectomy, for example in inferior breaks with traction or in eyes with proliferative vitreoretinopathy.
Silicone oil may be used when long tamponade is needed.
It requires a later removal (see silicone oil tamponade).
Counselling
Finally, explain the reasons for the choice, the expected recovery, and the risks to the patient.
Mention that a second operation is sometimes needed, and that the final vision depends on the macula at the time of surgery.
Practical Decision Guide
A useful way to decide is to ask five questions in order.
- What is the lens status, and would cataract be a problem in this patient?
- Where are the breaks, and can they be reached and sealed from outside?
- Is there posterior vitreous detachment, and how much traction is present?
- Are there signs of proliferative vitreoretinopathy or a giant tear?
- Which procedure does the surgeon perform best, and which fits the patient’s ability to position?
Training and Skills
Scleral buckling is now performed less often in many centers, so there is concern about declining expertise.
Surgeons who maintain buckle skills can also offer the best procedure for the young phakic patient, and vitreoretinal fellowships increasingly emphasize both techniques.
Also, patients with a primary detachment benefit from a discussion that includes the option of each procedure and the reason for the recommendation.
Whatever the choice, the surgeon should also discuss the plan for lens status, positioning, and follow-up, and should document the reason for the decision in the operative note.
Review the outcomes in your own practice regularly, since personal results are the best guide to the choice for the next patient.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Heimann H, Bartz-Schmidt KU, Bornfeld N, et al. Scleral buckling versus primary vitrectomy in rhegmatogenous retinal detachment: a prospective randomized multicenter clinical study. Ophthalmology. 2007;114:2142-2154.
- Znaor L, Medic A, Binder S, et al. Pars plana vitrectomy versus scleral buckling for repairing simple rhegmatogenous retinal detachments. Cochrane Database Syst Rev. 2019;3:CD009562.
- Hillier RJ, Felfeli T, Berger AR, et al. The Pneumatic Retinopexy versus Vitrectomy for the Management of Primary Rhegmatogenous Retinal Detachment Outcomes Randomized Trial (PIVOT). Ophthalmology. 2019;126:531-539.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 12: Retina and Vitreous. AAO; current edition.
Test yourself
A few questions straight from this article.
-
How does a scleral buckle close a retinal break in rhegmatogenous retinal detachment?
A silicone band or sponge indents the eye wall from outside, bringing the pigment epithelium and choroid toward the break, which is sealed with cryotherapy or laser. -
How does vitrectomy repair a rhegmatogenous retinal detachment?
Vitrectomy removes the vitreous gel exerting traction and fills the eye with gas or silicone oil to tamponade the break from within. -
Why is a scleral buckle a real advantage for young phakic patients with retinal detachment?
Buckle surgery does not cause cataract, whereas vitrectomy in phakic eyes does, which matters most in younger patients. -
Which retinal detachment feature favours vitrectomy over a scleral buckle?
Vitrectomy is favoured by vitreous hemorrhage or media opacity, pseudophakia, posterior or giant tears, PVR and macular hole detachment. -
Which refractive change is a recognised complication of scleral buckle surgery?
Buckle complications include a refractive change toward myopia, diplopia, pain, extrusion, infection and anterior segment ischemia. -
A retinal dialysis without posterior vitreous detachment is best suited to which repair?
Inferior breaks and dialysis without posterior vitreous detachment are among the features favouring a scleral buckle. -
For a retinal detachment patient who cannot posture after surgery, which operation is favoured, and why?
Buckles do not rely on a gas bubble, so they suit patients who cannot posture; vitrectomy requires positioning to keep the bubble on the break. -
In the randomized trial comparing pneumatic retinopexy with vitrectomy for selected detachments, what did pneumatic retinopexy show?
The trial found better visual outcomes with pneumatic retinopexy, though it needed more reoperations than vitrectomy. -
When are scleral buckle and vitrectomy combined for retinal detachment?
Complex detachments, such as inferior breaks with traction or eyes with PVR, may need combined buckle and vitrectomy. -
After repair of a retinal detachment by either buckle or vitrectomy, final vision depends mainly on what?
Patients should be told a second operation is sometimes needed and that final vision depends on the macula at the time of surgery.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.