
Retinal cryotherapy, also called cryopexy, seals a retinal break by freezing it from the outside of the eye rather than treating it with light from inside.
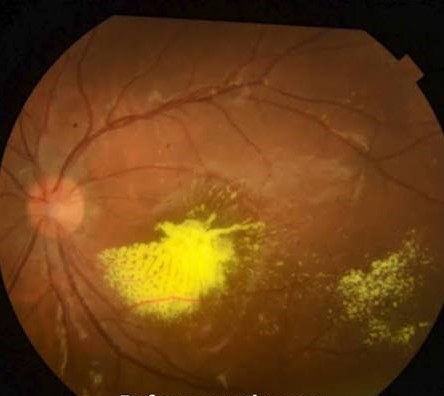
It produces the same biological end point as laser retinopexy, a firm chorioretinal adhesion around the break, but the route of delivery and the clinical situations where each is preferred are genuinely different.
Most retina specialists reach for laser first when the break is accessible, and reserve cryotherapy for the situations where laser cannot do the job as well.
Cryotherapy is also, historically, the older of the two techniques, and it remains the default in settings where a laser delivery system is not readily available.
Mechanism
A cryoprobe is applied to the external scleral surface directly over the break, and a freeze-thaw cycle is delivered under indirect ophthalmoscopic visualization to confirm accurate placement.
Ice crystal formation within the retinal pigment epithelium and outer retina disrupts cell membranes, and the wound-healing response that follows produces a chorioretinal scar functionally equivalent to a laser burn.
Unlike laser, where the effect is confined to the point of light absorption, a cryotherapy freeze spreads out somewhat within the tissue, which is one reason the resulting scar tends to be larger and more diffusely pigmented than a laser burn of comparable clinical intent.
Indications
- Breaks located very far anteriorly, near the ora serrata, where a laser delivery system cannot achieve a direct, centered view
- Breaks obscured by vitreous hemorrhage or a hazy view that would prevent safe laser aiming but still allow external localization with scleral depression
- Any break being treated during a scleral buckle procedure, since the sclera is already exposed and cryotherapy avoids an additional separate laser session
- Breaks in eyes where pupillary dilation or media clarity is poor enough that transpupillary laser delivery is simply not practical
Cryotherapy is generally avoided as a first choice when laser is equally accessible, largely because of its less favorable side-effect profile around pain, inflammation, and the theoretical risk of seeding viable retinal pigment epithelial cells into the vitreous.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteTechnique
The surgeon localizes the break externally by indenting the sclera with the cryoprobe tip while watching the corresponding indentation appear internally through the indirect ophthalmoscope.
Freezing is continued until a visible white, ice-ball reaction is seen to surround the break with an adequate margin, then the probe is allowed to thaw fully before it is moved or removed, since pulling on a still-frozen probe can tear the retina it is meant to protect.
Multiple applications are used to encircle a larger tear completely, in the same way a laser barrier requires a confluent ring rather than a single spot.
Most cryotherapy for a routine peripheral break is performed under local or topical anesthesia with sedation as needed, though extensive treatment or a very apprehensive patient occasionally warrants a regional block.
Comparison With Laser Retinopexy
Cryotherapy causes more breakdown of the blood-retinal barrier and a more pronounced postoperative inflammatory response than laser, which translates clinically into more discomfort and a theoretically higher risk of stimulating proliferative vitreoretinopathy when used over a large area.
Laser burns are more discrete and easier to titrate spot by spot, while a cryotherapy freeze is more of an all-or-nothing application over a given area, which is part of why laser is favored whenever direct visualization allows it.
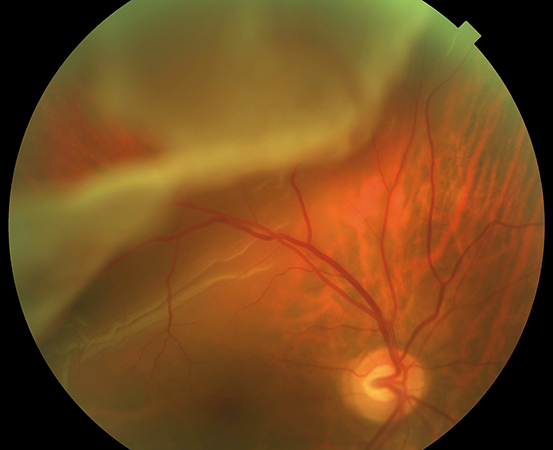
Neither modality treats subretinal fluid, and the same limitation that applies to laser retinopexy applies here: a break with a meaningful cuff of fluid underneath it needs a reattachment procedure, not cryotherapy alone.
Complications
- Postoperative pain and chemosis, generally more pronounced than after an equivalent laser treatment
- Choroidal effusion or hemorrhage from vigorous or repeated freeze-thaw cycles over a large area
- Dispersion of viable retinal pigment epithelial cells into the vitreous cavity, a recognized contributor to proliferative vitreoretinopathy when cryotherapy is used extensively
- Undertreatment from an inaccurately localized freeze, leaving a gap in the barrier around the break
Follow-Up
Patients are examined within one to two weeks to confirm the treated area has developed a stable, pigmented chorioretinal scar and that no new subretinal fluid has appeared.
New or worsening flashes, a new field defect, or any sense of a curtain progressing across the vision after treatment should prompt an urgent re-examination rather than waiting for the scheduled visit.
As with laser retinopexy, the fellow eye deserves a careful dilated look at the same visit, since the predisposing factors behind one eye’s break are frequently present bilaterally.
Patients should also be counseled that transient floaters and mild discomfort over the treated area are expected for a few days, so that a normal postoperative course is not mistaken for a complication.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Wilkinson CP, Rice TA. Michels’ Retinal Detachment.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 12: Retina and Vitreous.
- Wilkinson CP. Evidence-based analysis of prophylactic treatment of asymptomatic retinal breaks and lattice degeneration. Ophthalmology.
- Glaser BM, Vidaurri-Leal J, Michels RG, Campochiaro PA. Cryotherapy during surgery for giant retinal tears and intravitreal dispersion of viable retinal pigment epithelial cells. Ophthalmology.
Test yourself
A few questions straight from this article.
-
How does retinal cryotherapy deliver treatment to a peripheral retinal break?
Cryopexy seals a break from outside the eye: a cryoprobe on the sclera over the break delivers a freeze-thaw cycle, reaching the same end point as laser by a different route. -
Which process creates the chorioretinal adhesion produced by retinal cryotherapy?
Ice crystal formation in the retinal pigment epithelium and outer retina breaks cell membranes, and the wound-healing response that follows lays down a chorioretinal scar. -
How does a cryotherapy scar compare with a laser burn of comparable clinical intent?
A freeze spreads through tissue rather than staying at a point of light absorption, so the resulting scar is broader and more diffusely pigmented than a discrete laser burn. -
Which clinical situation favours cryotherapy over laser for sealing a retinal break?
When haemorrhage or media haze prevents safe laser aiming, scleral depression can still localise the break externally, and cryotherapy can then be delivered accurately. -
How does the surgeon localise a retinal break while performing cryotherapy?
The probe tip indents the sclera while the surgeon watches the indentation appear internally through the indirect ophthalmoscope, confirming the freeze is centred on the break. -
Which visible endpoint tells the surgeon a cryotherapy application is adequate?
Freezing continues until a white ice-ball reaction is seen to encircle the break with an adequate margin, and larger tears need several applications to close the ring. -
Why must a cryoprobe be allowed to thaw fully before it is moved or removed?
The frozen probe is adherent to the tissue, so moving it before complete thaw risks tearing the very retina the treatment is meant to protect. -
Compared with laser retinopexy, retinal cryotherapy characteristically produces which postoperative difference?
Cryotherapy breaks down the blood-retinal barrier more and provokes a stronger postoperative inflammatory reaction, so discomfort and chemosis are more pronounced than after laser. -
Which consequence of extensive retinal cryotherapy is recognised as contributing to proliferative vitreoretinopathy?
Extensive freezing can release viable retinal pigment epithelial cells into the vitreous cavity, and these cells are a recognised driver of proliferative vitreoretinopathy. -
What should patients be told to expect in the first days after retinal cryotherapy?
Counselling patients that a few days of floaters and mild soreness are normal prevents an ordinary postoperative course from being mistaken for a complication.
