
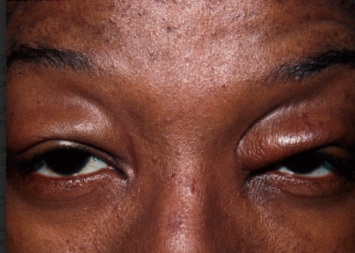
Blepharochalasis is a rare, recurrent inflammatory disorder of the eyelids characterized by repeated episodes of painless eyelid edema, typically beginning in childhood or early adulthood, that eventually leaves the eyelid skin thin, redundant, and atrophic.
It is easily confused with the far more common dermatochalasis of aging, though the two conditions differ fundamentally in mechanism, age of onset, and natural history, and treating one as if it were the other leads to suboptimal surgical outcomes.
Because the condition is rare and its earliest episodes can look like a simple, self-resolving allergic swelling, many patients experience several unexplained flares over years before a clinician recognizes the recurring pattern and connects it to blepharochalasis specifically.
Pathogenesis
The precise cause of blepharochalasis remains incompletely understood, though it is generally considered a localized inflammatory process, with some evidence pointing toward abnormal elastin degradation within the eyelid tissue during each inflammatory episode.
Each recurrent bout of edema is thought to cause cumulative, incremental damage to the skin’s elastic and connective tissue framework, which is why repeated episodes — rather than any single flare — are what ultimately produce the characteristic thin, redundant, atrophic skin seen once the active phase has burned out.
Clinical Course
The disease typically progresses through an active inflammatory phase in the first two to three decades of life, marked by recurrent, self-limited episodes of eyelid swelling that can last days to weeks and recur unpredictably over years, followed by a quiescent phase in which the acute swelling episodes become less frequent and eventually stop, leaving behind the permanent structural changes accumulated from repeated bouts of edema.
This biphasic course — active recurrent inflammation followed by eventual burnout with residual damage — is one of the more distinctive features separating blepharochalasis from other eyelid conditions.
Individual episodes are typically painless and not associated with fever or other systemic symptoms, which helps distinguish an acute flare from an infectious or more broadly inflammatory process requiring urgent treatment, even though the swelling itself can look dramatic at the time.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteResidual Findings After Repeated Episodes
- Thin, redundant, wrinkled (“cigarette paper”) eyelid skin
- Loss of orbital fat, sometimes producing a hollowed, prematurely aged appearance out of proportion to the patient’s actual age
- Ptosis, from stretching and attenuation of the levator aponeurosis after repeated episodes of edema
- Canthal tendon laxity in more severe, longstanding cases
- Visible, sometimes prominent, blood vessels through the thinned skin
The combination of these residual changes can significantly affect both function (superior visual field loss from ptosis and dermatochalasis) and appearance, and is what ultimately brings many patients to surgical evaluation once the active inflammatory phase has settled.
Differential Diagnosis
- Dermatochalasis — age-related skin redundancy without a preceding history of recurrent inflammatory swelling episodes, developing gradually in older adults rather than through discrete recurrent bouts starting in youth
- Angioedema — acute, can be recurrent, but typically more diffuse facial involvement and often associated with an identifiable trigger or underlying allergic/hereditary cause
- Thyroid eye disease — eyelid and periorbital swelling, but with other characteristic features (lid retraction, proptosis, restrictive myopathy) and abnormal thyroid function
- Chronic blepharitis with lid edema — associated with lid margin disease and typically does not produce the same degree of skin atrophy over time
- Ascher syndrome — blepharochalasis combined with double lip and, in some cases, non-toxic thyroid enlargement; a recognized associated triad worth asking about
Evaluation
The diagnosis is largely clinical, built on the characteristic history of recurrent, self-limited eyelid swelling episodes beginning at a young age, followed by the residual skin and structural changes described above.
Because the acute swelling episodes can superficially resemble other causes of eyelid edema, a history spanning the full course of the disease — not just the current presentation — is often what clarifies the diagnosis, and asking specifically about recurrent episodes over years, not just the most recent one, is important.
Screening for associated Ascher syndrome features (lip swelling, thyroid enlargement) is reasonable once blepharochalasis is suspected, because recognizing the full syndrome can prompt additional relevant evaluation.
Photographic documentation of successive episodes, when available from the patient, can be genuinely helpful for confirming the recurrent, self-limited pattern and for planning the timing of any eventual reconstructive surgery once the disease has quieted.
Management
During the active phase, treatment is largely supportive, since individual swelling episodes are self-limited.
Cool compresses and reassurance are usually sufficient, and there is no proven medical therapy that reliably prevents recurrent episodes.
Some clinicians have tried oral or topical anti-inflammatory approaches during active flares, though evidence supporting any specific medical regimen is limited, and the disease tends to follow its own course regardless of intervention.
Once the disease has entered its quiescent phase and structural changes have stabilized, surgical correction — blepharoplasty for the redundant skin and fat loss, ptosis repair for levator dehiscence, and canthal tendon tightening when indicated — addresses the residual functional and cosmetic effects.
Surgery is generally deferred until the inflammatory phase has genuinely settled, because operating during an active phase risks poor healing and continued tissue changes that can compromise the surgical result.
Patients should also be counseled that, even after successful surgical repair, a late recurrence of the inflammatory process — though uncommon once the disease has truly quiesced — remains a recognized possibility, and any new episode of swelling after reconstructive surgery warrants re-evaluation rather than being assumed to be a surgical complication.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Karesh JW. Blepharochalasis. In: Smith’s Ophthalmic Plastic and Reconstructive Surgery.
- Custer PL, Tenzel RR, Kowalczyk AP. Blepharochalasis syndrome. American Journal of Ophthalmology.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 7: Orbit, Eyelids, and Lacrimal System.
Test yourself
A few questions straight from this article.
-
Which feature defines blepharochalasis?
Blepharochalasis is a rare recurrent inflammatory eyelid disorder of painless edema starting in childhood or early adulthood, eventually leaving thin, redundant, atrophic skin. -
Which mechanism is implicated in the eyelid damage of blepharochalasis?
The process is considered a localized inflammation, with evidence pointing to abnormal elastin degradation; each bout adds cumulative damage to the elastic and connective tissue framework. -
When does the active inflammatory phase of blepharochalasis typically occur?
Recurrent self-limited swelling episodes dominate the first two to three decades, after which the disease burns out into a quiescent phase leaving permanent structural change. -
What characterizes an individual swelling episode in blepharochalasis?
Episodes are painless and carry no fever or systemic features, which helps separate a flare from an infectious or broader inflammatory process needing urgent treatment. -
What causes the ptosis seen after repeated blepharochalasis episodes?
Repeated bouts of edema stretch and attenuate the levator aponeurosis, producing an aponeurotic ptosis among the residual structural changes. -
Which skin change remains once blepharochalasis burns out?
Cumulative damage leaves thin, redundant, wrinkled cigarette-paper skin, often with orbital fat loss and visible vessels showing through the atrophic tissue. -
What distinguishes blepharochalasis from dermatochalasis?
Dermatochalasis is age-related redundancy developing gradually in older adults, with no history of the discrete recurrent inflammatory bouts that define blepharochalasis. -
Which syndrome combines blepharochalasis with a double lip?
Ascher syndrome pairs blepharochalasis with a double lip and, in some patients, non-toxic thyroid enlargement, so asking about lip and thyroid swelling is worthwhile. -
How is an acute blepharochalasis flare managed?
Episodes are self-limited and no medical therapy reliably prevents recurrence, so treatment during the active phase is largely supportive. -
When should surgical correction of blepharochalasis be performed?
Operating during active disease risks poor healing and continued tissue change, so blepharoplasty, ptosis repair and canthal tightening are deferred until the disease settles.
