
Neurotrophic keratopathy is a degenerative corneal disease that develops when the trigeminal nerve’s sensory innervation of the cornea is impaired, removing not just pain sensation but also the trophic support the nerve normally provides to corneal epithelial cells.
The result is a cornea that heals poorly, breaks down easily, and — because the patient cannot feel the damage happening — frequently progresses further before anyone notices than it would if pain were still driving the patient to seek care.
Why Corneal Nerves Matter Beyond Sensation
Corneal sensory nerves release neuropeptides (including substance P and calcitonin gene-related peptide) that support normal epithelial cell proliferation, migration, and adhesion, independent of their role in transmitting pain and touch.
When this trophic input is lost, epithelial healing slows, and epithelial integrity becomes fragile even without any additional insult.
The cornea essentially loses part of its normal maintenance and repair machinery, not just its alarm system.
This distinction is precisely why treating a neurotrophic epithelial defect purely as a mechanical wound — as one might with a simple abrasion — so often fails: the underlying biological support for healing is itself deficient, not just the surface integrity, and treatment needs to address that deficiency directly rather than simply protecting the surface and waiting.
Causes
- Herpes simplex and herpes zoster keratitis — among the most common causes, from direct viral damage to corneal nerve fibers
- Prior intracranial or skull base surgery involving the trigeminal nerve, including surgery for trigeminal neuralgia or acoustic neuroma
- Diabetes mellitus, through diabetic corneal neuropathy, often underrecognized as a contributing factor
- Chemical burns and other injuries that damage corneal nerve endings directly
- Contact lens overwear
- Topical medication toxicity from chronic use of certain preserved drops
- Congenital causes, including congenital corneal anesthesia and certain rare genetic syndromes affecting trigeminal nerve development
- Leprosy, where trigeminal nerve involvement is a recognized contributor to corneal disease, discussed in more detail in the dedicated article on leprosy’s ocular findings on this site
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteClinical Staging
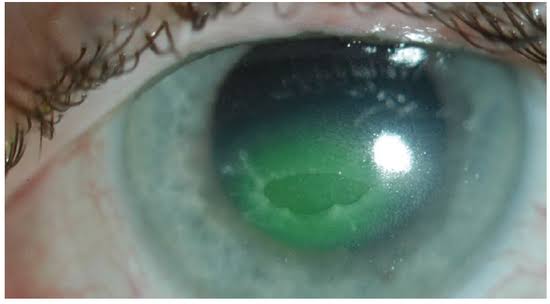
Neurotrophic keratopathy is classically staged from mild (stage 1: epithelial changes — irregularity, punctate keratopathy, reduced tear film stability — without a frank defect) through moderate (stage 2: a persistent epithelial defect, often with rolled, thickened edges that fail to progress toward healing despite standard measures) to severe (stage 3: stromal involvement with thinning, melting, and a genuine risk of descemetocele formation or perforation).
This staging directly informs the intensity of treatment, because stage 1 disease can often be managed with lubrication alone while stage 3 disease requires the same urgency as any other cause of impending corneal perforation.
Because progression between stages can happen without corresponding pain to alert the patient, regular scheduled follow-up — rather than waiting for the patient to report worsening symptoms — is the practical way disease stage is actually tracked over time.
Clinical Findings
- Reduced or absent corneal sensation on formal testing (cotton wisp or, more precisely, Cochet-Bonnet esthesiometry) — the single most important and specific finding, and one that should be actively checked whenever the diagnosis is suspected
- A persistent epithelial defect, often oval or round, with characteristically rolled, gray, thickened edges rather than the clean margins of a simple abrasion
- Notably little pain or discomfort relative to the severity of the corneal finding — a mismatch that is itself diagnostically important
- Reduced or absent blink reflex on the affected side in some cases
- Stromal thinning or melting in advanced disease
Differential Diagnosis
- Ordinary persistent epithelial defect from dry eye or exposure — corneal sensation is typically preserved, distinguishing it from a neurotrophic cause
- Infectious keratitis — usually more painful, with an infiltrate rather than isolated epithelial breakdown, though secondary infection of a neurotrophic defect is itself a real risk requiring ongoing vigilance
- Recurrent corneal erosion — episodic, typically with normal corneal sensation and a history of prior abrasion or an underlying epithelial basement membrane dystrophy
Management
Preservative-free lubrication is the foundation of treatment at every stage, both to protect the fragile ocular surface and to reduce the toxic load from preservatives that a normally functioning cornea would tolerate better.
Autologous serum or plasma eye drops, which supply growth factors and neurotrophic support the cornea would otherwise get from intact innervation, have become an important treatment for persistent defects.
Recombinant human nerve growth factor (cenegermin) is now available specifically for neurotrophic keratopathy and has meaningfully changed outcomes for many patients with moderate to severe disease, representing one of the few disease-targeted rather than purely supportive treatments available for this condition.
Bandage contact lenses, amniotic membrane transplantation, and temporary or permanent tarsorrhaphy all serve to protect the ocular surface and support healing in stage 2 and 3 disease, with the choice depending on defect severity and response to less invasive measures.
Any secondary microbial infection needs to be treated aggressively given the impaired healing capacity of the underlying cornea, since a superimposed infection on an already compromised surface can progress unusually quickly.
Eyes progressing to descemetocele or perforation are managed with the same urgency described for those findings elsewhere on this site, with the underlying neurotrophic deficit remaining a relevant consideration in surgical planning and postoperative healing expectations.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Bonini S, Rama P, Olzi D, Lambiase A. Neurotrophic keratitis. Eye.
- Sacchetti M, Lambiase A. Diagnosis and management of neurotrophic keratitis. Clinical Ophthalmology.
- Bonini S, Lambiase A, Rama P, et al. Phase II randomized, double-masked, vehicle-controlled trial of recombinant human nerve growth factor for neurotrophic keratitis. Ophthalmology.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 8: External Disease and Cornea.
Test yourself
A few questions straight from this article.
-
In neurotrophic keratopathy, loss of corneal innervation removes which support in addition to sensation?
Corneal sensory nerves do more than transmit pain: they provide trophic support to the epithelium. Losing it leaves a cornea that heals poorly and breaks down easily. -
Which neuropeptides released by corneal sensory nerves support epithelial proliferation, migration and adhesion?
These neuropeptides maintain epithelial cell proliferation, migration and adhesion independently of pain transmission, which is why epithelial integrity becomes fragile once innervation is lost. -
Which infections are among the most common causes of neurotrophic keratopathy?
Both herpetic keratitides directly damage corneal nerve fibres and rank among the most common causes of neurotrophic keratopathy. -
What defines stage 2 neurotrophic keratopathy in the classical staging system?
Stage 1 is epithelial change without a defect and stage 3 is stromal involvement; stage 2 is the persistent defect whose rolled, thickened edges fail to progress toward healing. -
Which test most precisely confirms the key deficit when neurotrophic keratopathy is suspected?
Reduced or absent corneal sensation is the single most important and specific finding, and esthesiometry measures it more precisely than a cotton wisp. -
How does the epithelial defect of neurotrophic keratopathy typically appear at its margins?
The defect is usually oval or round with characteristically rolled, gray, thickened edges, unlike the clean margins of a simple abrasion. -
Which feature separates recurrent corneal erosion from neurotrophic keratopathy?
Recurrent erosion is episodic with normal corneal sensation and a history of prior abrasion or epithelial basement membrane dystrophy. -
Which treatment for neurotrophic keratopathy targets the underlying disease rather than only supporting the surface?
Cenegermin is available specifically for neurotrophic keratopathy and is one of the few disease-targeted rather than purely supportive treatments, changing outcomes in moderate to severe disease. -
Autologous serum drops help a persistent neurotrophic defect because they supply what?
Serum or plasma drops replace growth factors and neurotrophic support the cornea would otherwise receive from intact innervation. -
Why is neurotrophic keratopathy tracked with scheduled review rather than waiting for patient-reported worsening?
Because the damaged cornea cannot signal pain, disease can advance silently, so regular scheduled follow-up is the practical way stage is actually tracked.
