Sclerosing keratitis is a peripheral corneal opacification that develops next to an area of active scleritis.
The affected stroma turns gray-white, so the limbus seems to creep onto the cornea, and clinicians also call the condition sclerokeratitis. Because it often accompanies severe or vasculitic scleritis, it calls for a systemic workup.
What Sclerosing Keratitis Is
The term describes stromal inflammation and scarring adjacent to inflamed sclera, and over time the clear peripheral cornea takes on the opaque look of sclera. Usually the epithelium stays intact and stromal thickness is preserved, so the lesion reflects scarring, while active melting is absent.
Why the Cornea Opacifies
The peripheral cornea shares blood supply and immune cells with the limbus and sclera. As a result, scleral inflammation spreads into the neighboring stroma. Inflammatory mediators and new vessels then disorganize the collagen lamellae, but the exact mechanism is not fully defined and likely varies with the underlying disease.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteSlit Lamp Signs of Sclerosing Keratitis
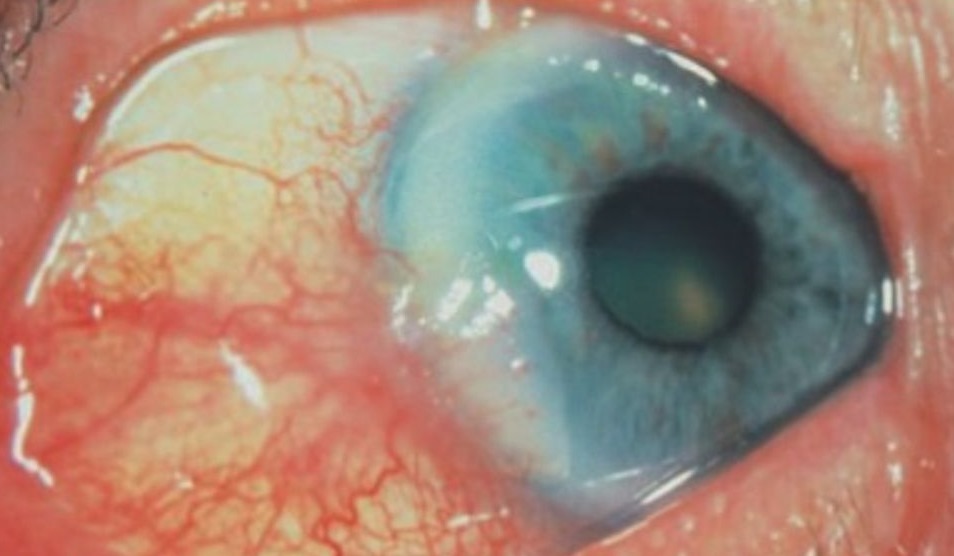
- Gray-white stromal opacity contiguous with inflamed sclera
- Tongue or crescent shape advancing toward the center
- Intact epithelium with little or no fluorescein staining
- Normal or near-normal stromal thickness
- Vessels entering the opacity, with lipid at the edge in chronic cases
What the Patient Reports
Most patients present with the pain of scleritis, which feels deep and boring, and the ache often wakes them at night and radiates to the brow or jaw. In addition, redness and globe tenderness are common, while vision stays normal unless the opacity reaches the visual axis or induces astigmatism.
The Scleritis Behind It
Sclerosing keratitis accompanies anterior scleritis, often of the nodular or necrotizing type, and some cases also follow diffuse disease that smolders for months. Therefore, classify the scleritis first, because the pattern guides the workup (see scleritis classification).
Systemic Associations of Sclerosing Keratitis
Rheumatoid arthritis is the classic association in older patients, while granulomatosis with polyangiitis and relapsing polychondritis also appear in reported series. In addition, herpes zoster ophthalmicus can produce scleritis with adjacent corneal scarring, and syphilis and tuberculosis are less common, yet treatable, causes.
Sclerosing Keratitis Versus PUK
Peripheral ulcerative keratitis shows an epithelial defect and progressive stromal thinning, whereas sclerosing keratitis keeps an intact surface and stable thickness. PUK can perforate quickly while the sclerosing form scars slowly, but both share the same systemic triggers and can coexist in one eye (see peripheral ulcerative keratitis).
Distinguishing Interstitial Keratitis
Interstitial keratitis involves the deep stroma, often centrally or diffusely, with ghost vessels, and it usually lacks a contiguous zone of active scleritis. For example, syphilitic disease leaves bilateral deep scars long after the acute phase (see interstitial keratitis), so location and continuity with sclera help separate the two.
Other Look-Alikes
- Arcus senilis, which keeps a clear lucid interval at the limbus
- Terrien marginal degeneration, with thinning and lipid but little pain
- A healed infectious scar in the peripheral cornea
Workup for Sclerosing Keratitis
First, take a full systemic history, including joint, sinus, ear, lung and kidney symptoms, and then order a blood count, ESR, CRP, rheumatoid factor, anti-CCP and ANCA. Also request treponemal serology, urinalysis and a chest radiograph, and finally ask about prior shingles in the same dermatome.
Treating Sclerosing Keratitis
Treatment targets the scleritis, because the corneal change follows it, and oral NSAIDs may control mild nodular disease. However, necrotizing or vasculitic scleritis needs systemic corticosteroids and usually a steroid-sparing immunosuppressive agent, so co-manage with a rheumatologist, since these drugs carry significant risks.
Role of Topical Steroids
Topical corticosteroids can calm adjacent corneal inflammation, but they cannot control scleritis on their own. They also raise intraocular pressure and may worsen thinning if melting begins, so use them only as adjuncts with close monitoring.
What Treatment Cannot Do
Established opacity rarely clears completely, even after the scleritis becomes quiet. Some peripheral lucency may return as vessels regress, and central encroachment may later require keratoplasty.
Counseling the Patient
Explain that the white patch reflects inflammation in the wall of the eye, and mention that the same process may affect joints, kidneys or lungs. Ask patients to report new pain, redness or blurred vision quickly, and because adherence drives outcome, discuss drug side effects openly.
Follow-Up in Sclerosing Keratitis
Review active cases every one to two weeks until the scleritis settles, and at each visit stain the cornea and check thickness at the leading edge. Anterior segment OCT helps document early thinning, and any new epithelial defect suggests conversion toward ulceration, so intensify systemic therapy promptly.
Pitfalls to Avoid
- Do not treat the opacity as an isolated scar
- Never skip ANCA testing in painful necrotizing scleritis
- Do not rely on topical steroids for scleritis control
- Remember herpes zoster as a possible cause


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Watson PG, Hayreh SS. Scleritis and episcleritis. Br J Ophthalmol. 1976;60:163-191.
- Sainz de la Maza M, Foster CS, Jabbur NS. Scleritis associated with systemic vasculitic diseases. Ophthalmology. 1995;102:687-692.
- Okhravi N, Odufuwa B, McCluskey P, Lightman S. Scleritis. Surv Ophthalmol. 2005;50:351-363.
- Galor A, Thorne JE. Scleritis and peripheral ulcerative keratitis. Rheum Dis Clin North Am. 2007;33:835-854.
Test yourself
A few questions straight from this article.
-
How is sclerosing keratitis defined?
Sclerosing keratitis is a gray-white peripheral corneal opacification adjacent to active scleritis, so the limbus seems to creep onto the cornea. -
Why does scleral inflammation spread into the adjacent cornea in sclerosing keratitis?
The peripheral cornea shares blood supply and immune cells with the limbus and sclera, so scleral inflammation spreads into neighboring stroma, though the exact mechanism is not fully defined. -
What is the typical shape of the opacity in sclerosing keratitis?
The gray-white opacity is contiguous with inflamed sclera and forms a tongue or crescent advancing centrally, with vessels and edge lipid in chronic cases. -
Which finding favors peripheral ulcerative keratitis over sclerosing keratitis?
PUK shows an epithelial defect and progressive thinning and can perforate quickly, whereas sclerosing keratitis keeps an intact surface and stable thickness. -
Which feature points to interstitial keratitis rather than sclerosing keratitis?
Interstitial keratitis involves deep stroma, often centrally or diffusely, with ghost vessels, and usually lacks a contiguous zone of active scleritis. -
Which systemic disease is the classic association of sclerosing keratitis in older patients?
Rheumatoid arthritis is the classic association in older patients, with granulomatosis with polyangiitis, relapsing polychondritis and herpes zoster also reported. -
How is sclerosing keratitis with necrotizing or vasculitic scleritis treated?
Treatment targets the scleritis; necrotizing or vasculitic disease needs systemic steroids and usually a steroid-sparing immunosuppressive, co-managed with a rheumatologist. -
What role do topical corticosteroids have in sclerosing keratitis?
Topical steroids can calm adjacent corneal inflammation but cannot control scleritis alone, and they raise pressure and may worsen thinning if melting begins. -
What happens to established opacity in sclerosing keratitis once the scleritis is quiet?
Established opacity rarely clears completely; some peripheral lucency may return as vessels regress, and central encroachment may later need keratoplasty. -
During follow-up of sclerosing keratitis, what does a new epithelial defect suggest?
Any new epithelial defect suggests conversion toward ulceration, so systemic therapy is intensified promptly; anterior segment OCT helps document early thinning.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.