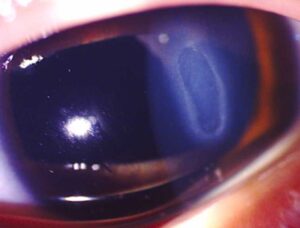
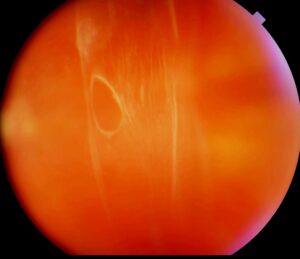
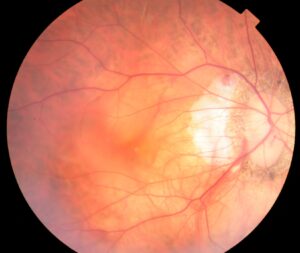
Scleral buckle recovery commonly takes about three months, although comfort usually returns much sooner.
Pain, swelling, double vision and a myopic shift can all occur during this period, but clinicians must separate these expected events from redetachment, infection and pressure problems.
What Shapes Scleral Buckle Recovery
The surgeon opens the conjunctiva, isolates the rectus muscles and secures an explant to the sclera (see buckle technique). As a result, this external surgery often causes considerable orbital soreness, so each patient needs a timeline that fits the actual operation.
The First Week
Most patients return the next day for examination of vision, pressure, chamber depth and retinal position. Nausea may follow muscle traction, so an antiemetic can help.
Pain usually eases by the end of the week, while swelling and redness may persist. Vision often remains blurred because of edema, ointment and refractive change, and then the clinician confirms that the break sits on the buckle.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this sitePain Control in Scleral Buckle Recovery
Patients typically describe a deep ache that worsens with eye movement. Oral analgesics and cold compresses usually control it, and the ache then fades over one to two weeks. However, escalating pain deserves same-day examination, as severe pain with halos and nausea suggests raised pressure, while pain with falling vision raises concern for infection.
Swelling and Drops
Lid edema, chemosis and subconjunctival hemorrhage look alarming but settle over several weeks, while regimens typically combine a topical antibiotic and a corticosteroid, followed by a taper. Because steroid responders can develop ocular hypertension, pressure checks should continue, whereas thick purulent discharge needs prompt assessment.
Gas and Positioning in Scleral Buckle Recovery
While a buckle alone usually requires little positioning, an added gas bubble requires the head posture the surgeon prescribes. Gas also rules out air travel and nitrous oxide anesthesia until it absorbs.
Weeks Two to Four
Most patients resume light desk work during this period, but many surgeons restrict heavy lifting and contact sports for several weeks. Driving depends on legal vision standards and the absence of diplopia.
Diplopia in Scleral Buckle Recovery
Early double vision often reflects muscle edema and altered mechanics from the explant, and many cases improve over weeks to months as inflammation resolves. Temporary occlusion or Fresnel prisms can then provide relief, but persistent misalignment needs a structured workup (see diplopia assessment).
Refractive Shift After Surgery
An encircling element can lengthen the eye and therefore often induces myopia. Refraction can drift while edema settles, so many surgeons defer new glasses for two to three months. A large unilateral shift may cause anisometropia, and a contact lens can then help.
Visual Outcome in Scleral Buckle Recovery
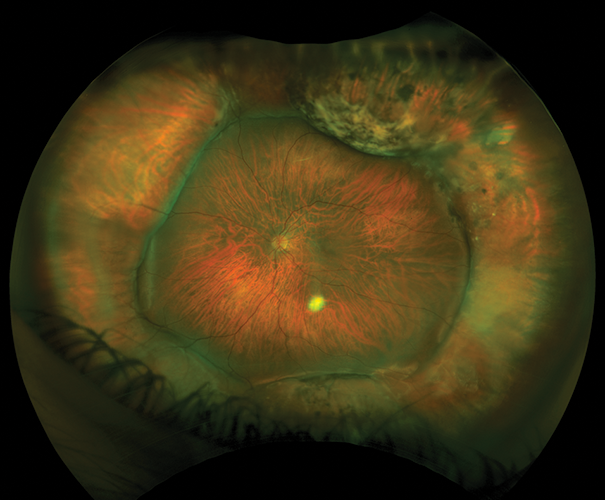
Macula-on patients often regain vision faster once refraction stabilizes, whereas macula-off patients may improve slowly over many months, and metamorphopsia and reduced contrast can also persist. Therefore, OCT helps explain limited vision by showing outer retinal disruption or persistent fluid. Surgery can reattach the retina, but it cannot guarantee full macular function.
Persistent Subretinal Fluid
Shallow fluid may persist on OCT for weeks after anatomically successful surgery. If the break remains closed and the fluid regresses, observation is usually reasonable, but enlarging fluid should prompt a search for an open or missed break.
Late Follow-Up in Scleral Buckle Recovery
Follow-up intervals usually lengthen once the retina stays attached, but proliferative vitreoretinopathy typically declares itself early, so peripheral examination remains essential. Late buckle problems, including infection and extrusion, can also appear (see buckle complications).
Warning Signs During Scleral Buckle Recovery
Patients should seek urgent review for any of the following:
- A new shadow or curtain in the visual field
- New flashes or a shower of floaters
- A sudden drop in vision
- Worsening pain, especially with nausea or halos
- Increasing redness, swelling or purulent discharge
What the Examiner Should Exclude
Shallow anterior chamber with high pressure suggests ciliochoroidal effusion with secondary angle closure. Anterior segment ischemia is uncommon, but pain and corneal edema should raise suspicion after encircling. Finally, a pale disc may indicate excessive buckle effect or high pressure.
Counseling Patients in Scleral Buckle Recovery
First, explain that the eye may look worse than it feels during the first week, and next, warn patients that glasses may not work well until refraction stabilizes. Written warning signs also help patients act quickly, while the fellow eye may share risk factors, so advise a dilated examination.
Pitfalls to Avoid
- Do not attribute rising pain to routine soreness without measuring pressure
- Avoid prescribing final glasses before refraction stabilizes
- Do not label new diplopia as permanent early
- Never overlook gas status before air travel


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Smiddy WE, Loupe D, Michels RG, et al. Refractive changes after scleral buckling surgery. Arch Ophthalmol. 1989;107:1469-1471.
- Farr AK, Guyton DL. Strabismus after retinal detachment surgery. Curr Opin Ophthalmol. 2000;11:207-210.
- Heimann H, Bartz-Schmidt KU, Bornfeld N, et al. Scleral buckling versus primary vitrectomy in rhegmatogenous retinal detachment: a prospective randomized multicenter clinical study. Ophthalmology. 2007;114:2142-2154.
- Schwartz SG, Flynn HW Jr, Mieler WF. Update on retinal detachment surgery. Curr Opin Ophthalmol. 2013;24:255-261.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 12: Retina and Vitreous. San Francisco: AAO.
Test yourself
A few questions straight from this article.
-
How long does full recovery after scleral buckle surgery commonly take?
Scleral buckle recovery commonly takes about three months, although comfort usually returns much sooner. -
After scleral buckle surgery, worsening pain with halos and nausea most suggests which problem?
Severe pain with halos and nausea suggests raised pressure, whereas pain with falling vision raises concern for infection; escalating pain needs same-day examination. -
Why should pressure checks continue while topical drops are tapered after scleral buckle surgery?
The usual regimen combines a topical antibiotic and corticosteroid with a taper, and steroid responders may develop ocular hypertension. -
When a gas bubble is added to a scleral buckle, which restriction applies until the gas absorbs?
A buckle alone needs little positioning, but gas requires prescribed head posture and rules out air travel and nitrous oxide anaesthesia until absorbed. -
Which option can relieve early double vision after scleral buckle surgery while it settles?
Early diplopia often reflects muscle oedema and altered mechanics and improves over weeks to months; occlusion or Fresnel prisms give relief meanwhile. -
Why does an encircling scleral buckle often induce myopia?
An encircling element can lengthen the eye, producing a myopic shift that may cause anisometropia, where a contact lens can help. -
When do many surgeons prescribe new glasses after scleral buckle surgery?
Refraction drifts while oedema settles, so many surgeons defer new glasses for two to three months; prescribing final glasses early is a listed pitfall. -
Which patients usually regain vision faster after scleral buckle repair of retinal detachment?
Macula-on eyes often recover faster, while macula-off eyes improve slowly over months and may keep metamorphopsia and reduced contrast. -
After scleral buckle surgery, enlarging subretinal fluid on OCT should prompt what?
Shallow regressing fluid with a closed break can be observed, but enlarging fluid points to an open or missed break. -
After scleral buckling, a shallow anterior chamber with high pressure suggests which complication?
The examiner should exclude ciliochoroidal effusion with secondary angle closure when the chamber is shallow and pressure is high.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.