Subretinal injection delivers a drug, a gene vector, or cells into the space between the photoreceptors and the retinal pigment epithelium.
Surgeons use it for gene therapy, cell therapy, and tissue plasminogen activator for submacular hemorrhage. The technique is delicate, since the retina is thin and the target space is potential.
Why Use Subretinal Injection
Many gene therapy vectors transduce RPE and photoreceptor cells efficiently only when injected below the retina. An intravitreal route may not reach these cells, because the internal limiting membrane acts as a barrier. Subretinal delivery therefore places the agent next to its target cells (see gene therapy for inherited retinal disease).
Subretinal Injection Equipment
Surgeons use a 23, 25, or 27-gauge vitrectomy system and a fine subretinal cannula, often 38 to 41 gauge. A syringe with controlled pressure, such as a foot-pedal injector, gives steady delivery. Micro-forceps and a heads-up display or optical coherence tomography in the operating room may help in some centers.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteSurgical Technique
First, the surgeon performs a core vitrectomy and induces a posterior vitreous detachment. The next step is to choose the entry point, usually away from the macula and outside the vascular arcades.
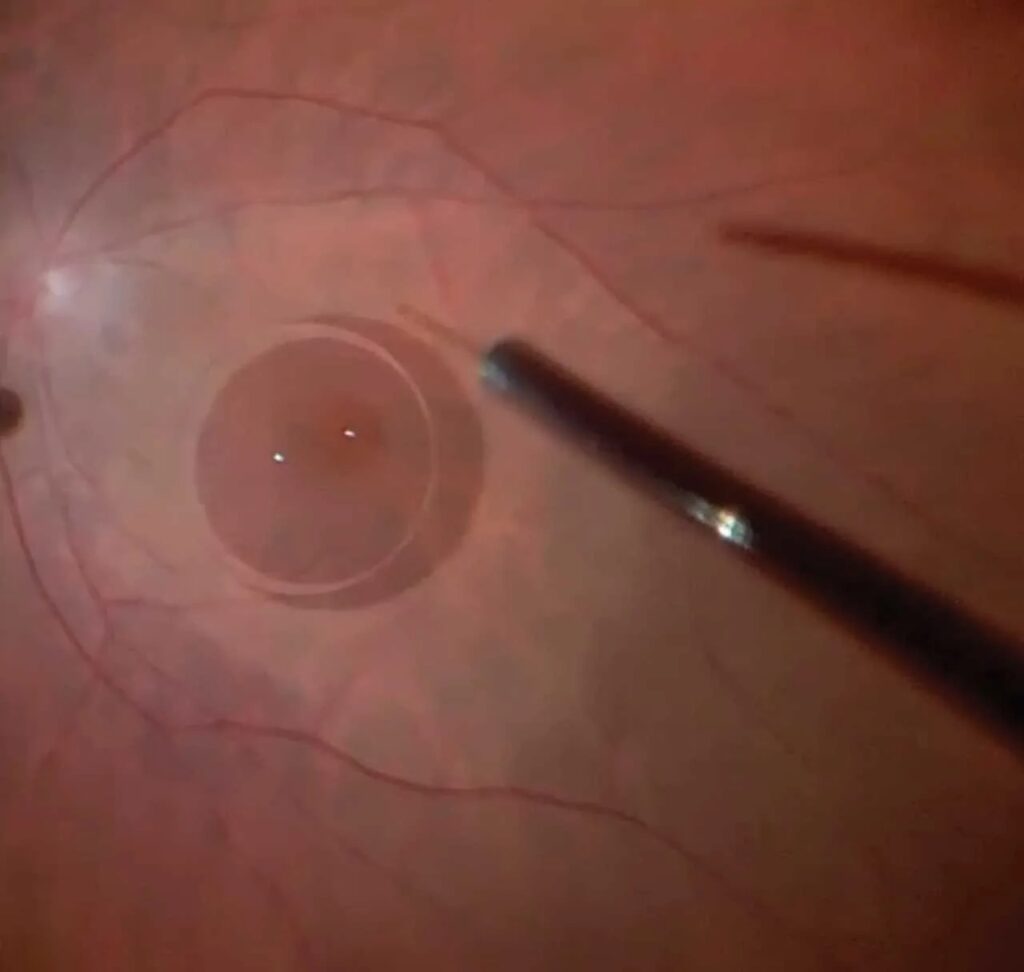
After that, a small injection of balanced salt solution creates a bleb, and the agent follows into that bleb. Finally, the bleb expands under the macula, and the surgeon removes the cannula without reflux and leaves the eye filled with fluid or exchanges it to air, depending on the protocol.
Subretinal Injection in Gene Therapy
Voretigene neparvovec uses this technique, and trials of gene therapy for Leber congenital amaurosis led the field (see Leber congenital amaurosis). The technique requires a bleb that covers the target area, and it avoids touching the fovea more than necessary. Newer approaches under study include suprachoroidal and intravitreal delivery to avoid surgery.
Complications of Subretinal Injection
- Macular hole, especially when the bleb detaches the fovea
- Retinal tears at the entry site
- Reflux of vector into the vitreous, which may reduce the effect
- Subretinal hemorrhage and later chorioretinal atrophy
Careful bleb formation and a small, controlled injection lower these risks (see iatrogenic macular defects during vitreoretinal surgery).
Tips for Success
Use a pre-bleb when the retina is difficult to detach, and inject slowly while you watch the bleb under good illumination.
Avoid perfusion pressure peaks that push fluid into the subretinal space, and document the volume and the bleb position for the study record.
An Example Case
A 12-year-old child with biallelic RPE65 disease receives gene therapy. After vitrectomy, the surgeon creates a bleb with a 41-gauge cannula, and the bleb covers the macula.
The gene vector enters the bleb, and the surgeon exchanges the fluid for air. The child recovers without a macular hole, and light sensitivity improves in the following months.
Key Points
- Create a pre-bleb before the vector
- Place the retinotomy outside the arcades
- Watch for macular hole and reflux
Questions Patients Ask
Patients ask whether the surgery is safe, and the answer depends on the agent and their condition. They also ask how long recovery takes, and many return to routine activity within weeks. Because gene therapy needs follow-up, explain the visit schedule.
Pitfalls to Avoid
- Injecting without a pre-bleb in an eye with tight retina
- Placing the retinotomy too close to the fovea
- Allowing reflux into the vitreous during withdrawal
- Overlooking early macular hole after surgery
Looking Ahead
Suprachoroidal and intravitreal gene delivery may reduce the need for surgery, and intraoperative OCT may improve bleb placement. However, subretinal delivery remains the reference method for many vectors.
Practical Points
Rehearse the injection steps in a wet lab before the first case. Then confirm the cannula and syringe settings with the sterile team, and plan the postoperative drops and steroids in advance.
Choosing the Retinotomy Site
Place the entry in the superotemporal retina, outside the arcade, in an area of healthy tissue. Because the bleb spreads under gravity and pressure, a site near the target area helps.
Avoid areas with vessels, since bleeding may cloud the view, and then confirm that the cannula tip enters the subretinal space smoothly. Keep the infusion pressure low during injection, so that the bleb does not extend too quickly, and record the bleb size with a photo or OCT when available.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Maguire AM, Simonelli F, Pierce EA, et al. Safety and efficacy of gene transfer for Leber’s congenital amaurosis. N Engl J Med. 2008;358:2240-2248.
- Davis JL, Gregori NZ, MacLaren RE, Lam BL. Surgical technique for subretinal gene therapy in humans with inherited retinal degeneration. Retina. 2019;39(Suppl 1):S2-S8.
- Russell S, Bennett J, Wellman JA, et al. Efficacy and safety of voretigene neparvovec (AAV2-hRPE65v2) in patients with RPE65-mediated inherited retinal dystrophy: a randomised, controlled, open-label, phase 3 trial. Lancet. 2017;390:849-860.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 12: Retina and Vitreous. AAO; current edition.
Test yourself
A few questions straight from this article.
-
Into which space does subretinal injection deliver a drug, gene vector or cells?
Subretinal injection places the agent in the potential space between the photoreceptors and the RPE, which is why the technique is so delicate. -
Why may an intravitreal route fail to reach the target cells of many retinal gene therapy vectors?
Many vectors transduce RPE and photoreceptors efficiently only from below the retina, because the internal limiting membrane blocks access from the vitreous side. -
What cannula size is typically used for subretinal injection during vitrectomy?
A fine subretinal cannula, often 38 to 41 gauge, is passed through a 23, 25 or 27-gauge vitrectomy system. -
Which steps come first in subretinal injection, before the entry point is chosen?
The surgeon first performs a core vitrectomy and induces a posterior vitreous detachment, then chooses the entry point. -
In subretinal gene therapy surgery, what is usually injected first to create the bleb before the agent?
A small injection of balanced salt solution raises a pre-bleb, and the agent then follows into it; a pre-bleb is especially useful when the retina is hard to detach. -
Where is the retinotomy for subretinal injection usually placed?
The entry is placed outside the arcades in healthy tissue, often superotemporally, and away from vessels; a retinotomy too close to the fovea is a listed pitfall. -
Which complication of subretinal injection is most likely when the bleb detaches the fovea?
Macular hole is listed as a complication especially when the bleb detaches the fovea, so early postoperative holes must not be overlooked. -
What is the main concern when a gene vector refluxes into the vitreous during subretinal injection?
Reflux of vector into the vitreous may reduce the effect, so the cannula is withdrawn carefully to avoid reflux. -
By which route is the gene therapy voretigene neparvovec delivered?
Voretigene neparvovec uses subretinal injection; suprachoroidal and intravitreal delivery are newer approaches still under study. -
How should infusion pressure be managed while the subretinal bleb is being raised?
Low infusion pressure stops the bleb from extending too quickly, and pressure peaks that push fluid into the subretinal space should be avoided.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.