Papilledema recovery begins when intracranial pressure falls, although the disc usually lags behind the pressure.
Swelling commonly settles over weeks to months, so follow optic nerve function as closely as disc appearance.
What Drives Papilledema Recovery
Raised pressure in the optic nerve sheath impairs axoplasmic flow near the lamina cribrosa, so axons swell and the disc margins blur (see papilledema basics). Once pressure falls, transport recovers and fluid clears, but axons lost during the high-pressure phase do not return.
Typical Papilledema Recovery Timeline
No fixed timetable fits every patient, but after effective pressure control, many discs improve within weeks and settle substantially within a few months. However, severe or long-standing swelling often takes longer, and one eye may recover before the other.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteEarly Changes at the Disc
Transient visual obscurations and headache may improve soon after pressure falls, although the disc can look unchanged at this early visit. Then, hyperemia fades, hemorrhages and cotton-wool spots clear, and disc elevation falls, while hard exudates may clear more slowly because lipid takes time to resorb.
How Cause Affects Papilledema Recovery
Speed depends on how quickly the cause is controlled. For example, tumor removal or shunting lowers pressure directly, while idiopathic intracranial hypertension often improves gradually with weight loss and medication. Cerebral venous sinus thrombosis needs urgent treatment, because persistent outflow obstruction sustains swelling.
What the IIHTT Showed
The Idiopathic Intracranial Hypertension Treatment Trial studied patients with mild visual loss. At six months, acetazolamide plus diet improved perimetric mean deviation more than diet alone, and papilledema grade also improved more in the acetazolamide group. However, the benefit was modest, and results apply mainly to similar patients, while acetazolamide can also cause paresthesia, altered taste and fatigue.
Grading and OCT During Papilledema Recovery
The modified Frisén scale gives a shared language for documenting change, but grading varies between observers, so serial disc photographs help. Peripapillary RNFL thickness also measures swelling, however, a falling value can mean resolving edema or axonal loss.
For that reason, pair it with macular ganglion cell analysis and perimetry. Anterior bowing of the peripapillary RPE may also lessen after pressure falls, and segmentation errors are common in marked swelling, so review the scans directly.
Visual Field Monitoring
Perimetry tracks the function that treatment aims to protect, and blind spot enlargement often improves as swelling settles. In contrast, established nasal or arcuate defects may persist, and therefore repeat fields at a consistent setting and compare trends.
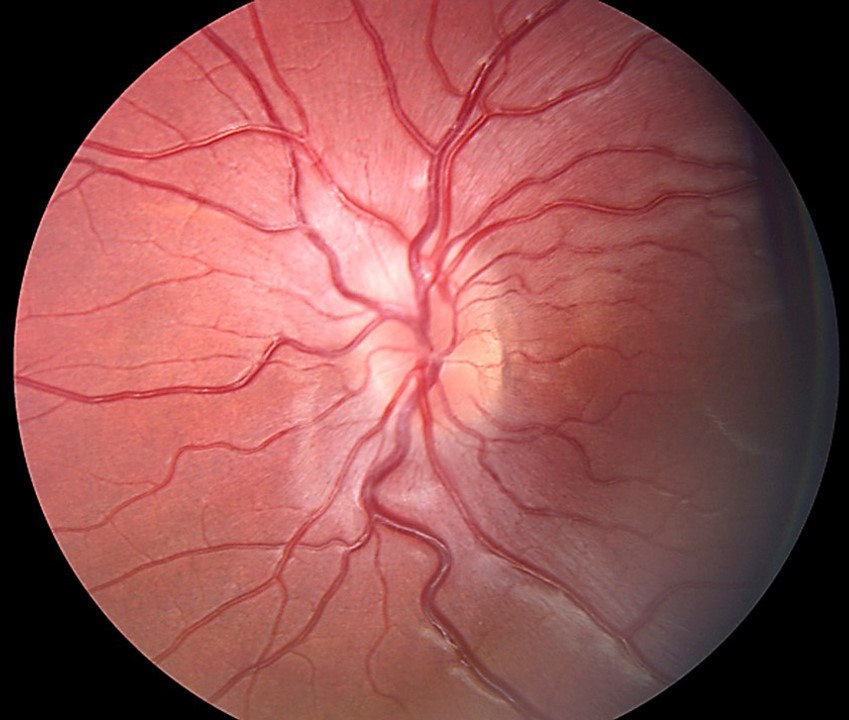
Residual Findings After Papilledema Recovery
A recovered disc rarely looks entirely normal after prolonged swelling, and examiners may find these changes:
- Mild margin blur from gliosis
- Disc pallor
- Peripapillary pigment changes
- Persistent retinochoroidal folds (see Paton lines)
- Optociliary shunt vessels
- Nerve fiber layer dropout
Resolution or Atrophy?
A flatter disc can be a warning sign, because atrophic papilledema shows pallor, attenuated vessels and declining vision. Meanwhile, swelling may decrease because too few axons remain to swell, so pressure may still be high.
When Improvement Stalls
First, check adherence, weight trajectory and drugs linked to raised pressure, next consider shunt failure, venous sinus disease or an unrecognized mass, and also reconsider other causes of disc edema (see pseudopapilledema versus papilledema). Worsening fields need urgent escalation, including CSF diversion or optic nerve sheath fenestration.
Recurrence After Apparent Recovery
Swelling can return after weight regain or medication withdrawal, and similarly, a blocked shunt can produce renewed symptoms. However, a gliotic or atrophic disc may swell less, even when pressure rises again, and therefore a quiet disc does not exclude recurrent intracranial hypertension in a symptomatic patient.
Follow-Up During Papilledema Recovery
Visit intervals should reflect visual risk and treatment phase, and each visit should include:
- Visual acuity and color vision
- Pupil assessment
- Dilated disc examination and photographs
- OCT of the RNFL and ganglion cell layer
- Threshold visual fields
Also, reduce medication gradually and recheck the disc and fields after each step down.
Counseling on Papilledema Recovery
Tell patients that symptoms and disc appearance may improve at different speeds, and also explain that lost field may not return. Ask them to report new obscurations, double vision, worsening headache or dimming promptly, and finally stress that regaining weight or stopping treatment can bring swelling back.
Pitfalls to Avoid
- Do not equate a flatter disc with better nerve function
- Avoid judging response from one OCT value
- Never assume bilateral disc swelling is papilledema (see disc swelling causes)


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Wall M, McDermott MP, Kieburtz KD, et al. Effect of acetazolamide on visual function in patients with idiopathic intracranial hypertension and mild visual loss: the idiopathic intracranial hypertension treatment trial. JAMA. 2014;311:1641-1651.
- Frisén L. Swelling of the optic nerve head: a staging scheme. J Neurol Neurosurg Psychiatry. 1982;45:13-18.
- Friedman DI, Liu GT, Digre KB. Revised diagnostic criteria for the pseudotumor cerebri syndrome in adults and children. Neurology. 2013;81:1159-1165.
- Mollan SP, Davies B, Silver NC, et al. Idiopathic intracranial hypertension: consensus guidelines on management. J Neurol Neurosurg Psychiatry. 2018;89:1088-1100.
- Sibony P, Kupersmith MJ, Honkanen R, et al. Effects of lowering cerebrospinal fluid pressure on the shape of the peripapillary retina in intracranial hypertension. Invest Ophthalmol Vis Sci. 2014;55:8223-8231.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 5: Neuro-Ophthalmology. San Francisco: AAO.
Test yourself
A few questions straight from this article.
-
In papilledema, what happens to axons lost during the high-pressure phase once intracranial pressure falls?
Raised sheath pressure blocks axoplasmic flow near the lamina cribrosa; once pressure falls, transport recovers and fluid clears, but axons already lost do not come back. -
After effective control of intracranial pressure, what is the typical recovery course of papilledema?
No fixed timetable fits all, but many discs improve within weeks and settle substantially within a few months; severe or long-standing swelling takes longer and one eye may lag. -
During papilledema recovery, which disc finding typically clears most slowly?
Hyperemia fades and hemorrhages and cotton-wool spots clear as elevation falls, while hard exudates resolve more slowly because lipid takes time to resorb. -
In the Idiopathic Intracranial Hypertension Treatment Trial, what did acetazolamide plus diet achieve at six months compared with diet alone?
In patients with mild visual loss, acetazolamide plus diet improved mean deviation and papilledema grade more than diet alone, though the benefit was modest. -
During papilledema recovery, why can a falling peripapillary RNFL thickness on OCT be misleading on its own?
A falling RNFL value can mean edema is resolving or that axons are being lost, so it should be paired with macular ganglion cell analysis and perimetry. -
Which visual field change often improves as papilledema settles?
Blind spot enlargement often improves as swelling settles, whereas established nasal or arcuate defects may persist, so fields should be repeated at a consistent setting. -
Why can a flatter optic disc be a warning sign rather than reassurance in treated papilledema?
Atrophic papilledema shows pallor, attenuated vessels and declining vision; swelling falls because few axons remain to swell, so pressure may still be high. -
Which vascular finding may persist at the optic disc after prolonged papilledema has resolved?
A recovered disc rarely looks fully normal after prolonged swelling; residual findings include gliotic margin blur, pallor, pigment change, retinochoroidal folds, optociliary shunts and nerve fiber layer dropout. -
When visual fields worsen despite treatment for papilledema, which escalation does management call for?
Stalled improvement prompts checks of adherence, weight, drugs, shunt and venous sinuses, while worsening fields need urgent escalation such as CSF diversion or optic nerve sheath fenestration. -
How should medication be withdrawn once papilledema has recovered?
Medication should be tapered gradually with the disc and fields rechecked after each step down, because stopping treatment or regaining weight can bring the swelling back.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.