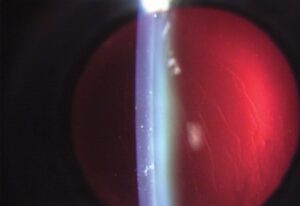
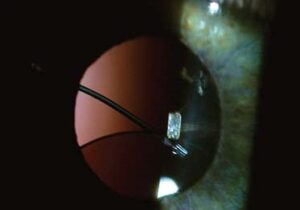
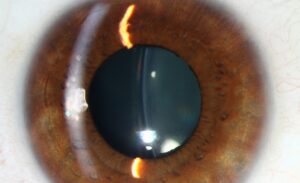
Atopic cataract is a lens opacity that develops in young adults and adolescents with severe atopic dermatitis, and it is characterized by an anterior subcapsular plaque that may appear shield-like.
It can progress rapidly, and it is a reminder that the eye is part of a systemic atopic disease.
The patient is usually in the second or third decade of life, which is much younger than the usual age for cataract.
What Is Atopic Cataract?
Cataract in atopic dermatitis affects a minority of patients, and the frequency is higher in those with severe disease and with keratoconjunctivitis.
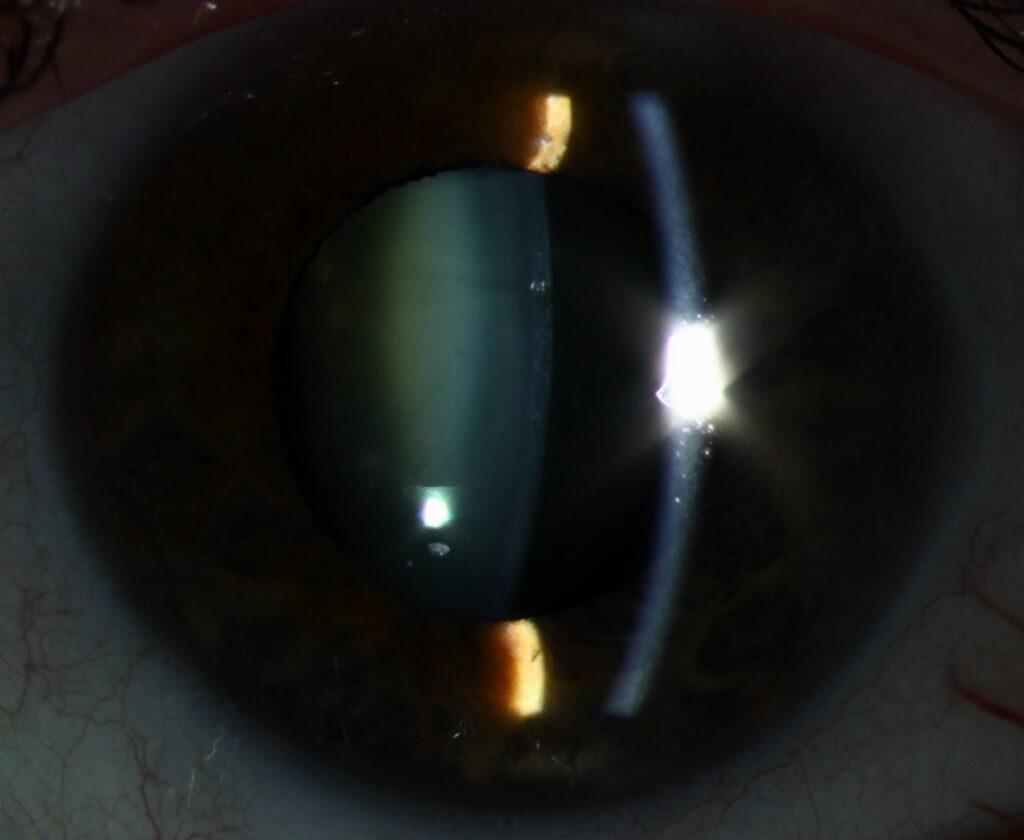
The lens opacity can be anterior subcapsular, posterior subcapsular, or both, and anterior plaques with a stellate or shield-like shape are the distinctive form.
The exact mechanism is not settled, and the proposed contributors include chronic inflammation, eye rubbing and trauma, and the effect of long-term corticosteroids.
Some patients develop lens changes without any steroid exposure, which supports a role for the disease itself.
The condition overlaps with atopic keratoconjunctivitis and keratoconus, and many patients have more than one of these (see atopic keratoconjunctivitis).
Clinical Features
Patients complain of blurred vision, glare, and difficulty with bright light, and they may notice that vision fluctuates with the pupil size.
The slit lamp shows a gray-white plaque beneath the anterior capsule, often central and sometimes with a pearly, stellate appearance.
Posterior subcapsular opacities may coexist, and they look like a granular or vacuolated plaque in retroillumination.
The lens may also show cortical changes in advanced cases.
Look for eczema of the eyelids and face, thickened lids, periorbital hyperpigmentation, and signs of keratoconus.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteEvaluation
Take a history of the skin disease, its severity, the use of topical and oral steroids, and the pattern of eye rubbing.
Examine the lids, conjunctiva, and cornea for atopic keratoconjunctivitis, and perform corneal topography to look for keratoconus.
Measure the intraocular pressure, because steroid use is common in this group and can cause glaucoma (see steroid-induced glaucoma).
A dilated fundus examination should be performed, as atopic patients are at risk of retinal detachment, particularly after trauma and eye rubbing.
Differential Diagnosis
- Steroid-induced cataract: posterior subcapsular, related to dose and duration (see posterior subcapsular cataract)
- Traumatic cataract: history of a blow or a penetrating injury, often with a rosette pattern
- Uveitic cataract: posterior synechiae and signs of inflammation
- Congenital or developmental cataract: noted in childhood and stable
Management
Early control of the skin disease and the ocular surface inflammation is the first step, using steroid-sparing agents such as topical calcineurin inhibitors when possible.
Patients should be advised to avoid eye rubbing, which also damages the cornea and the retina.
Cataract surgery is indicated when vision or function is affected, and the timing is guided by the patient’s needs.
The surgeon should be aware of the associated problems, which include zonular weakness, anterior capsular contraction, and a higher rate of retinal detachment.
Postoperative inflammation is managed carefully, and follow-up includes the retinal periphery.
Atopic Disease and the Rest of the Eye
Patients with atopic dermatitis have a higher rate of several ocular problems beyond cataract.
Keratoconus is associated with chronic eye rubbing and with atopy, and it can progress rapidly in young patients.
Herpes simplex keratitis may be more frequent and more severe in atopic patients, and eczema herpeticum around the eye needs urgent treatment.
Retinal detachment, sometimes with giant tears or a history of blunt rubbing, occurs more often in this group, and the symptoms should be explained.
Because several of these conditions are interrelated, a complete examination of the cornea, lens, and retina is worthwhile at each visit.
Steroid Exposure
Many patients with atopic dermatitis use topical corticosteroids on the face and eyelids, and the amount absorbed can be significant.
Periocular use of potent steroids should be minimized, and the steroid-sparing alternatives discussed with the dermatologist.
A record of the type, potency, and duration of treatment helps to estimate the contribution of steroids to the lens changes.
Surgical Pearls
The lens capsule in atopic eyes may be fragile, and the zonules may be weakened by chronic rubbing, so capsular tension devices should be available.
A well-sized capsulorhexis helps to avoid capsular contraction, which has been described with this condition.
Postoperative review should include a careful look at the periphery for tears, and patients should be advised against rubbing the eye.
Parents of children with atopic dermatitis should also know that persistent eye rubbing, light sensitivity, or reduced vision warrants an eye examination in addition to treatment of the skin.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Bair B, Dodd J, Heidelberg K, Krach K. Cataracts in atopic dermatitis: a case presentation and review of the literature. Arch Dermatol. 2011;147:585-588.
- Nagaki Y, Hayasaka S, Kadoi C. Cataract progression in patients with atopic dermatitis. J Cataract Refract Surg. 1999;25:96-99.
- Salmon JF. Kanski’s Clinical Ophthalmology: A Systematic Approach. 9th ed. Elsevier; 2020.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 11: Lens and Cataract. AAO; current edition.
Test yourself
A few questions straight from this article.
-
In which decades of life does atopic cataract typically appear?
Atopic cataract develops in adolescents and young adults, usually in the second or third decade, which is much younger than the usual age for cataract. -
What is the distinctive lens finding of atopic cataract?
Anterior subcapsular plaques with a stellate or shield-like shape are the distinctive form, seen as a gray-white plaque beneath the anterior capsule. -
Which symptom pattern do patients with atopic cataract describe?
Patients complain of blurred vision, glare and difficulty in bright light, and they often notice that vision fluctuates with the size of the pupil. -
Which atopic dermatitis patients have the highest frequency of cataract?
Cataract affects a minority of patients with atopic dermatitis, and the frequency is higher in those with severe disease and with keratoconjunctivitis. -
What supports a role for atopic disease itself, rather than steroids, in cataract formation?
Although long-term corticosteroids are a proposed contributor, some patients develop lens changes without any steroid exposure, which supports a role for the disease itself. -
Why should intraocular pressure be measured in a patient with atopic cataract?
Steroid use is common in atopic patients and can cause glaucoma, so intraocular pressure should be measured as part of the assessment. -
Which corneal condition should corneal topography look for in atopic cataract?
Keratoconus is associated with atopy and chronic eye rubbing and can progress rapidly in young patients, so topography is part of the work-up. -
Which cataract shows a rosette pattern after a blow to the eye?
Traumatic cataract follows a blow or a penetrating injury and often shows a rosette pattern, which separates it from the atopic anterior plaque. -
Which steroid-sparing agents help control ocular surface inflammation in atopic disease?
Early control of the skin and ocular surface inflammation is the first step, using steroid-sparing agents such as topical calcineurin inhibitors where possible. -
Which intraoperative problems should be anticipated during atopic cataract surgery?
The surgeon should expect zonular weakness and anterior capsular contraction, and should have capsular tension devices available and plan a well-sized capsulorhexis.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.