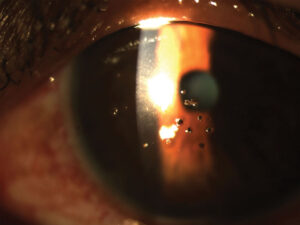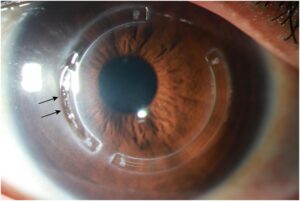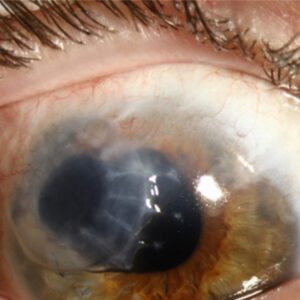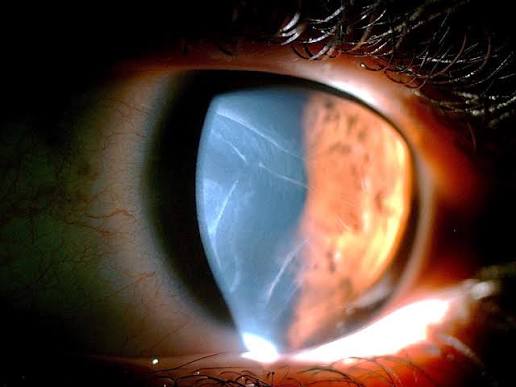
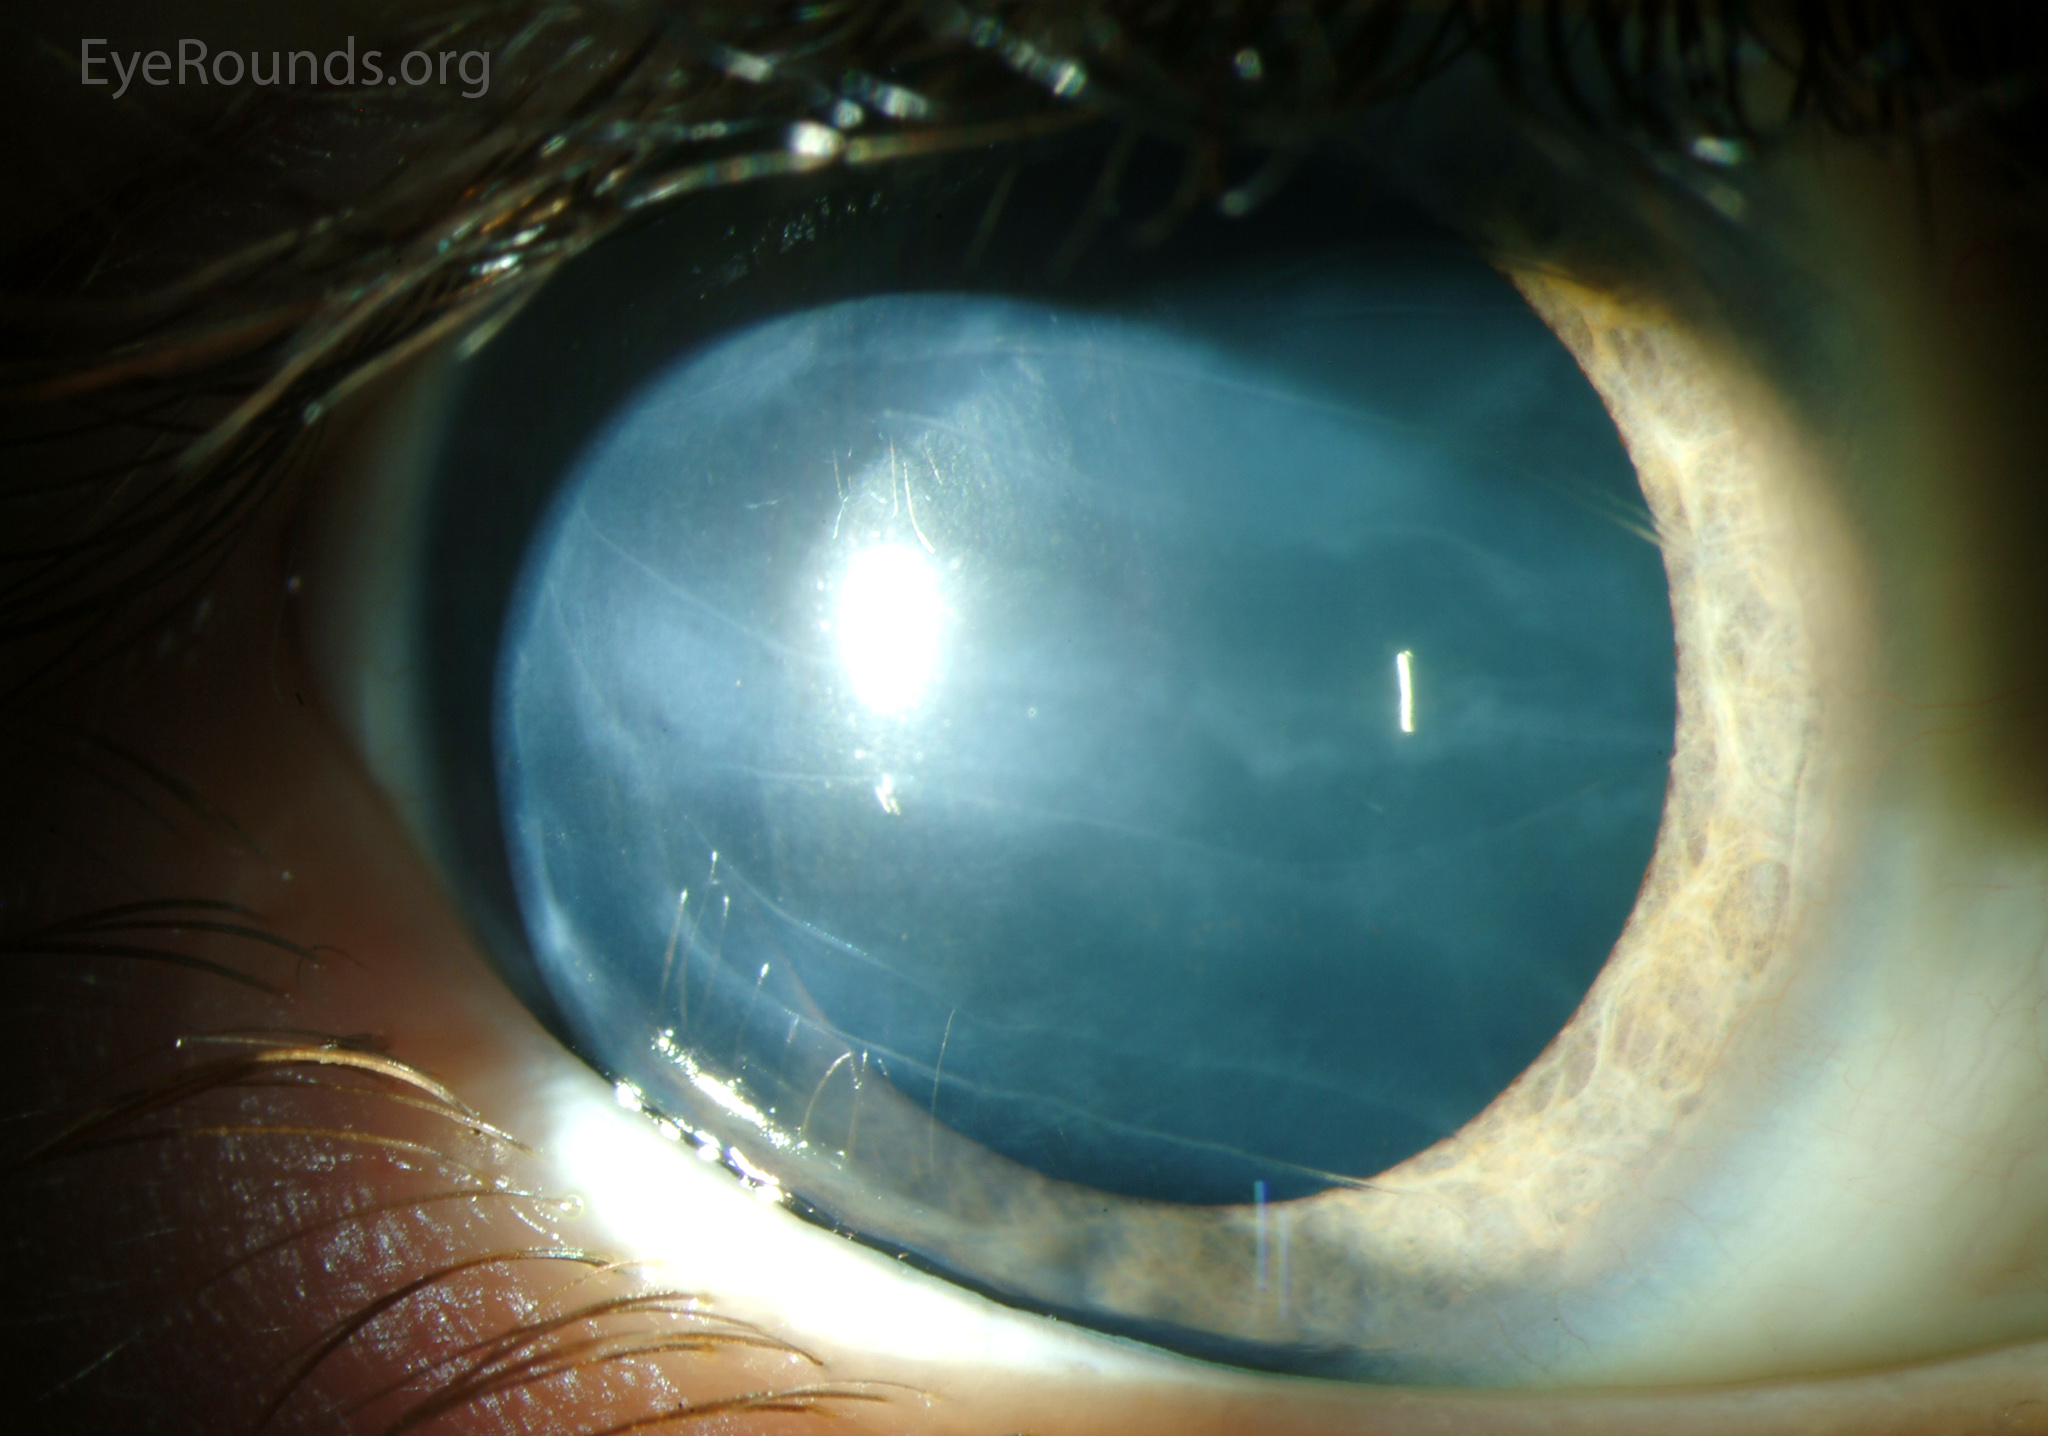
In an infant with a cloudy, enlarged cornea, the finding that settles the diagnosis is often a set of lines.
When the pressure in the eye is high, the cornea stretches, and Descemet membrane, which is not elastic, tears.
The tears are called Haab striae, after Otto Haab, who described them in the late nineteenth century, and they are one of the cardinal signs of primary congenital glaucoma.
How they form
Descemet membrane is a thin, rigid basement membrane secreted by the endothelium.
When intraocular pressure is raised in a young eye, the cornea and sclera are still elastic, so the globe enlarges (buphthalmos), and the cornea stretches.
Descemet membrane cannot stretch, so it splits.
The edges of the break curl, aqueous leaks into the stroma, and the area of the tear becomes edematous.
After the edema subsides, the break heals and appears as a ridge of new basement membrane with a clear, glassy border.
Appearance
- Curvilinear, often horizontal or concentric with the limbus, double-contoured lines on the posterior cornea
- Multiple parallel lines, sometimes arranged like railway tracks
- Seen on retroillumination as ridges with a clear central zone
- Often accompanied by diffuse corneal edema, enlarged corneal diameter (over 12 mm in infants), and a deepened anterior chamber
- Associated tearing, photophobia, and blepharospasm, the classic triad (see primary congenital glaucoma)
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteDistinguishing them from other Descemet breaks
Birth trauma from forceps delivery produces a single, usually vertical or oblique, curved tear in the left eye more often, and it is unilateral.
It lies in a normal-sized cornea with normal pressure.
Haab striae tend to be horizontal, multiple, and in an enlarged cornea with elevated pressure.
In keratoconus, breaks occur in acute hydrops (see corneal hydrops).
Posterior polymorphous dystrophy also produces band-like lesions, but they are not associated with corneal enlargement.
Other causes of a large, cloudy cornea in infants
Megalocornea has a clear cornea of normal pressure (see megalocornea).
Congenital hereditary endothelial dystrophy, Peters anomaly, and birth trauma, along with metabolic storage disorders, can all cloud the cornea, but the combination of enlargement and Haab striae points toward glaucoma (see Peters anomaly).
Evaluation
An examination under anesthesia is often needed for an infant.
It includes measurement of corneal diameter, intraocular pressure, gonioscopy to assess the angle, optic disc cupping, and axial length.
Systemic associations to consider include Sturge-Weber syndrome, Axenfeld-Rieger syndrome, and aniridia (see Sturge-Weber syndrome).
Management
Primary congenital glaucoma is treated surgically.
Goniotomy or trabeculotomy is the first choice in most cases, and medical therapy bridges the time to surgery.
Early treatment is crucial to prevent optic nerve damage and amblyopia, and the cornea often clears once the pressure is controlled, though the striae remain as permanent scars.
Looking for the signs in an infant
In a baby with watering eyes, light sensitivity, and a hazy cornea, measure the horizontal corneal diameter, which is above 11 mm in a newborn and above 12 mm in a child under one year in typical congenital glaucoma. Look for Haab striae with retroillumination, since they can be hard to see in an edematous cornea. Measure the pressure, though the readings under anesthesia can be lower than in the awake child, and examine the optic disc for increased cupping, which may be reversible if the pressure is lowered early.
Why an examination under anesthesia is often necessary
Babies do not tolerate detailed examination awake. Under anesthesia, the surgeon can measure the pressure and corneal diameter, perform gonioscopy, assess the disc, take photographs, and treat in the same session. Because anesthetic agents affect the pressure, the findings should be interpreted with that in mind, and a combination of signs is more reliable than a single number.
Long-term outlook
The striae remain visible for life as ridges in the posterior cornea. Many children have good vision after successful surgery, but they need lifelong monitoring, correction of myopia and astigmatism, and amblyopia treatment. Parents should be told that the disease is chronic and that regular review prevents late loss of vision.
Why early treatment prevents amblyopia
In an infant, corneal clouding and high astigmatism from corneal stretching interfere with visual development, and the eye may become amblyopic even after the pressure is controlled. Early surgery, correction of refractive error, and patching of the better eye when needed are all part of the plan.
Prognosis
The visual outcome depends on how early the disease is diagnosed and how well the pressure is controlled.
Haab striae do not usually affect vision unless they cross the visual axis, and astigmatism and amblyopia must be managed.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- deLuise VP, Anderson DR. Primary infantile glaucoma (congenital glaucoma). Surv Ophthalmol. 1983;28:1-19.
- Papadopoulos M, Cable N, Rahi J, Khaw PT; BIG Eye Study Investigators. The British Infantile and Childhood Glaucoma (BIG) Eye Study. Invest Ophthalmol Vis Sci. 2007;48:4100-4106.
- Mandal AK, Chakrabarti D. Update on congenital glaucoma. Indian J Ophthalmol. 2011;59(Suppl):S148-S157.
- Kanski JJ, Bowling B. Clinical Ophthalmology: A Systematic Approach. 7th ed. London: Elsevier; 2011.
Test yourself
A few questions straight from this article.
-
Haab striae in primary congenital glaucoma represent breaks in which corneal layer?
Haab striae are tears in Descemet membrane, a thin rigid basement membrane secreted by the endothelium, produced when the cornea stretches under raised pressure. -
Why does Descemet membrane tear when intraocular pressure is raised in an infant eye?
In a young eye the cornea and sclera are still elastic, so the globe enlarges and the cornea stretches; the rigid Descemet membrane cannot follow and splits. -
Which examination technique best reveals Haab striae in an infant with a hazy cornea?
On retroillumination the striae appear as double-contoured ridges with a clear central zone, which matters because they are hard to see in an edematous cornea. -
In typical congenital glaucoma, which horizontal corneal diameter is exceeded in a child under one year?
Corneal diameter exceeds 11 mm in a newborn and 12 mm in a child under one year in typical congenital glaucoma, reflecting the stretching of buphthalmos. -
Which feature distinguishes forceps birth-trauma Descemet tears from Haab striae?
Forceps injury causes a single, usually vertical or oblique curved tear, unilateral and more often in the left eye, in a normal-sized cornea with normal pressure. -
Posterior polymorphous dystrophy can mimic Haab striae but differs in which respect?
Posterior polymorphous dystrophy also produces band-like posterior corneal lesions, but corneal enlargement is absent, unlike the buphthalmic eye of congenital glaucoma. -
Which triad classically accompanies Haab striae in primary congenital glaucoma?
Watering, light sensitivity and lid squeezing form the classic presenting triad alongside corneal haze and corneal enlargement. -
What is the first-choice treatment in most cases of primary congenital glaucoma?
Primary congenital glaucoma is treated surgically, with goniotomy or trabeculotomy the first choice; medical therapy only bridges the time to surgery. -
How should intraocular pressure readings taken under anesthesia in an infant be interpreted?
Anesthetic agents affect intraocular pressure and readings under anesthesia can be lower than awake values, so a combination of signs beats any single number. -
What becomes of Haab striae after intraocular pressure is successfully controlled?
The cornea often clears once pressure is controlled, but the healed Descemet breaks remain for life as ridges, affecting vision only if they cross the visual axis.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.