
Distichiasis is the presence of an accessory row of eyelashes emerging from the orifices of the meibomian glands along the posterior lid margin, growing in a location where lashes are not normally found and typically oriented to point back toward the ocular surface.
It is anatomically distinct from both entropion (where the lid margin itself is malpositioned) and ordinary trichiasis (where normal lash follicles are misdirected), because here the follicles themselves are abnormal in both number and location from the outset, a distinction that directly shapes how the condition is treated.
Congenital Distichiasis
Congenital distichiasis can occur as an isolated finding or as part of lymphedema-distichiasis syndrome, an autosomal dominant condition caused by mutations in FOXC2 that combines distichiasis with lower-extremity lymphedema, typically developing at puberty or later.
The lymphedema and the eyelash finding do not necessarily present simultaneously, and the ocular finding often precedes the limb swelling by years.
A patient (or family) presenting with distichiasis, with a family history of either finding, should be asked specifically about lymphedema, because recognizing the syndrome has implications well beyond the eye.
Because the lymphedema often does not appear until puberty, a young child presenting with isolated distichiasis and no visible swelling has not necessarily been excluded from the syndrome, and ongoing awareness of the possibility should be carried forward rather than dismissed after a single, early, reassuring exam.
Associated Systemic and Ocular Features of Lymphedema-Distichiasis Syndrome
- Lower-extremity lymphedema, usually developing around puberty
- Distichiasis, often bilateral
- Ptosis, in some affected individuals
- Additional eyelid anomalies (ectropion, in some cases)
- Cardiac defects and cleft palate, reported in a subset of cases, reflecting the broader developmental role of the affected gene
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteAcquired Distichiasis
Acquired distichiasis is far less common than the congenital form and has been reported following chronic eyelid inflammation, cicatrizing conjunctival disease (Stevens-Johnson syndrome, ocular cicatricial pemphigoid), and, as a consequence of certain systemic medications.
Most recognized among these are the eyelash-growth-promoting effects of some glaucoma prostaglandin analogs, which produce an unwanted, though generally reversible, related lash change rather than true distichiasis in most reported cases.
It is worth distinguishing simple lash overgrowth as a medication side effect from genuine accessory-follicle distichiasis when evaluating a patient on these drops, since the former typically resolves or improves after stopping the medication while true distichiasis does not.
Clinical Presentation
Symptoms depend heavily on how coarse the accessory lashes are and how directly they contact the ocular surface: fine, soft accessory lashes may cause minimal or no symptoms, while coarser lashes in direct, sustained contact with the cornea produce the same mechanical irritation syndrome as any other cause of trichiasis.
This includes foreign-body sensation, tearing, redness, and photophobia, with a real risk of corneal epithelial breakdown, scarring, and secondary infection if the mechanical irritation is significant and left untreated, particularly in a young child who may not reliably report or localize the discomfort.
Exam Findings
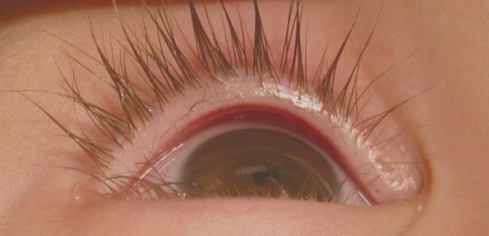
- An accessory row of lashes emerging from meibomian gland orifices along the posterior lid margin, best appreciated on careful slit-lamp exam of the lid margin, sometimes requiring magnification given how fine some of the accessory lashes can be
- The normal anterior lash row remains present and normally positioned, distinguishing this from entropion where the entire lid margin (and its normal lashes) rotates inward
- Corneal fluorescein staining corresponding to areas of lash-corneal contact when symptomatic
- Associated lymphedema of the lower extremities when the syndromic form is present, though this may not be obvious unless specifically examined for, particularly in a young patient before lymphedema has become clinically apparent
Differential Diagnosis
- Trichiasis without distichiasis — misdirected lashes from the normal, single anterior lash row rather than an accessory posterior row
- Entropion — inward rotation of the entire lid margin, discussed in its own dedicated article on this site
- Prostaglandin-associated eyelash changes — increased length, thickness, and number of normally positioned lashes from topical glaucoma medication, rather than a true accessory row from meibomian gland orifices
Management
Sparse, fine, minimally symptomatic accessory lashes can be observed or managed with simple mechanical epilation, though this offers only temporary relief since the follicle remains and the lash regrows over subsequent weeks.
For more significant, symptomatic distichiasis, definitive follicle destruction is needed for lasting relief, since epilation alone addresses only the visible lash and not the persistent follicle producing it.
Options include electrolysis, cryotherapy applied to the posterior lid margin, and, for more extensive or refractory disease, surgical approaches such as lid margin splitting with direct visualization and ablation or excision of the abnormal follicles.
Because the accessory lash row typically involves a broader portion of the lid margin rather than an isolated trichiasis, treatment often needs to address multiple follicles or an extended segment of the lid rather than a few individually identified lashes.
Recurrence after any single treatment session is common enough that patients should be counseled to expect the possible need for repeated treatment.
Follow-up examination after treatment focuses both on confirming the abnormal follicles have been adequately destroyed and on watching for the specific complications that can follow aggressive lid margin treatment, such as notching or misdirection of the normal anterior lashes if the destructive procedure inadvertently affects adjacent, normal follicles.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Brice G, Mansour S, Bell R, et al. Analysis of the phenotypic abnormalities in lymphoedema-distichiasis syndrome in 74 patients with FOXC2 mutations or linkage to 16q24. Journal of Medical Genetics.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 7: Orbit, Eyelids, and Lacrimal System.
Test yourself
A few questions straight from this article.
-
From which structures do the accessory lashes of distichiasis emerge?
Distichiasis is an accessory row of lashes growing from meibomian gland orifices, a site where lashes are not normally found, typically angled back toward the ocular surface. -
Which examination finding separates distichiasis from entropion?
In entropion the whole lid margin and its normal lashes rotate inward. In distichiasis the anterior row remains normal and an extra, abnormally sited row appears behind it. -
Which gene is mutated in lymphedema-distichiasis syndrome?
Lymphedema-distichiasis syndrome is an autosomal dominant condition caused by FOXC2 mutations, combining distichiasis with lower-extremity lymphedema. -
When does lymphedema typically appear in lymphedema-distichiasis syndrome?
The lower-limb swelling usually develops at puberty or later, so the eyelash finding often precedes it by years and a reassuring early exam in a child does not exclude the syndrome. -
Which systemic abnormalities are reported in a subset of lymphedema-distichiasis syndrome cases?
Cardiac defects and cleft palate are reported in a subset of affected individuals, reflecting the broader developmental role of the affected gene. Ptosis and ectropion also occur. -
Which ocular surface disorders have been reported to cause acquired distichiasis?
Acquired distichiasis is much rarer than the congenital form and follows chronic eyelid inflammation or cicatrizing conjunctival disease such as Stevens-Johnson syndrome and ocular cicatricial pemphigoid. -
How do prostaglandin-associated eyelash changes differ from true distichiasis?
Prostaglandin analogs lengthen and thicken lashes in their normal anterior position rather than creating an accessory row from meibomian orifices, and the change generally reverses after stopping the drop. -
Why does mechanical epilation give only temporary relief in distichiasis?
Epilation removes only the visible lash. The abnormal follicle persists and keeps producing lashes, which is why definitive follicle destruction is needed for lasting relief. -
Which treatments achieve definitive follicle destruction in symptomatic distichiasis?
These destroy or excise the abnormal follicles themselves. Because an accessory row usually spans a broad segment of lid margin, treatment must address an extended segment rather than a few individual lashes. -
Which complication should follow-up after aggressive lid margin treatment for distichiasis look for?
Destructive lid margin procedures can inadvertently damage adjacent normal follicles, producing notching or misdirected anterior lashes. Recurrence is also common enough that repeat treatment should be anticipated.
