
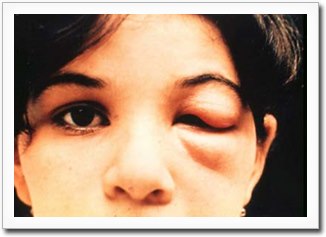
Chagas disease, caused by the protozoan parasite Trypanosoma cruzi and transmitted by triatomine (“kissing”) bugs, produces one of the more recognizable eponymous signs in tropical medicine when the parasite enters through the conjunctiva or periocular skin: Romana’s sign, a unilateral, usually painless swelling of the eyelids and periorbital tissue.
Named after Cecilio Romaña, the Argentine physician who described it in 1935, the sign remains clinically relevant wherever Chagas disease is endemic, largely across Latin America, though rising population movement has made it a consideration in non-endemic countries as well.
The finding matters because it identifies the site of parasite entry during the acute phase, at a point when the disease is far more treatable than it is once it progresses to the chronic cardiac or gastrointestinal complications that make Chagas disease so dangerous.
Mechanism
Infection typically occurs when triatomine bug feces, deposited near a bite wound on the skin, are inadvertently rubbed into the eye or an area of broken skin — the insect itself does not inject the parasite through its bite, which is why the periocular route of entry is so mechanistically direct and so classically described.
The resulting local inflammatory reaction at the conjunctiva and periorbital tissue produces the characteristic unilateral swelling, occurring days to a few weeks after exposure.
Because the sign is a local reaction to parasite entry rather than a systemic manifestation, it appears only in patients infected through this specific route and is absent in most Chagas disease cases acquired through blood transfusion, congenital transmission, or oral ingestion of contaminated food, where the acute phase is often asymptomatic or produces only nonspecific fever.
This route-dependence is a useful reminder that Romana’s sign, while classic, is only ever present in a minority of all Chagas disease cases overall — its absence never excludes the diagnosis in a patient with a compatible exposure history and other suggestive findings, and the great majority of acute infections instead pass unrecognized until chronic disease eventually surfaces, often decades later.
Clinical Findings
- Unilateral, painless edema of the upper and lower eyelids on the side of inoculation
- Conjunctival injection and chemosis on the affected side
- Preauricular and submandibular lymphadenopathy, often palpable on the same side
- Associated acute-phase systemic findings — fever, malaise, and occasionally hepatosplenomegaly — in a minority of patients
The absence of pain and itching, together with the striking unilaterality, is what distinguishes Romana’s sign clinically from more common causes of periorbital swelling such as allergic reaction, insect bite hypersensitivity, or preseptal cellulitis, though in practice these alternatives are still the more statistically likely explanation outside endemic areas and need to be actively excluded.
Because the acute phase can otherwise be entirely asymptomatic or produce only vague, nonspecific fever, Romana’s sign is sometimes the single visible clue prompting the entire diagnostic workup, giving it outsized clinical importance relative to how rarely it actually occurs among all infected patients.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteDifferential Diagnosis
- Preseptal or orbital cellulitis — usually painful, with erythema and warmth, and a source of local infection
- Allergic contact dermatitis or insect bite reaction — typically itchy, sometimes bilateral, with a clear exposure history
- Angioedema — can be unilateral but usually evolves faster (hours) and may involve other facial or mucosal sites
- Dacryoadenitis or dacryocystitis — localized to the lacrimal gland or sac region rather than diffuse periorbital swelling
A history of residence in or travel to an endemic region, exposure to rural or peri-domestic housing where triatomine bugs live, and the painless, unilateral quality of the swelling together should prompt specific consideration of Chagas disease rather than treating it as a routine periorbital infection.
Diagnosis
During the acute phase, direct visualization of trypomastigotes on peripheral blood smear, or PCR-based detection of parasite DNA, confirms the diagnosis while parasitemia is still high enough to detect.
Serologic testing (requiring at least two different assays for confirmation, per most national guidelines) is used for chronic-phase diagnosis, once parasitemia has dropped below the detection threshold of direct methods.
A high index of suspicion in a returning traveler or immigrant from an endemic area with compatible findings is often what actually triggers testing in a non-endemic setting, since the diagnosis is easy to overlook entirely by clinicians unfamiliar with the disease’s regional epidemiology.
Management
Antitrypanosomal treatment — benznidazole or nifurtimox — is most effective when started during the acute phase, which is precisely why recognizing Romana’s sign and other acute presentations promptly matters clinically.
Efficacy declines, though treatment is still often recommended, as the disease moves into the chronic phase, and the periorbital swelling itself resolves as the acute infection is treated and typically leaves no lasting ocular sequelae.
Beyond the acute presentation, the real long-term stakes of Chagas disease are cardiac (chronic Chagas cardiomyopathy) and gastrointestinal (megaesophagus, megacolon), which is why any patient in whom the diagnosis is confirmed needs baseline and ongoing screening for these complications regardless of how mild the initial ocular presentation was.
Coordination with infectious disease and, once cardiac or gastrointestinal involvement is identified, the relevant specialists is standard, and the ophthalmologist’s role — having potentially been the clinician who first raised the diagnosis from a periocular finding — is often simply to ensure the patient is appropriately connected to that broader, longer-term system of care that ultimately matters far more for the patient’s outcome than the resolved eyelid swelling itself.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Rassi A Jr, Rassi A, Marin-Neto JA. Chagas disease. Lancet.
- Pérez-Molina JA, Molina I. Chagas disease. Lancet.
- World Health Organization. Chagas disease (American trypanosomiasis) fact sheet.
- Bern C. Chagas’ disease. New England Journal of Medicine.
Test yourself
A few questions straight from this article.
-
Which organism causes Chagas disease?
Chagas disease is caused by the protozoan parasite Trypanosoma cruzi, transmitted by triatomine or kissing bugs, largely across Latin America. -
How does Trypanosoma cruzi typically enter the body in vector-borne Chagas disease?
The insect does not inject the parasite through its bite; infection follows triatomine faeces deposited near the bite being rubbed into the eye or broken skin. -
What does Romana's sign look like on examination?
Romana's sign is a unilateral, usually painless swelling of the eyelids and periorbital tissue marking the site of parasite entry, with conjunctival injection and chemosis on that side. -
Which additional finding commonly accompanies Romana's sign?
Preauricular and submandibular lymphadenopathy is often palpable on the same side as the periorbital swelling. -
Why is Romana's sign absent in most patients with Chagas disease?
The sign is a local reaction at the site of entry, so it is absent in infection acquired by transfusion, congenitally, or by ingestion; its absence never excludes the diagnosis. -
Which feature distinguishes Romana's sign from preseptal cellulitis?
Preseptal cellulitis is usually painful with erythema, warmth and a local source of infection, whereas Romana's sign is painless and non-itchy despite striking unilateral swelling. -
How is acute-phase Chagas disease confirmed in the laboratory?
During the acute phase parasitaemia is high enough for direct visualisation of trypomastigotes on smear or PCR detection of parasite DNA. -
How is chronic-phase Chagas disease diagnosed?
Once parasitaemia falls below the threshold of direct methods, diagnosis rests on serology, with most national guidelines requiring at least two different assays for confirmation. -
Which drugs treat Chagas disease, and when are they most effective?
Antitrypanosomal therapy with benznidazole or nifurtimox works best in the acute phase; efficacy declines in chronic disease, though treatment is still often recommended. -
Which long-term complications drive ongoing screening after confirmed Chagas disease?
The real long-term stakes are chronic Chagas cardiomyopathy and gastrointestinal disease, so every confirmed patient needs baseline and ongoing screening whatever the initial ocular picture.
