CASE REPORT
A 65-year-old female with a medical history of controlled hypertension presented with a sudden decrease in vision, severe eye pain, and redness in the right eye 48 hours after uncomplicated phacoemulsification cataract surgery.
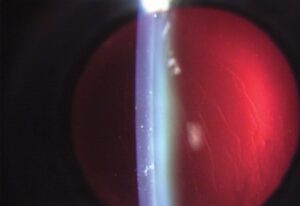
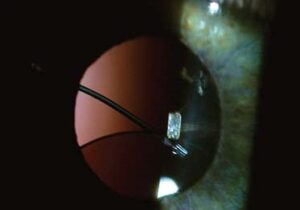
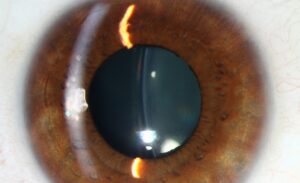
Clinical examination revealed reduced visual acuity to counting fingers at 1 meter, conjunctival injection, corneal edema, elevated intraocular pressure, and limited fundus examination due to corneal edema.
Despite initial concerns for postoperative infection, laboratory tests ruled out bacterial and fungal endophthalmitis, supported by the absence of vitritis and unresponsiveness to broad-spectrum antimicrobial therapy.
The diagnosis of Toxic anterior segment syndrome (TASS) was considered.
DISEASE
Toxic anterior segment syndrome (TASS) is an acute severe intraocular inflammation accompanied by diffuse corneal edema within 1-2 days of anterior segment surgery which is most commonly associated with cataract surgery.
TASS is a form of sterile, noninfectious endophthalmitis with or without pain, a marked decrease in vision, diffuse corneal edema that extends limbus to limbus, photophobia, and severe anterior chamber reaction, occasionally with hypopyon.
Toxic anterior segment syndrome (TASS) presents within 12-24 hours after surgery whereas infectious endophthalmitis typically develops 2-7 days after surgery. TASS is responsive to topical steroids in most cases.
The etiology of TASS may be multi-factorial with numerous potential causes.
- Bacterial endotoxins or particulate contamination of balanced salt solutions
- Intraocular irrigating solutions with abnormal PH, osmolarity, or ionic composition
- Denatured Ophthalmic viscosurgical Devices (OVD)
- Intraocular medications (antibiotics in the irrigation solutions or intracameral antibiotics)
- Topical ointments
- Inadequate sterilization of surgical instruments and tubing
- Inadequate flushing of instruments between cases resulting in build-up of ophthalmic viscosurgical devices (OVD)
- Preservatives
- Metallic precipitates
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteEye examination
A full examination is very important. Evaluation of visual acuity, pupil size and reaction, slit-lamp exam, eye pressure, and dilated fundus exam.
Symptoms
- Vision loss or blurry vision within 12-48 hours after surgery
- Pain ranging from mild to severe
- Photophobia
Signs
- The acute severe inflammatory reaction of the anterior chamber within 12-48 hours after surgery
- Corneal edema extending from limbus to limbus
- Dilated or irregular pupil
- Increased intraocular pressure
- Hypopyon
- Lack of bacterial or fungal growth from cultures of intraocular taps
- Good response to topical ophthalmic steroid drops
MANAGEMENT

Medical therapy
Most Toxic anterior segment syndrome (TASS) patients respond well to topical corticosteroids (1% Prednisolone acetate) given hourly. Mild or early cases will respond to steroids rapidly as evidenced by the clearing of the inflammation and a decrease in intraocular pressure.

In cases of moderate TASS, the clearing may take up to 3-6 weeks. In severe cases, which may need systemic steroids, there may be permanent damage, including persistent corneal edema, chronic persistent inflammation, fixed dilated pupils, refractory glaucoma secondary to trabecular meshwork damage, and cystoid macular edema.
Medical follow up
The patient should be followed very closely, especially for several hours and days after the onset of treatment. The patient needs to be evaluated for recovery and response rate.
The eye pressure, level of inflammation, and corneal recovery should be observed. A gonioscopy examination is necessary to rule out retained lens fragments.
Surgery
Toxic anterior segment syndrome (TASS) is a post-surgical event after an anterior segment surgery.
If TASS develops, then there is usually a need for intraocular aqueous and vitreous tap for culture. In severe cases of TASS with persistent corneal edema, patients may need corneal transplantation.
In refractory glaucoma, the eye pressure should be closely monitored. If the pressure is not responsive to medical management, glaucoma surgery may be necessary.
Of note, in a major outbreak of 147 eyes published by Oshika et al, 29.3% of cases required surgery, including irrigation of the anterior chamber, vitrectomy, and IOL removal.
Complications
- Severe inflammation
- Pain
- Vision loss
- Iris atrophy either dilated or irregular pupil
- Cornea endothelial damage with corneal edema
- Trabecular meshwork damage with possible secondary glaucoma
Prognosis
Most cases of Toxic anterior segment syndrome (TASS) are successfully treated with topical steroids, non-steroidal anti-inflammatory drops, or both.
If not resolved after 6 weeks, permanent damage is more likely to occur.
The intense inflammatory reaction can cause serious damage to intraocular tissues including the corneal endothelium, which results in cornea edema, iris (either dilated or irregular pupil, and atrophy), and trabecular meshwork damage with possible secondary glaucoma. Tissue damage can result in vision loss.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteREFERENCES
- Manson MC, Mamalis N, Olson RJ. Toxic anterior segment inflammation following cataract surgery. J Cataract Surg 1992; 18: 184-189
- Mamalis N, Edelhauser HF, Dawson DG, Chew J, LeBoyer RM, Werner L. Toxic anterioe segment syndrome. J Cataract Refract Surg 2006; 32: 324-333
- Carolee M. Cutler Peck, Jacob Brubaker, Sue Clouser, Chris Danford, Henry E. Edelhauser, Nick Mamalis Toxic anterior segment syndrome: Common causes Journal of Cataract & Refractive Surgery July 2010; Vol. 36(Issue 7): 1073-1080
- Oshika T, Eguchi S, Goto H, Ohashi Y. Outbreak of Subacute-Onset Toxic Anterior Segment Syndrome Associated with Single-Piece Acrylic Intraocular Lenses. Ophthalmology. 2017;124(4):519e23
- Hernandez-Bogantes E, Navas A, Naranjo A, Amescua G, Graue-Hernandez EO, Flynn HW Jr, Ahmed I. Toxic anterior segment syndrome: A review. Surv Ophthalmol. 2019;64(4):463-476.
Test yourself
A few questions straight from this article.
-
Toxic anterior segment syndrome after cataract surgery is best classified as which process?
TASS is a sterile, noninfectious endophthalmitis arising soon after anterior segment surgery, with no bacterial or fungal growth from cultures of intraocular taps. -
Which operating-room factor is a recognised cause of toxic anterior segment syndrome?
Recognised causes include inadequate sterilization and inadequate flushing of instruments between cases, allowing viscosurgical device residue to build up, as well as contaminated or abnormal irrigating solutions and preservatives. -
Which corneal finding is characteristic of toxic anterior segment syndrome?
TASS produces diffuse corneal edema that extends from limbus to limbus, together with a severe anterior chamber reaction and occasionally hypopyon. -
Infectious endophthalmitis after cataract surgery typically develops in which postoperative window?
Infectious endophthalmitis typically develops 2 to 7 days after surgery, later than toxic anterior segment syndrome, which appears in the first day or two. -
Which finding argues against infectious endophthalmitis and supports toxic anterior segment syndrome?
Hypopyon, pain, raised pressure and corneal edema all occur in TASS as well. Absence of vitritis with no bacterial or fungal growth, plus failure to respond to broad-spectrum antimicrobials, points to TASS. -
What is the first-line medical treatment for toxic anterior segment syndrome?
Most TASS patients respond well to hourly topical corticosteroid, prednisolone acetate 1%, with mild or early cases clearing rapidly and intraocular pressure falling. -
In moderate toxic anterior segment syndrome, how long may the inflammation take to clear?
Mild or early TASS clears rapidly on topical steroids, but in moderate cases the inflammation may take 3 to 6 weeks to clear. -
Failure of toxic anterior segment syndrome to resolve by which point makes permanent damage more likely?
Most cases are treated successfully with topical steroids, non-steroidal anti-inflammatory drops or both; if the inflammation has not resolved after 6 weeks, permanent damage is more likely. -
Secondary glaucoma following toxic anterior segment syndrome results from damage to which structure?
The intense inflammatory reaction damages the trabecular meshwork and can cause refractory secondary glaucoma; if pressure resists medical management, glaucoma surgery may be needed. -
During follow-up of toxic anterior segment syndrome, gonioscopy is performed to exclude which finding?
Alongside monitoring intraocular pressure, inflammation and corneal recovery, a gonioscopy examination is necessary to rule out retained lens fragments.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.