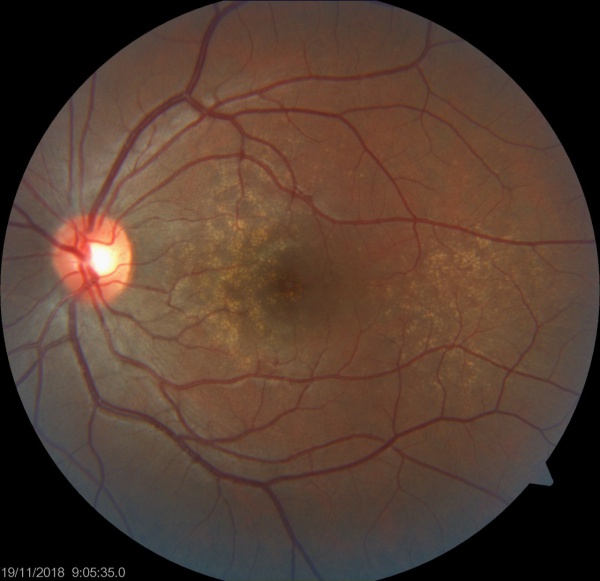
Basal laminar drusen are numerous small, round, yellow deposits at the level of the retinal pigment epithelium (RPE). Ophthalmologists also call them cuticular drusen. They usually affect both eyes of adults in their 30s to 60s, and vision is often normal at first.
Most patients need monitoring, not treatment. The visual risks are a vitelliform (egg-yolk) detachment, choroidal neovascularization (CNV), and geographic atrophy (GA). A kidney connection also exists, so the workup sometimes reaches beyond the eye.
What are basal laminar drusen and cuticular drusen?
Basal laminar drusen and cuticular drusen are two names for the same uncommon entity, abbreviated BLD in the retina literature. Clinicians first thought it was separate from age-related macular degeneration (AMD). Most now place it on the same spectrum as macular degeneration, with a distinct appearance and a younger onset.
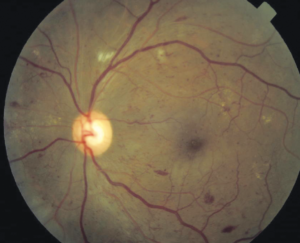
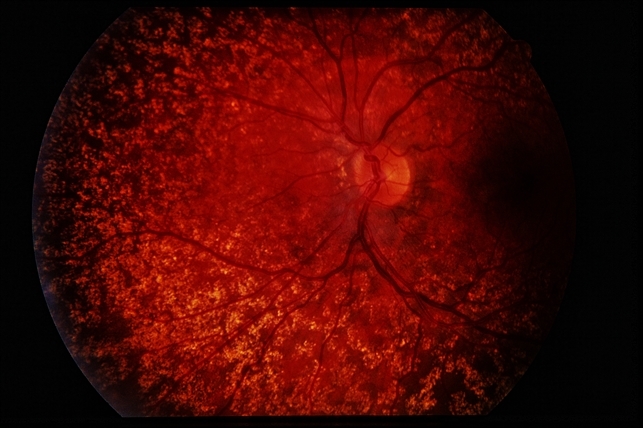
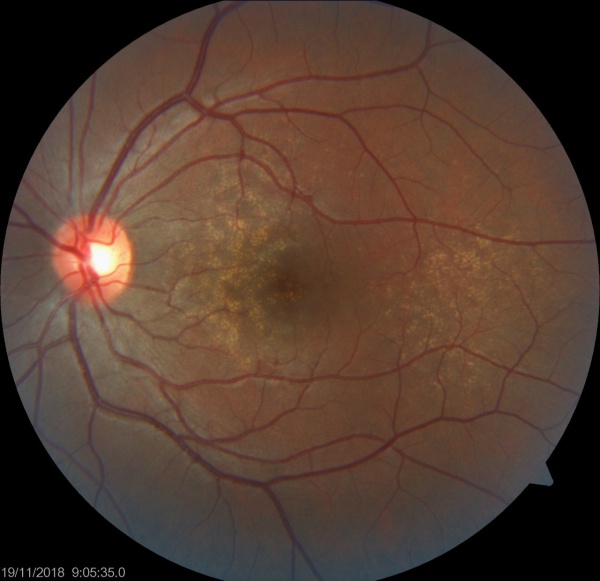
On examination, you see many small yellow drusen scattered through the macula, often more than 100 per eye. They are more obvious on fundus autofluorescence than on ophthalmoscopy. The size is usually 25 to 75 microns, much smaller than typical soft drusen.
Visual acuity often stays good for decades. Some patients notice blur, metamorphopsia, or a central patch of distortion when a vitelliform lesion forms. Others are found by chance on a routine dilated exam.
Case report: basal laminar drusen in a 65-year-old woman
A 65-year-old woman complained of blurred vision in both eyes. At her first ophthalmic examination, her visual acuity was 20/20 in both eyes. Ophthalmoscopy showed many small sub-RPE deposits in both eyes.
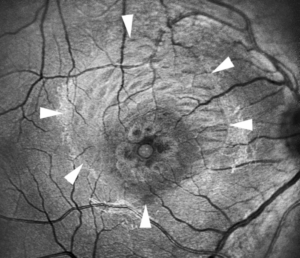
Spectral-domain OCT showed nodular RPE elevations with a saw-tooth pattern. This blunted triangular or prolapsed shape has been reported as typical for cuticular drusen. Reticular pseudodrusen were also present in both eyes.
The scotopic and photopic full-field electroretinograms were reduced. Goldmann perimetry showed decreased sensitivity in the pericentral field of both eyes. She received a diagnosis of cuticular drusen and went on a periodic follow-up schedule.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteHow do basal laminar drusen look on OCT?
On OCT, basal laminar drusen appear as small, dome-shaped or triangular RPE elevations that give the band a saw-tooth outline. The peaks are narrow and the spaces between them are shallow. This pattern separates them from the broader, rounder mounds of soft drusen in AMD.
OCT also shows the complications. A vitelliform lesion appears as hyperreflective material between the RPE and the ellipsoid zone, sometimes with subretinal fluid. GA shows as loss of the RPE with deeper light penetration. CNV shows as fluid, hemorrhage, or a pigment epithelial detachment with new vessels.
Reticular pseudodrusen can coexist, as in the case above. They sit above the RPE, not below it. For the difference, see drusen versus pseudodrusen.
Autofluorescence and fluorescein angiography in cuticular drusen
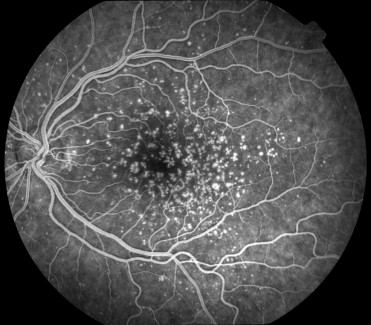
Fundus autofluorescence shows many small, discrete spots that are often more numerous than the yellow lesions you see clinically. Each spot is typically bright with a darker rim, spread across the macula and sometimes beyond the arcades. This makes autofluorescence the most sensitive screening image for the condition.
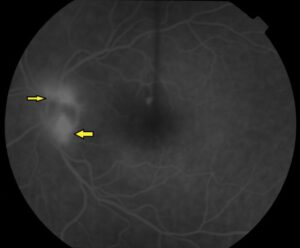
Fluorescein angiography (FA) shows punctate areas of early hyperfluorescence throughout the macula. The classic description is a “stars in the sky” pattern. The dots appear early in the angiogram and fade late, which sets them apart from the larger, later-staining drusen of AMD.
FA also helps when a patient reports new distortion. Leakage that grows over the transit suggests CNV, while pooling or staining in a vitelliform lesion is usually benign. OCT angiography now answers this question without dye in many clinics.
Basal laminar deposits versus basal linear deposits
Basal laminar deposit is a histologic term for thickened RPE basement membrane material. It lies between the RPE plasma membrane and the RPE basal lamina. Basal laminar drusen are the clinical lesions that correspond to nodular accumulations of this material.
Basal linear deposit is different. It sits external to the RPE basement membrane, in the inner collagenous layer of Bruch’s membrane. It is a lipid-rich, membranous material that is closely tied to soft drusen and to AMD progression.
- Basal laminar deposits: inside the RPE basement membrane, linked to cuticular drusen.
- Basal linear deposits: within Bruch’s membrane, linked to soft drusen and AMD.
Both can occur in the same eye. The location on histology is the real difference, and OCT cannot always separate them in a living patient. For clinical comparison of the drusen themselves, the review of drusen types covers hard, soft, and cuticular forms.
How is basal laminar drusen diagnosed?
Diagnosis of basal laminar drusen is clinical. It rests on dilated fundus examination, fundus autofluorescence, and FA. OCT adds the saw-tooth pattern and screens for complications.
The main differential includes early AMD with small hard drusen, Best vitelliform macular dystrophy when a yolk-like lesion forms, and pattern dystrophies. Age, bilateral symmetry, and the stars in the sky FA pattern usually settle the question. A vitelliform lesion in an older patient with many tiny drusen should raise this diagnosis.
Electroretinography can be reduced, as in the case above. This does not change the diagnosis, but it explains some patients who report symptoms out of proportion to their acuity.
Management of basal laminar drusen
No treatment removes the drusen. Patients should be monitored for a “pseudovitelliform” RPE lesion or detachment, CNV, or GA, any of which may reduce vision. Reasonable follow-up includes dilated exams, OCT, and a home Amsler grid, with prompt review for new distortion.
CNV is treated with anti-VEGF injections, as in AMD. Vitelliform lesions often resolve on their own, sometimes leaving atrophy, so most are observed. Genetic analysis for certain mutations may help guide patients who carry alleles associated with disease progression.
Is basal laminar drusen linked to kidney disease?
Yes, in some patients. The full pathophysiology of BLD has not been worked out, but a complement factor H (CFH) mutation has been implicated in membranoproliferative glomerulonephritis type 2 (MPGN type II, or dense deposit disease) and in atypical hemolytic uremic syndrome (aHUS).
Glomerulonephritis with isolated C3 deposits, a condition intermediate between MPGN and aHUS, also associates with CFH mutation. Renal function should be monitored in patients who present with BLD, especially at an early age, between 5 and 30 years.
There does not appear to be a correlation between the severity of kidney and eye disease. Even so, about 80% of patients with dense deposit disease present with cuticular drusen. When you find numerous cuticular drusen in a young patient, ask about urine abnormalities and refer for kidney evaluation.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteWhat is the prognosis?
Many patients keep useful vision for life. The outlook depends on whether a vitelliform lesion, CNV, or GA develops, and these usually appear after age 50. Regular follow-up lets you catch CNV early, when treatment protects vision best.
Counsel patients that the condition is chronic and usually bilateral. Their relatives may carry the same CFH variants, which adds weight to a family history of kidney disease or macular degeneration.
Test yourself
A few questions straight from this article.
-
How are basal laminar (cuticular) drusen currently classified in relation to age-related macular degeneration?
Although basal laminar drusen were originally thought to be a distinct entity, they are now regarded as lying within the same spectrum as macular degeneration. -
Which fundus appearance is characteristic of basal laminar drusen?
Examination shows numerous small yellow drusen, and these become far more obvious on fundus autofluorescence than on colour photography alone. -
What pattern does fluorescein angiography show in basal laminar drusen?
Fluorescein angiography demonstrates punctate areas of early staining scattered throughout the macula, described as a 'stars in the sky' pattern. -
Which SD-OCT appearance is reported as typical of cuticular drusen?
SD-OCT shows nodular elevations of the retinal pigment epithelium in a saw-tooth pattern, a blunted triangular or prolapsed shape reported as typical for cuticular drusen. -
On what is the diagnosis of basal laminar drusen based?
The diagnosis is clinical, resting on dilated fundus examination together with fundus autofluorescence and fluorescein angiography. -
Which developments should patients with basal laminar drusen be monitored for?
Vision loss in this condition comes from pseudovitelliform pigment epithelial lesions or detachment, choroidal neovascularization, and geographic atrophy, so follow-up targets those three. -
A mutation in which gene links basal laminar drusen to systemic renal disease?
A complement factor H mutation has been implicated in membranoproliferative glomerulonephritis type 2 (dense deposit disease) and in atypical haemolytic uraemic syndrome. -
Which additional monitoring is recommended for patients presenting with basal laminar drusen, especially at ages 5 to 30?
Because of the complement factor H association with glomerulonephritis and atypical haemolytic uraemic syndrome, renal function should be monitored, particularly when the drusen appear between 5 and 30 years of age. -
What proportion of patients with dense deposit disease present with cuticular drusen?
Eighty per cent of patients with dense deposit disease present with cuticular drusen, even though the severity of the renal and ocular disease does not correlate. -
What role does genetic analysis play in patients with basal laminar drusen?
Testing for certain mutations may be beneficial in guiding management for patients carrying known alleles associated with disease progression.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.