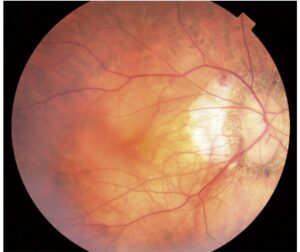
CRAO OCT imaging shows acute inner retinal swelling and hyperreflectivity, followed by progressive thinning and atrophy.
Central retinal artery occlusion (CRAO) causes sudden, painless, severe vision loss in one eye, and because the scan changes over time, each stage helps estimate the age of the injury.
Why the Inner Retina Takes the Injury
The central retinal artery supplies the inner retina, while the choroid nourishes the photoreceptors and usually remains perfused. As a result, damage follows a clear anatomical boundary on cross-sectional imaging.
Clinical Signs Before the Scan
Patients report abrupt monocular vision loss, and examination often reveals a relative afferent pupillary defect. The fundus shows retinal whitening, a cherry-red spot and attenuated arterioles. However, whitening may be subtle in the first hours, so OCT adds support when the fundus looks equivocal.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteAcute CRAO OCT Findings
Early scans show thickening and increased reflectivity of the inner retinal layers, and the boundaries between these layers blur. Cytotoxic edema likely explains both changes, because ischemic cells swell and scatter more light, while the outer retinal bands usually keep their expected position.
Shadowing on CRAO OCT
The bright, thickened inner retina attenuates the signal reaching deeper tissue, so the outer retina and pigment epithelium may appear dim. Do not interpret this dimming as primary photoreceptor infarction, but compare reflectivity with any spared area and repeat the scan later.
Prominent Middle Limiting Membrane Sign
Chu and colleagues described a hyperreflective band in the middle retina during acute arterial occlusion, which lies near the outer plexiform layer and may reflect early ischemic damage. However, its histologic basis remains uncertain, so treat it as a supporting sign.
Cilioretinal Sparing on CRAO OCT
A patent cilioretinal artery can preserve a zone of normal inner retina, and then OCT shows an abrupt transition between normal and swollen tissue. This zone may explain better central vision when it includes the papillomacular region.
Subacute Changes on CRAO OCT
Over the following weeks, inner retinal swelling gradually subsides. However, normal thickness does not indicate recovery, because layer definition usually remains poor. For this reason, inspect reflectivity and layer borders as well as the thickness map.
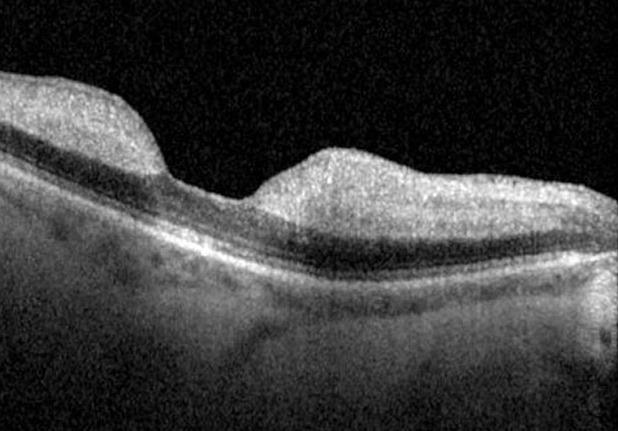
Late Atrophy on CRAO OCT
Months later, the inner retinal layers become thin and may merge into one band, while the outer retina often appears relatively preserved (see ellipsoid zone disruption). Vision may remain poor despite intact outer bands, because the signal pathway to the optic nerve is lost.
Grading Severity With CRAO OCT
Furashova and Matthé grouped OCT patterns into incomplete, subtotal and total grades, and in their study, more extensive structural changes were associated with worse visual acuity. Still, these findings do not support a validated individual prognosis.
What OCT Angiography Adds
OCT angiography can show reduced flow in the superficial and deep capillary plexuses, and en face OCT shows the geographic extent of inner retinal injury. However, poor fixation and reduced vision can create artifacts, so review the source B-scans before accepting an apparent flow defect.
Differential Diagnosis
Several conditions can mimic this pattern, so confirm the distribution and clinical course.
- Branch retinal artery occlusion: changes follow one arterial territory
- Paracentral acute middle maculopathy: a hyperreflective band mainly involves the inner nuclear layer
- Ophthalmic artery occlusion: inner and outer retinal injury, often without a cherry-red spot
- Commotio retinae: outer retinal changes follow blunt trauma
How CRAO OCT Affects Management
OCT supports the diagnosis, but it should never delay emergency referral. Acute CRAO is an ocular stroke, so patients need urgent vascular assessment, and older patients also need prompt evaluation for giant cell arteritis.
Observational data suggest possible benefit from early intravenous fibrinolysis, yet the treatment carries hemorrhage risk and evidence remains limited. Finally, no treatment has proven that it can reverse established inner retinal infarction.
Follow-Up After the Acute Event
Repeat OCT documents the shift from swelling to atrophy, but it cannot replace examination for neovascular complications. Therefore, check the iris and angle with gonioscopy, and coordinate cardiovascular risk management with the stroke team.
Pitfalls to Avoid
- Do not delay stroke referral to obtain imaging
- Avoid mistaking early shadowing for outer retinal infarction
- Do not read normal thickness as tissue recovery
- Avoid predicting outcome from one scan alone


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Hayreh SS, Zimmerman MB. Central retinal artery occlusion: visual outcome. Am J Ophthalmol. 2005;140:376-391.
- Ahn SJ, Woo SJ, Park KH, et al. Retinal and choroidal changes and visual outcome in central retinal artery occlusion: an optical coherence tomography study. Am J Ophthalmol. 2015;159:667-676.
- Chu YK, Hong YT, Byeon SH, Kwon OW. In vivo detection of acute ischemic damages in retinal arterial occlusion with optical coherence tomography: a “prominent middle limiting membrane sign”. Retina. 2013;33:2110-2117.
- Furashova O, Matthé E. Retinal changes in different grades of retinal artery occlusion: an optical coherence tomography study. Invest Ophthalmol Vis Sci. 2017;58:5209-5216.
- Chen H, Xia H, Qiu Z, Chen W, Chen X. Correlation of optical intensity on optical coherence tomography and visual outcome in central retinal artery occlusion. Retina. 2016;36:1964-1970.
- Mac Grory B, Schrag M, Biousse V, et al. Management of central retinal artery occlusion: a scientific statement from the American Heart Association. Stroke. 2021;52:e282-e294.
Test yourself
A few questions straight from this article.
-
Why does central retinal artery occlusion damage the inner retina while the photoreceptors are usually spared?
The central retinal artery supplies the inner retina, while the choroid nourishes the photoreceptors and usually stays perfused. Damage therefore follows a clear anatomical boundary on OCT. -
What does OCT typically show in acute central retinal artery occlusion?
Early scans show thickening and increased reflectivity of the inner retinal layers with blurred boundaries. Cytotoxic edema likely explains both, as ischemic cells swell and scatter more light. -
On acute CRAO OCT, the outer retina and pigment epithelium may look dim. How should this be interpreted?
The thickened, hyperreflective inner retina attenuates the signal reaching deeper tissue. Do not read this dimming as photoreceptor infarction; compare with any spared area and repeat the scan later. -
In central retinal artery occlusion, a patent cilioretinal artery produces which OCT appearance?
A patent cilioretinal artery can preserve a zone of normal inner retina, giving an abrupt transition to swollen tissue. This may explain better central vision when the zone includes the papillomacular region. -
Weeks after central retinal artery occlusion, inner retinal thickness returns to normal on OCT. What does this indicate?
Inner retinal swelling gradually subsides over weeks, but normal thickness does not mean recovery because layer definition usually stays poor. Inspect reflectivity and layer borders as well as the thickness map. -
Months after central retinal artery occlusion, why may vision stay poor even though the outer retinal bands look intact on OCT?
Late scans show thin inner retinal layers that may merge into one band, while the outer retina often looks relatively preserved. Vision may remain poor because the signal pathway to the optic nerve is lost. -
In the Furashova and Matthé OCT grading of retinal artery occlusion, what were more extensive structural changes associated with?
Furashova and Matthé grouped OCT patterns into incomplete, subtotal and total grades, and more extensive changes were associated with worse acuity. These findings do not support a validated individual prognosis. -
Which feature distinguishes ophthalmic artery occlusion from central retinal artery occlusion?
Ophthalmic artery occlusion causes inner and outer retinal injury, often without a cherry-red spot. Central retinal artery occlusion characteristically spares the outer retina, which the choroid supplies. -
A patient has acute central retinal artery occlusion and OCT is not immediately available. What is the priority?
OCT supports the diagnosis but should never delay emergency referral. Acute CRAO is an ocular stroke needing urgent vascular assessment, and older patients also need prompt evaluation for giant cell arteritis. -
During follow-up after central retinal artery occlusion, why is repeat OCT insufficient on its own?
Repeat OCT documents the shift from swelling to atrophy but cannot replace examination for neovascular complications. Check the iris and angle with gonioscopy and coordinate cardiovascular risk management with the stroke team.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.