
Corneal graft rejection is an immune-mediated response against donor corneal tissue, and it remains the leading cause of graft failure after penetrating keratoplasty.
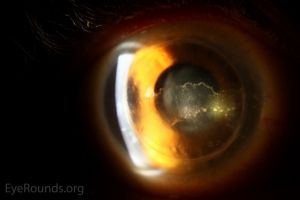
However, the cornea’s relative immune privilege — it is normally avascular and has reduced antigen-presenting cell density — gives corneal transplants a substantially better rejection-free survival rate than most other solid organ transplants, usually without the need for systemic immunosuppression.
Why the Cornea Is Different
The cornea’s avascularity limits access of immune cells and antibodies to the graft, and the anterior chamber has its own additional layer of immune modulation (anterior chamber-associated immune deviation) that further dampens the rejection response.
This combination is why most corneal transplants succeed with only topical, rather than systemic, immunosuppression.
But it also means that anything that disrupts this privilege (prior graft failure, deep stromal vascularization, active inflammation, a large or eccentric graft close to the limbus) substantially raises rejection risk by giving the immune system easier access to donor tissue.
Types of Rejection
- Epithelial rejection — a rejection line of donor epithelial cells being replaced by host cells, often subtle and self-limited, sometimes missed entirely
- Subepithelial (stromal) rejection — small subepithelial infiltrates, resembling those seen in adenoviral keratoconjunctivitis, generally mild
- Stromal rejection — diffuse stromal haze and edema, sometimes with an advancing rejection line, more visually significant than epithelial rejection
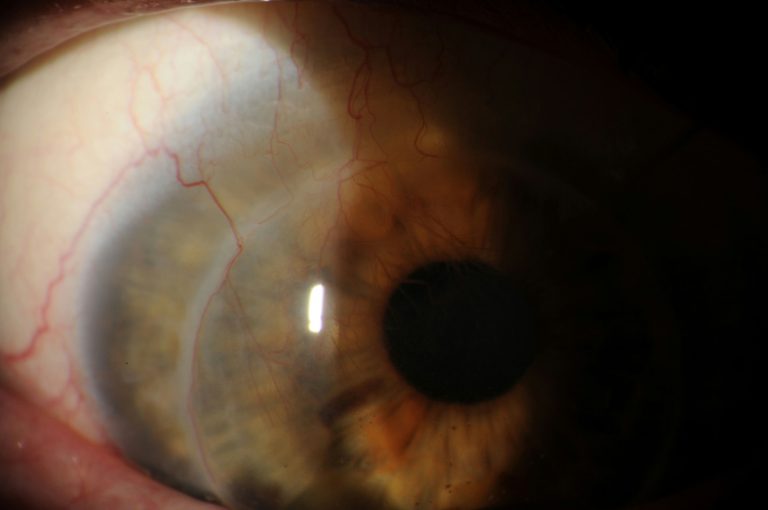
- Endothelial rejection — the most clinically significant form, marked by a linear or diffuse line of inflammatory cells (Khodadoust line) migrating across the endothelium, associated with corneal edema and carrying the greatest risk of permanent graft failure if not treated promptly
Endothelial rejection deserves the most urgent attention because the corneal endothelium does not regenerate in humans, so cell loss from a rejection episode is permanent.
Enough cumulative endothelial loss from repeated or severe rejection episodes leads to irreversible graft decompensation regardless of how well any single episode is ultimately treated.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteClinical Presentation
The classic teaching mnemonic — redness, sensitivity to light, decreased vision, and pain — captures the typical presentation reasonably well, though symptoms can be subtle, especially early or in mild epithelial rejection.
This is why patient education about seeking prompt evaluation for any new symptoms after keratoplasty is such an important part of routine post-transplant care.
Symptom onset can occur anytime after surgery, from weeks to many years later; risk does not simply disappear once the early postoperative period has passed.
This lifelong risk is part of why patients need durable, repeated education rather than a single explanation at the time of surgery, since a patient many years out from transplantation may reasonably have let their guard down about symptoms that once felt urgent and now seem like a distant concern.
Risk Factors
- Corneal vascularization, particularly deep stromal vessels extending close to or into the graft
- Prior graft rejection or failure in the same eye
- Large graft diameter or a graft placed eccentrically, closer to the limbus
- Active or recent ocular inflammation at the time of transplantation
- Younger patient age, associated with a more robust immune response
- Glaucoma or elevated intraocular pressure, which independently worsens graft survival
- Non-adherence to topical corticosteroid regimen
Differential Diagnosis
- Infectious keratitis in a graft — can mimic rejection, but typically has a more focal infiltrate, different risk factors (recent trauma, contact lens wear, suture-related), and requires an entirely different, urgent treatment approach
- Elevated intraocular pressure alone — can cause corneal edema resembling rejection without the cellular infiltrate; tonometry is essential to distinguish the two
- Primary graft failure — endothelial dysfunction present from the early postoperative period, related to donor tissue quality or surgical trauma rather than an immune-mediated process
- Recurrent original disease (for example, herpetic keratitis) in the graft
Distinguishing rejection from infection is particularly important because the initial treatments are opposite in direction: rejection calls for increased corticosteroids, while infection calls for controlling or reducing steroid use alongside targeted antimicrobial therapy.
As a result, getting this call right early changes the entire treatment trajectory, since treating a true infection with increased steroids alone could allow the infection to progress unchecked.
Management
Prompt, intensive topical corticosteroid therapy is the mainstay of treatment for an acute rejection episode, often started at high frequency (hourly or more) and tapered gradually as the episode resolves, with the specific regimen tailored to severity.
Severe or endothelial rejection unresponsive to topical treatment may require periocular or systemic corticosteroids.
Some high-risk grafts are managed with adjunctive systemic immunosuppression (such as topical or systemic cyclosporine or tacrolimus) even outside of an active rejection episode, aimed at reducing overall rejection risk in eyes with significant vascularization or a history of prior rejection, generally in coordination with a corneal specialist experienced in managing this specific category of high-risk transplant.
Long-term maintenance topical corticosteroid use, even in the absence of active rejection symptoms, remains standard for most grafts for an extended period, because abrupt discontinuation is a recognized trigger for rejection episodes.
This is one of the more important points of patient education, since well-meaning but premature self-discontinuation of drops is a preventable cause of graft loss, particularly once the eye looks and feels comfortable and the patient no longer perceives an ongoing need for treatment.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Panda A, Vanathi M, Kumar A, et al. Corneal graft rejection. Survey of Ophthalmology.
- Niederkorn JY. Immune mechanisms of corneal allograft rejection. Current Eye Research.
- Williams KA, Coster DJ. The immunobiology of corneal transplantation. Transplantation.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 8: External Disease and Cornea.
