Episcleritis vs scleritis is a daily decision in any clinic that sees red eyes.
Both conditions inflame the outer coat of the globe, and both can look sectoral and angry. However, episcleritis is usually benign and self-limiting, while scleritis can threaten sight and signal systemic vasculitis. Therefore, the examiner needs a fast and reliable way to separate them.
Episcleritis vs Scleritis: Anatomy First
The episclera is a thin vascular layer between Tenon capsule and the sclera, and its superficial plexus runs radially and moves freely over the deeper tissue. In addition, a deep episcleral plexus lies against the sclera and becomes engorged in scleritis. Because of this layering, vessel depth guides every bedside test below.
Pain in Episcleritis vs Scleritis
Pain is the most useful single symptom, and episcleritis causes mild irritation or tenderness while most patients keep working normally. In contrast, scleritis produces a deep, boring pain that radiates to the brow, temple or jaw. The pain often wakes the patient at night and responds poorly to simple analgesics, and the globe also feels tender through the closed lid.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteColor in Daylight
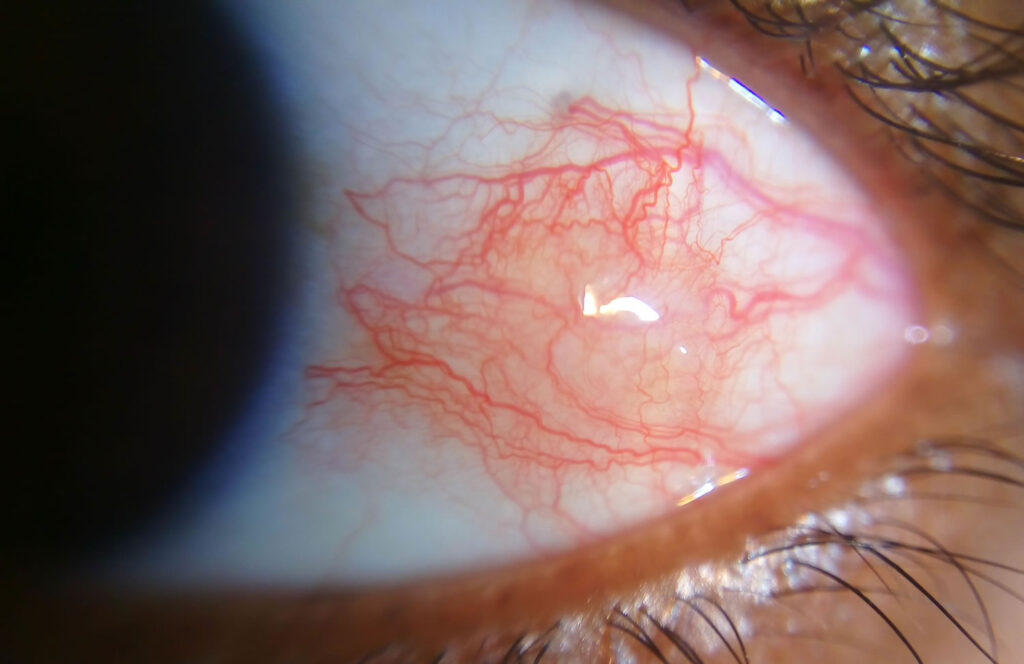
Look at the eye in natural light before using the slit lamp. Episcleritis appears bright red or salmon pink, while scleritis has a bluish violet hue because deep vessels and scleral edema lie beneath the surface.
Vessel Depth in Episcleritis vs Scleritis
A thin slit beam shows which layer is swollen, and in episcleritis the beam reveals episcleral swelling above a flat scleral surface. In scleritis, however, the sclera itself thickens, so the deep reflection of the beam bows forward, and red-free light makes the crisscrossing deep plexus easier to see.
Phenylephrine Test for Episcleritis vs Scleritis
Instill one drop of 10% phenylephrine and reexamine after 10 to 15 minutes. The superficial episcleral vessels then blanch and the redness clearly fades, while the deep plexus in scleritis stays congested, so persistent redness after the drop points toward scleral disease.
Nodules and Mobility
Nodular episcleritis forms a red, tender nodule that moves over the sclera. By contrast, nodular scleritis creates a firm nodule fixed to the deeper tissue. For example, a cotton tip slides the episcleral nodule gently, while the scleral nodule stays put.
Episcleritis vs Scleritis: Systemic Associations
Most episcleritis is idiopathic, although some cases accompany rosacea, atopy, gout or connective tissue disease. Scleritis, however, has a much stronger link with systemic disease, especially rheumatoid arthritis and ANCA associated vasculitis (see granulomatosis with polyangiitis), and infections such as herpes zoster, syphilis and tuberculosis also cause scleritis.
When to Order a Workup
Every patient with scleritis needs a systemic evaluation, even when the eye looks mild. First tests usually include blood count, ESR, CRP, rheumatoid factor, anti-CCP, ANCA, ANA, urinalysis, syphilis serology and chest imaging. Then the clinical pattern guides further testing (see scleritis classification and workup), and for episcleritis, reserve testing for recurrent, bilateral or atypical cases, or for systemic symptoms.
Urgency in Episcleritis vs Scleritis
Episcleritis rarely needs urgent review, whereas suspected scleritis needs prompt ophthalmic assessment. Necrotizing scleritis is an emergency because the sclera can melt and perforate, and uveitis, raised pressure or peripheral keratitis also signal a sight threatening process.
Treating Episcleritis
Simple episcleritis often settles within a few weeks without treatment, so reassurance, cold compresses and chilled artificial tears are often enough. A short topical steroid course or an oral NSAID helps persistent or nodular cases (see episcleritis treatment). However, repeated topical steroids risk cataract and raised pressure, so taper them early.
Treating Scleritis
Topical therapy alone does not control scleritis, while oral NSAIDs suit many cases of diffuse or nodular disease. If pain persists, systemic corticosteroids follow, then steroid sparing immunosuppression or biologics. For example, rituximab has a role in refractory ANCA associated scleritis, and rheumatology co-management also helps because the systemic disease often drives prognosis.
Painless Scleritis
Scleromalacia perforans breaks the pain rule and typically affects older women with longstanding rheumatoid arthritis. The sclera thins and reveals bluish uvea while inflammation stays minimal, so a quiet blue patch of sclera still demands systemic review.
Counseling the Patient
Explain that episcleritis rarely harms vision but may recur, and warn that severe pain, photophobia or blurred vision needs prompt review. For scleritis, explain why blood tests, long treatment and steady follow-up matter.
Episcleritis vs Scleritis at a Glance
- Pain: mild irritation versus deep, boring pain that wakes the patient
- Color: bright red versus bluish violet
- Vessels: superficial and mobile versus deep and fixed
- Phenylephrine: redness fades versus redness persists
- Workup: selective versus always
- Urgency: routine versus prompt, and emergency if necrotizing
Pitfalls to Avoid
- Do not treat suspected scleritis with topical drops alone
- Never skip the workup because the eye looks mild
- Also look for painless scleromalacia in rheumatoid arthritis
- Check the cornea for peripheral ulcerative keratitis


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Watson PG, Hayreh SS. Scleritis and episcleritis. Br J Ophthalmol. 1976;60:163-191.
- Sainz de la Maza M, Molina N, Gonzalez-Gonzalez LA, et al. Clinical characteristics of a large cohort of patients with scleritis and episcleritis. Ophthalmology. 2012;119:43-50.
- Akpek EK, Thorne JE, Qazi FA, et al. Evaluation of patients with scleritis for systemic disease. Ophthalmology. 2004;111:501-506.
- Jabs DA, Mudun A, Dunn JP, Marsh MJ. Episcleritis and scleritis: clinical features and treatment results. Am J Ophthalmol. 2000;130:469-476.
- Okhravi N, Odufuwa B, McCluskey P, Lightman S. Scleritis. Surv Ophthalmol. 2005;50:351-363.
Test yourself
A few questions straight from this article.
-
In episcleritis versus scleritis, which symptom is described as the most useful single distinguishing feature?
The article calls pain the most useful single symptom. Episcleritis causes mild irritation or tenderness, while scleritis produces a deep, boring pain radiating to the brow, temple or jaw. -
What color of redness in natural daylight suggests scleritis rather than episcleritis?
Scleritis looks bluish violet because deep vessels and scleral edema lie beneath the surface. Episcleritis appears bright red or salmon pink. -
How does the episcleral vascular anatomy explain the bedside difference between episcleritis and scleritis?
The episclera has a superficial radial plexus that moves freely, plus a deep plexus lying against the sclera. The deep plexus becomes engorged in scleritis, so vessel depth guides the bedside tests. -
On slit lamp examination of scleritis, what does a thin slit beam show?
In scleritis the sclera itself thickens, so the deep reflection of the slit beam bows forward. In episcleritis the beam shows swelling above a flat scleral surface. -
How is the 10% phenylephrine test interpreted when distinguishing episcleritis from scleritis, after 10 to 15 minutes?
Superficial episcleral vessels blanch and the redness fades in episcleritis. The deep plexus in scleritis stays congested, so persistent redness points toward scleral disease. -
How does a nodule in nodular episcleritis behave when moved with a cotton tip?
Nodular episcleritis forms a red, tender, mobile nodule that a cotton tip can slide. In nodular scleritis the nodule is firm and fixed to deeper tissue. -
Which systemic disease associations are especially strong for scleritis?
Scleritis has a much stronger link with systemic disease than episcleritis, especially rheumatoid arthritis and ANCA associated vasculitis. Infections such as herpes zoster, syphilis and tuberculosis can also cause it. -
Which patients with episcleritis should have a systemic workup, according to the approach for episcleritis?
Testing for episcleritis is reserved for recurrent, bilateral or atypical cases, or for systemic symptoms. Scleritis, by contrast, always needs a systemic evaluation, even when mild. -
Why is necrotizing scleritis considered an emergency?
Necrotizing scleritis is an emergency because the sclera can melt and perforate. Uveitis, raised pressure or peripheral keratitis also signal a sight threatening process. -
What is the appropriate initial treatment for simple episcleritis, which often settles within a few weeks?
Simple episcleritis often settles without treatment, so reassurance, cold compresses and chilled artificial tears are often enough. A short topical steroid or oral NSAID is reserved for persistent or nodular cases.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.