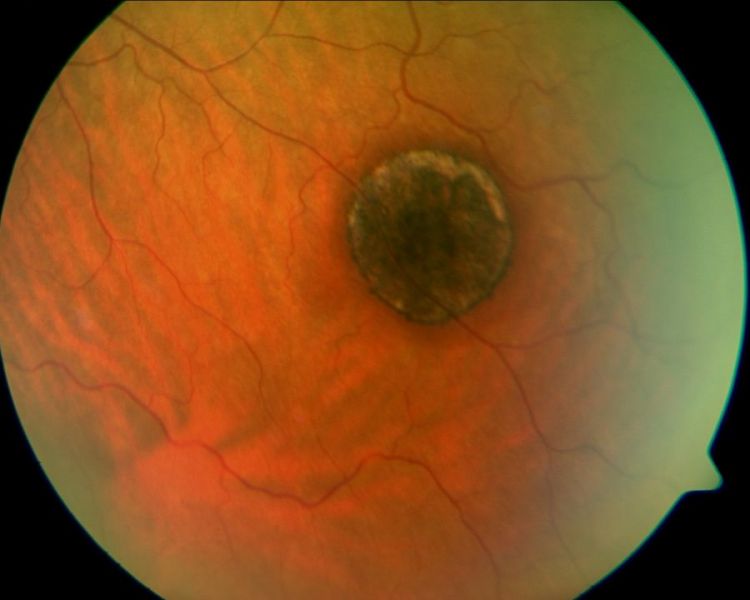
RPE hyperplasia is a reactive proliferation of retinal pigment epithelium cells after injury to the outer retina or choroid.
It appears as jet black, irregular pigment clumps on fundus examination. The lesion itself rarely threatens vision, because it marks a healed process. However, it records past disease and can mimic congenital or malignant pigmented lesions.
What RPE Hyperplasia Is
Normal RPE forms a single layer of cells between the photoreceptors and Bruch membrane, but after damage, surviving cells divide, pile up and migrate into the retina. As a result, pigment collects in multilayered clumps that look darker than the surrounding fundus.
Loss of contact with the photoreceptors appears to trigger this response, while inflammation amplifies it, and the same cellular behavior also contributes to proliferative vitreoretinopathy.
Common Causes of RPE Hyperplasia
- Blunt or penetrating trauma, including choroidal rupture
- Chronic or previously repaired retinal detachment
- Laser photocoagulation and cryotherapy scars
- Healed chorioretinitis, for example toxoplasmosis
- Inherited dystrophies, such as retinitis pigmentosa
- Long-standing choroidal lesions with overlying RPE changes
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteDemarcation Lines After Old Detachment
A chronic detachment often leaves a pigmented line at its posterior border, and this demarcation line forms when detached and attached retina meet for months. Therefore, it signals chronicity and a slowly progressive or stable detachment, while several parallel lines suggest that the detachment advanced in stages.
RPE Hyperplasia After Trauma and Laser
Blunt trauma can leave patchy pigment clumps in the periphery or near a choroidal rupture, while laser burns typically mature into round scars with a pigmented rim and atrophic center. Cryotherapy scars also become pigmented over several weeks, and the history usually matches the scar pattern.
Inflammatory Scars
Healed toxoplasma retinochoroiditis leaves an atrophic scar edged by heavy pigment, and similarly, other forms of posterior uveitis can produce punched-out lesions with pigmented borders. Therefore, ask about prior floaters, red eye or treated infections. A fresh fluffy lesion beside an old pigmented scar suggests reactivation.
Fundus Appearance of RPE Hyperplasia
Reactive pigment usually looks jet black, flat and irregular in shape, and it sits at the RPE level or within the retina, and vessels may pass over it. Surrounding atrophy, scarring or a demarcation line supports a reactive origin, although occasionally nodular hyperplasia forms a small elevated mass that needs closer study.
OCT Findings in RPE Hyperplasia
Optical coherence tomography shows hyperreflective thickening at the RPE level, and dense pigment then casts a shadow over the underlying choroid. Intraretinal hyperreflective foci may represent migrating RPE cells, and on autofluorescence, dense clumps usually appear hypoautofluorescent. Also, a normal choroidal contour beneath the pigment argues against a choroidal mass.
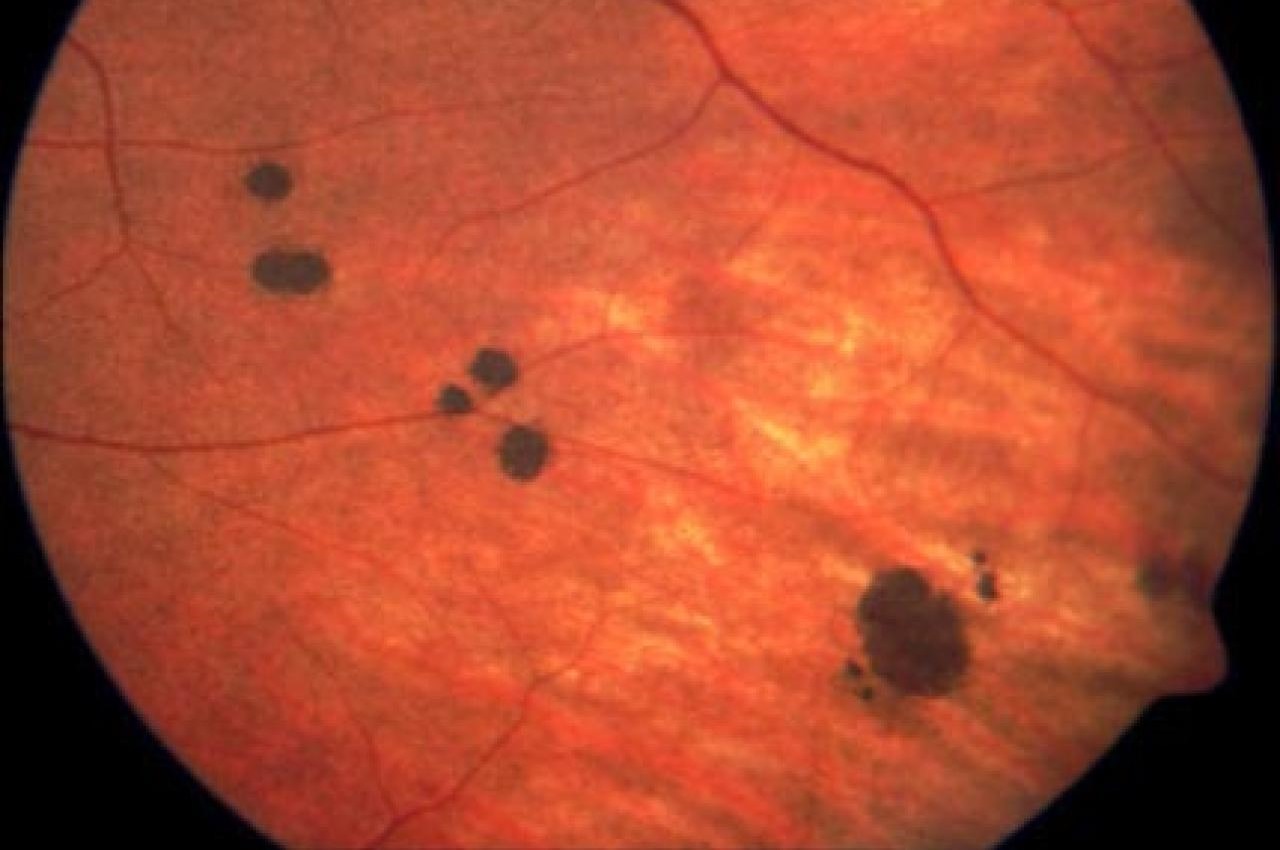
RPE Hyperplasia Versus CHRPE
CHRPE is a congenital, flat, sharply demarcated lesion with a round or oval shape (see CHRPE features), and it often has a depigmented halo and internal lacunae. By contrast, RPE hyperplasia has irregular borders and lies within a scar or atrophic zone, while CHRPE usually occurs without prior trauma, inflammation or detachment.
RPE Hyperplasia Versus Choroidal Nevus
A choroidal nevus sits deeper and looks slate gray with less distinct margins, and it often carries overlying drusen and may show subtle choroidal elevation on OCT. On the other hand, reactive hyperplasia appears blacker and lies at the RPE level. Next, compare any pigmented lesion with prior photographs when they exist.
RPE Hyperplasia Versus Melanoma
Melanoma is a choroidal tumor that usually becomes elevated and dome shaped, and warning features include thickness over 2 mm, subretinal fluid, symptoms and orange pigment (see orange pigment). Furthermore, the TFSOM mnemonic helps grade risk in small lesions (see TFSOM risk factors). Reactive pigment, however, lacks these features and stays flat in most patients.
Ultrasound for Nodular Lesions
Elevated pigmented lesions need B-scan and A-scan ultrasonography, where melanoma typically shows low to medium internal reflectivity and acoustic hollowness. Nodular RPE hyperplasia and RPE adenoma usually arise abruptly from the RPE. Therefore, refer any growing or elevated lesion to an ocular oncologist.
Managing RPE Hyperplasia
Isolated reactive pigment needs no direct treatment, and management instead targets the cause, such as an active detachment or uveitis. First, document the lesion with wide-field color photographs and OCT, then repeat imaging at follow-up when the diagnosis remains uncertain. Stability over time supports a benign reactive process.
Counseling the Patient
Explain that the pigment is a scar marking an old injury or inflammation. Most patients feel reassured once they understand it does not behave like a tumor. However, advise prompt review for new floaters, flashes, a shadow or blurred vision, since these may signal a new problem.
Pitfalls to Avoid
- Avoid labeling every black spot as reactive without imaging
- Do not miss an active detachment behind an old demarcation line
- Separate vitreous pigment cells (Shafer sign) from fundus pigment
- Never dismiss elevation, fluid or orange pigment on a pigmented lesion


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Shields JA, Shields CL, Gündüz K, Eagle RC Jr. Neoplasms of the retinal pigment epithelium: the 1998 Albert Ruedemann, Sr, memorial lecture, part 2. Arch Ophthalmol. 1999;117:601-608.
- Shields CL, Mashayekhi A, Ho T, Cater J, Shields JA. Solitary congenital hypertrophy of the retinal pigment epithelium: clinical features and frequency of enlargement in 330 patients. Ophthalmology. 2003;110:1968-1976.
- Shields CL, Dalvin LA, Ancona-Lezama D, et al. Choroidal nevus imaging features in 3,806 cases and risk factors for transformation into melanoma in 2,355 cases: the 2020 Taylor R. Smith and Victor T. Curtin Lecture. Retina. 2019;39:1840-1851.
- Bowling B. Kanski’s Clinical Ophthalmology: A Systematic Approach. 8th ed. Elsevier; 2016.
Test yourself
A few questions straight from this article.
-
What is RPE hyperplasia?
RPE hyperplasia is a reactive proliferation of RPE cells after injury; surviving cells divide, pile up and migrate into the retina, forming dark multilayered clumps. -
What appears to trigger the reactive proliferation seen in RPE hyperplasia?
Loss of contact with the photoreceptors appears to trigger the response, while inflammation amplifies it. -
After a chronic retinal detachment, what do several parallel pigmented demarcation lines suggest?
A demarcation line forms where detached and attached retina meet for months and signals chronicity; several parallel lines suggest the detachment advanced in stages. -
How does reactive RPE hyperplasia typically appear on fundus examination?
Reactive pigment usually looks jet black, flat and irregular, sits at the RPE level or within the retina, and is often surrounded by atrophy or scarring. -
On fundus autofluorescence, how do dense clumps of RPE hyperplasia usually appear?
Dense clumps usually appear hypoautofluorescent, and on OCT they show hyperreflective RPE-level thickening that shadows the underlying choroid. -
Which feature favors CHRPE over reactive RPE hyperplasia?
CHRPE is congenital, flat, sharply demarcated and round or oval, often with a depigmented halo and lacunae, while RPE hyperplasia has irregular borders within a scar. -
How does a choroidal nevus differ in appearance from reactive RPE hyperplasia?
A choroidal nevus sits deeper, looks slate gray with less distinct margins and often carries drusen, whereas reactive hyperplasia is blacker and lies at the RPE level. -
Which finding on a pigmented fundus lesion is a melanoma warning feature rather than a sign of RPE hyperplasia?
Melanoma warning features include thickness over 2 mm, subretinal fluid, symptoms and orange pigment, whereas reactive pigment stays flat in most patients. -
How is isolated reactive RPE hyperplasia managed?
Isolated reactive pigment needs no direct treatment; management targets the cause, with photographs and OCT, and stability over time supports a benign process. -
Which inherited disorder is a recognized cause of RPE hyperplasia?
Causes include trauma, chronic detachment, laser and cryotherapy scars, healed chorioretinitis and inherited dystrophies such as retinitis pigmentosa.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.