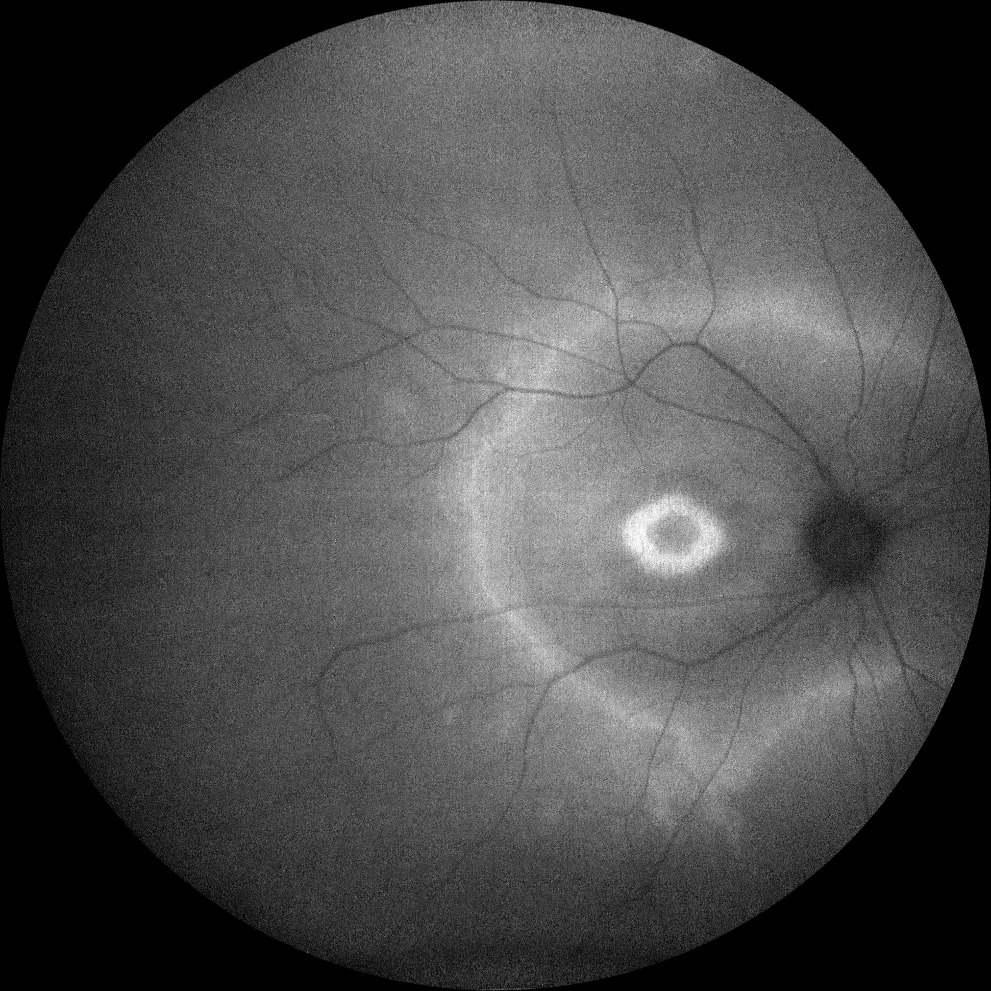
Hyperautofluorescent ring imaging shows a parafoveal band of bright signal in many eyes with retinitis pigmentosa (RP).
It marks the boundary between functioning central retina and degenerated periphery, so it gives clinicians a simple map of surviving photoreceptors.
What the Hyperautofluorescent Ring Looks Like
On blue-light FAF, the ring appears as a bright oval centered on the fovea, and its size varies widely, from a small perifoveal circle to a band near the arcades. Inside the ring, autofluorescence usually looks normal, but outside it the signal often looks mottled, while dark patches mark atrophy.
Who Shows It
The ring appears in many patients with autosomal dominant, recessive and X-linked RP, and clinicians also find it in Usher syndrome. However, not every RP eye has a ring, and advanced atrophy can erase it.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteWhy the Ring Forms
The exact mechanism remains uncertain, but one theory proposes lipofuscin buildup in the retinal pigment epithelium (RPE) at the edge of degenerating rods. Stressed photoreceptors may shed more outer segment material, which the RPE must then digest, and thinning of the outer retina may also unmask the RPE signal.
Hyperautofluorescent Ring and the Ellipsoid Zone
Spectral-domain OCT shows the clearest structural correlate, because the ellipsoid zone usually fades within the ring itself (see ellipsoid zone disruption). Meanwhile, the external limiting membrane often extends a little farther toward the outer border. Inside the ring, outer retinal lamination looks largely intact, and therefore the ring and the EZ edge describe the same transition from two angles.
Function Inside and Outside the Ring
Robson and colleagues linked ring size to pattern ERG responses in RP patients with normal acuity, and later microperimetry work showed relatively preserved sensitivity inside the ring. In contrast, sensitivity falls across the ring and beyond it. As a result, many patients keep good acuity despite tunnel vision.
Tracking Progression With the Hyperautofluorescent Ring
In many patients, the ring constricts slowly over years, and its shrinkage tends to parallel narrowing of the EZ width on OCT. Measure ring diameters or area on images with identical field and scale, and also compare eyes, because RP progression is usually symmetric.
When the Ring Reaches the Fovea
Eventually the ring may close in and break up near the center, and central acuity often declines at this stage. However, check OCT for cystoid macular edema or an epiretinal membrane before blaming progression, because both are treatable causes of central blur in RP.
Imaging Technique for the Hyperautofluorescent Ring
Confocal scanning laser ophthalmoscopes with 488 nm excitation give consistent images, so average several frames to reduce noise, then keep detector sensitivity and focus constant between visits. Ultra-widefield green-light FAF also captures the peripheral pattern, however, ring borders can differ between devices, so follow each patient on one platform.
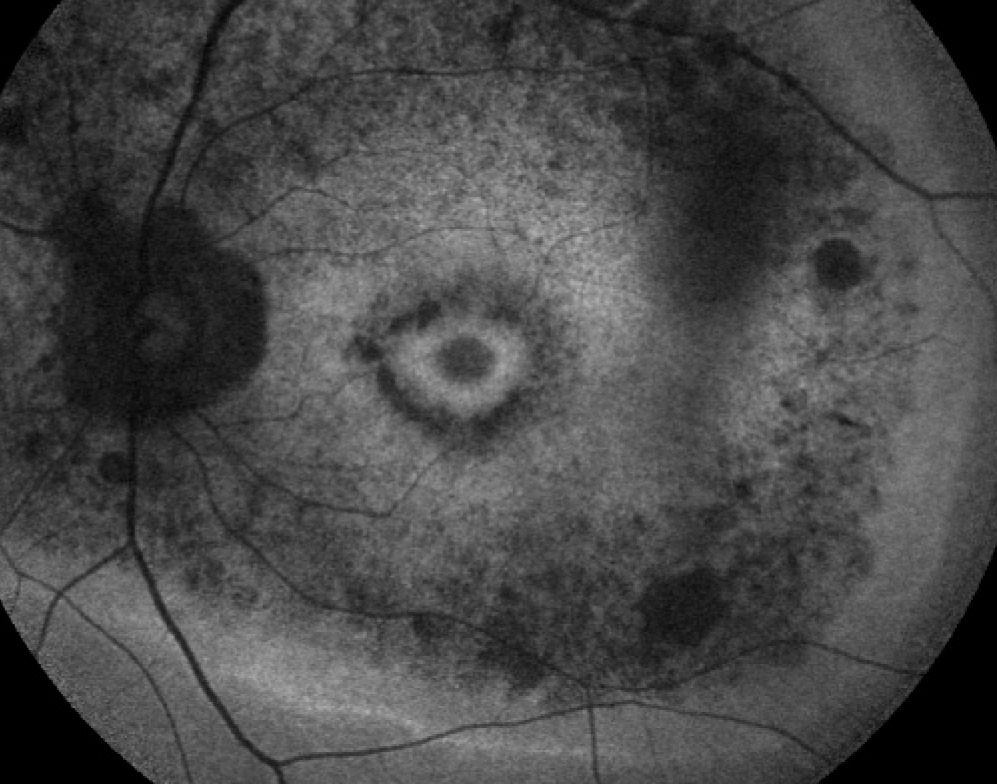
Hyperautofluorescent Ring in Cone-Rod Dystrophy
Rings also occur in cone and cone-rod dystrophies, where the bright annulus often surrounds a central zone of low signal. In many of these patients the ring expands over time, so read the direction of change alongside the phenotype and ERG.
Other Conditions With a Hyperautofluorescent Ring
- Hydroxychloroquine retinopathy with parafoveal or pericentral hyperautofluorescence
- Enhanced S-cone syndrome, often with a ring near the arcades
- Some forms of Leber congenital amaurosis
- Acute zonal occult outer retinopathy, with a bright lesion border (see AZOOR)
Differential Diagnosis
A ring in an adult with no family history needs a broader workup, so first ask about hydroxychloroquine use and recent onset of symptoms. Then consider autoimmune retinopathy and other causes of nyctalopia (see night vision loss), and full-field ERG and genetic testing usually settle the diagnosis.
Counseling Patients About the Hyperautofluorescent Ring
Patients often see the bright ring and assume it shows active damage, so explain that it marks the edge of their working retina. A stable ring supports reassurance, while a shrinking ring helps explain new field complaints. Avoid promising timelines, because rates vary between genes and individuals.
Role in Clinical Trials
RP trials need structural endpoints that change within a few years, and EZ width on OCT is a widely used measure. Ring area on FAF offers a complementary structural marker, but most trial designs pair structure with visual function.
Limits of the Hyperautofluorescent Ring
The ring describes the central retina only, so it does not measure the peripheral field that RP patients lose first. In addition, cataract and poor fixation degrade image quality, and ring borders also blur in late disease, which makes measurements less reliable.
Pitfalls to Avoid
- Do not compare images from different devices, because borders shift
- Never assume an absent ring excludes RP
- Do not ignore cystoid macular edema when acuity drops
- Avoid reading ring expansion in cone dystrophy as improvement
- Also check medication history before labeling a ring as inherited disease


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Robson AG, El-Amir A, Bailey C, et al. Pattern ERG correlates of abnormal fundus autofluorescence in patients with retinitis pigmentosa and normal visual acuity. Invest Ophthalmol Vis Sci. 2003;44:3544-3550.
- Robson AG, Michaelides M, Saihan Z, et al. Functional characteristics of patients with retinal dystrophy that manifest abnormal parafoveal annuli of high density fundus autofluorescence; a review and update. Doc Ophthalmol. 2008;116:79-89.
- Lima LH, Cella W, Greenstein VC, et al. Structural assessment of hyperautofluorescent ring in patients with retinitis pigmentosa. Retina. 2009;29:1025-1031.
- Schmitz-Valckenberg S, Holz FG, Bird AC, Spaide RF. Fundus autofluorescence imaging: review and perspectives. Retina. 2008;28:385-409.
- Hartong DT, Berson EL, Dryja TP. Retinitis pigmentosa. Lancet. 2006;368:1795-1809.
Test yourself
A few questions straight from this article.
-
In retinitis pigmentosa, what boundary does the hyperautofluorescent FAF ring mark?
The ring marks the boundary between functioning central retina and degenerated periphery, giving a simple map of surviving photoreceptors. -
Which theory has been proposed for the hyperautofluorescent ring in retinitis pigmentosa?
The mechanism is uncertain, but one theory proposes lipofuscin buildup in the RPE at the edge of degenerating rods, as stressed photoreceptors shed more outer segment material. -
On spectral-domain OCT in retinitis pigmentosa, where does the ellipsoid zone usually fade relative to the FAF ring?
The ellipsoid zone usually fades within the ring itself, so the ring and the EZ edge describe the same transition from two angles. -
Why do many retinitis pigmentosa patients with a hyperautofluorescent ring keep good acuity despite tunnel vision?
Microperimetry shows relatively preserved sensitivity inside the ring, while sensitivity falls across and beyond it, so many patients keep good acuity despite tunnel vision. -
How does the hyperautofluorescent ring typically change over years in retinitis pigmentosa?
In many patients the ring constricts slowly over years, and its shrinkage tends to parallel narrowing of the EZ width on OCT. -
Central acuity drops in a retinitis pigmentosa patient whose FAF ring nears the fovea. What should be checked before blaming progression?
Check OCT for cystoid macular edema or an epiretinal membrane before blaming progression, because both are treatable causes of central blur in RP. -
Why should a patient's hyperautofluorescent ring be followed on a single imaging platform?
Ring borders can differ between devices, so each patient should be followed on one platform with constant detector sensitivity, focus, field and scale. -
How does the hyperautofluorescent ring often behave over time in cone-rod dystrophy?
In cone and cone-rod dystrophies the ring often surrounds central low signal and expands over time, so expansion should not be read as improvement. -
An adult with no family history shows a hyperautofluorescent ring. What should be asked first?
A ring in an adult without family history needs a broader workup, starting with hydroxychloroquine use and recent onset, then autoimmune retinopathy and other causes of nyctalopia. -
What is a key limitation of the hyperautofluorescent ring as a measure of retinitis pigmentosa?
The ring describes the central retina only, so it does not measure the peripheral field that RP patients lose first; cataract and poor fixation also degrade images.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.