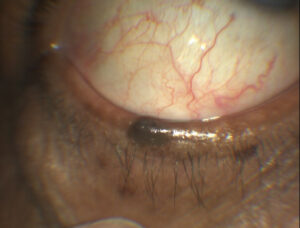
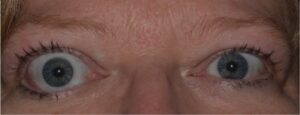
Merkel cell carcinoma (MCC) is a rare and aggressive neuroendocrine tumor of the skin, and when it arises on the eyelid it is easily mistaken for a benign lesion.
It occurs mainly in older, fair-skinned patients and in the immunosuppressed, and it grows quickly and spreads early to regional lymph nodes.
The eyelid specialist’s job is to suspect it, to biopsy it, and to refer promptly.
What Is Merkel Cell Carcinoma?
MCC arises from cells with neuroendocrine features in the skin, and most cases are linked to Merkel cell polyomavirus or to ultraviolet damage.
The virus is found integrated in the tumor DNA in a majority of cases, and the remaining cases are associated with heavy sun exposure and mutations.
Risk factors include age over 50, fair skin, chronic ultraviolet exposure, organ transplantation, HIV infection, and chronic lymphocytic leukemia.
The head and neck are the commonest sites, and the eyelid is an uncommon location, with a predilection for the upper lid.
Clinical Features
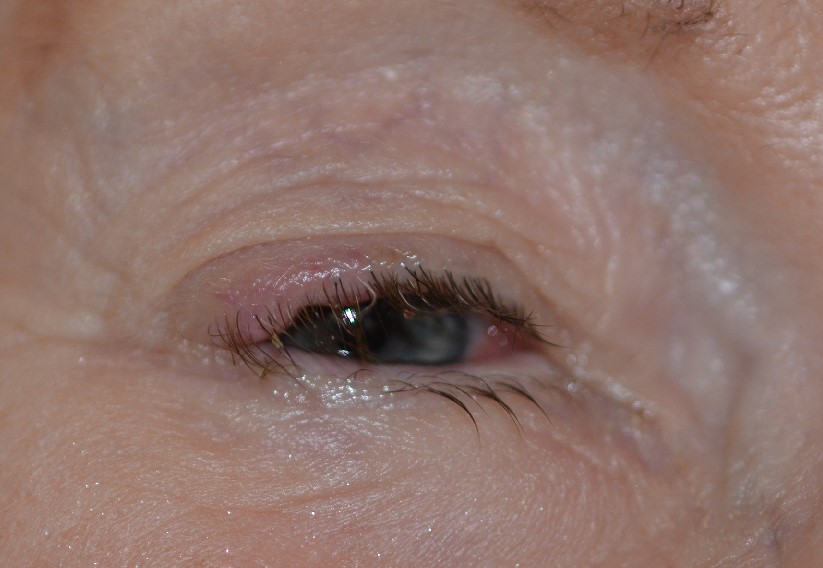
- A solitary, firm, painless, dome-shaped nodule, pink, red, or violaceous in color
- Rapid growth over weeks to a few months, often with an intact, shiny surface
- Absence of ulceration in the early stage, and sometimes telangiectasia on the surface
- Possible enlargement of the preauricular or submandibular lymph nodes at presentation
The mnemonic AEIOU summarizes the features: asymptomatic, expanding rapidly, immune suppression, older than 50, and ultraviolet-exposed site.
A rapidly growing lesion on the eyelid of an older patient, in a place where a chalazion does not usually occur, should be treated as suspicious.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteDifferential Diagnosis
- Chalazion: an inflammatory lesion within the tarsus, which may be tender and may resolve (see chalazion)
- Sebaceous carcinoma: a yellowish nodule or a diffuse thickening with loss of lashes (see sebaceous carcinoma)
- Basal cell carcinoma: a pearly nodule with telangiectasia and rolled borders (see basal cell carcinoma of the eyelid)
- Hemangioma, cyst, and pyogenic granuloma: benign vascular or cystic lesions
- Lymphoma and metastasis: other violaceous nodules
Diagnosis
Biopsy is essential, and an excisional or incisional biopsy provides a sample for histology and immunostaining.
The tumor is made of small round blue cells with scant cytoplasm and a high mitotic rate.
Immunohistochemistry shows cytokeratin 20 in a perinuclear dot pattern, with positive neuroendocrine markers such as chromogranin and synaptophysin, and negative thyroid transcription factor 1, which separates it from metastatic small cell lung carcinoma.
After the diagnosis, stage the disease with imaging, such as CT or PET-CT, and with sentinel lymph node biopsy where appropriate.
Treatment
Wide local excision with clear margins is the basis of treatment, and Mohs surgery or frozen-section margin control can preserve tissue on the eyelid.
Adjuvant radiotherapy to the primary site and to the regional nodes lowers the risk of local recurrence and is commonly used.
Immunotherapy with PD-1 or PD-L1 inhibitors, such as avelumab or pembrolizumab, has improved outcomes in advanced and metastatic disease.
Patients are followed closely, with examination of the nodes and imaging, since most recurrences appear in the first two or three years.
Coordination among the oculoplastic surgeon, dermatologist, oncologist, and radiation oncologist is needed.
Prognosis and Why Early Referral Matters
MCC has a high rate of local recurrence and regional spread, and a notable share of patients have nodal disease when they are first seen.
The prognosis depends on the stage at diagnosis, with small, localized tumors having a much better outcome than those with nodal or distant metastasis.
Because the lesion grows quickly, a delay of weeks can change the stage, so a suspicious eyelid nodule should be biopsied without waiting for a trial of drops or warm compresses.
Practical Tips for the Clinic
- Photograph any rapidly changing eyelid lesion and measure it, so that growth can be proved
- Palpate the preauricular and submandibular nodes at the first visit
- Alert the pathologist to the clinical suspicion, so that immunostains are ordered
- Avoid curettage of a lesion that might be a carcinoma, because it can complicate margin assessment
- Ask about immunosuppression, transplantation, and previous skin cancers
Follow-Up and Counselling
Patients need regular examination of the primary site and the nodes, together with imaging as directed by the oncology team.
Immunosuppressed patients should have their immunosuppression reviewed with their physician when possible.
Explain that the tumor is aggressive, but that modern treatment, including immunotherapy, has improved the outlook, and that a coordinated team gives the best results.
Sun protection and regular skin checks are advised for life.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Missotten GS, de Wolff-Rouendaal D, de Keizer RJ. Merkel cell carcinoma of the eyelid: review of the literature and report of a patient with Merkel cell carcinoma showing spontaneous regression. Ophthalmology. 2008;115:195-201.
- Heath M, Jaimes N, Lemos B, et al. Clinical characteristics of Merkel cell carcinoma at diagnosis in 195 patients: the AEIOU features. J Am Acad Dermatol. 2008;58:375-381.
- Shields JA, Shields CL. Eyelid, Conjunctival, and Orbital Tumors: An Atlas and Textbook. 3rd ed. Wolters Kluwer; 2016.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 7: Oculofacial Plastic and Orbital Surgery. AAO; current edition.
Test yourself
A few questions straight from this article.
-
What kind of tumour is Merkel cell carcinoma of the eyelid?
Merkel cell carcinoma is a rare, aggressive neuroendocrine tumour of the skin that grows quickly and spreads early to regional lymph nodes. -
Which virus is implicated in most cases of Merkel cell carcinoma?
Merkel cell polyomavirus is found integrated in the tumour DNA in most cases; the remaining tumours are linked to heavy ultraviolet exposure and mutations. -
Where on the eyelid does Merkel cell carcinoma show a predilection?
The head and neck are the commonest region for Merkel cell carcinoma, and the eyelid is an uncommon site with a predilection for the upper lid. -
What is the typical appearance of eyelid Merkel cell carcinoma?
The lesion is a solitary, firm, painless, dome-shaped nodule, pink to violaceous, with an intact shiny surface and no ulceration early on, growing over weeks to a few months. -
What is the correct action for a rapidly growing violaceous eyelid nodule in an older patient?
Because the tumour grows quickly, a delay of weeks can change the stage, so a suspicious eyelid nodule is biopsied without waiting for a trial of drops or warm compresses. -
Why should curettage be avoided in a suspected eyelid carcinoma?
Curettage of a lesion that might be a carcinoma can complicate margin assessment, so a lesion suspected of malignancy is biopsied properly and the pathologist alerted. -
What does histology of Merkel cell carcinoma show?
The tumour is composed of small round blue cells with scant cytoplasm and a high mitotic rate, which is why immunostaining is needed to confirm the lineage. -
Which immunostaining pattern separates Merkel cell carcinoma from metastatic small cell lung carcinoma?
Cytokeratin 20 in a perinuclear dot pattern with positive chromogranin and synaptophysin, and negative thyroid transcription factor 1, separates it from metastatic small cell lung carcinoma. -
Which systemic therapy has improved outcomes in advanced Merkel cell carcinoma?
Immunotherapy with PD-1 or PD-L1 inhibitors such as avelumab or pembrolizumab has improved outcomes in advanced and metastatic disease, alongside excision and adjuvant radiotherapy. -
When do most recurrences of Merkel cell carcinoma appear?
Most recurrences appear within the first two or three years, so patients are followed closely with examination of the nodes and imaging as directed by the oncology team.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.