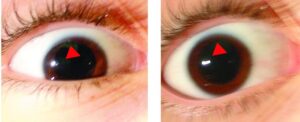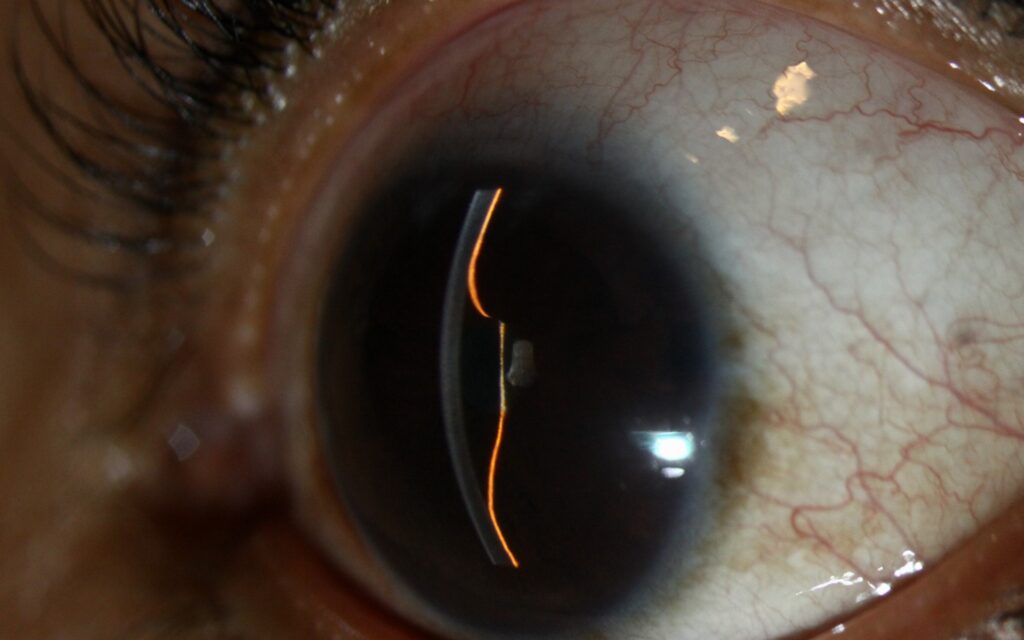
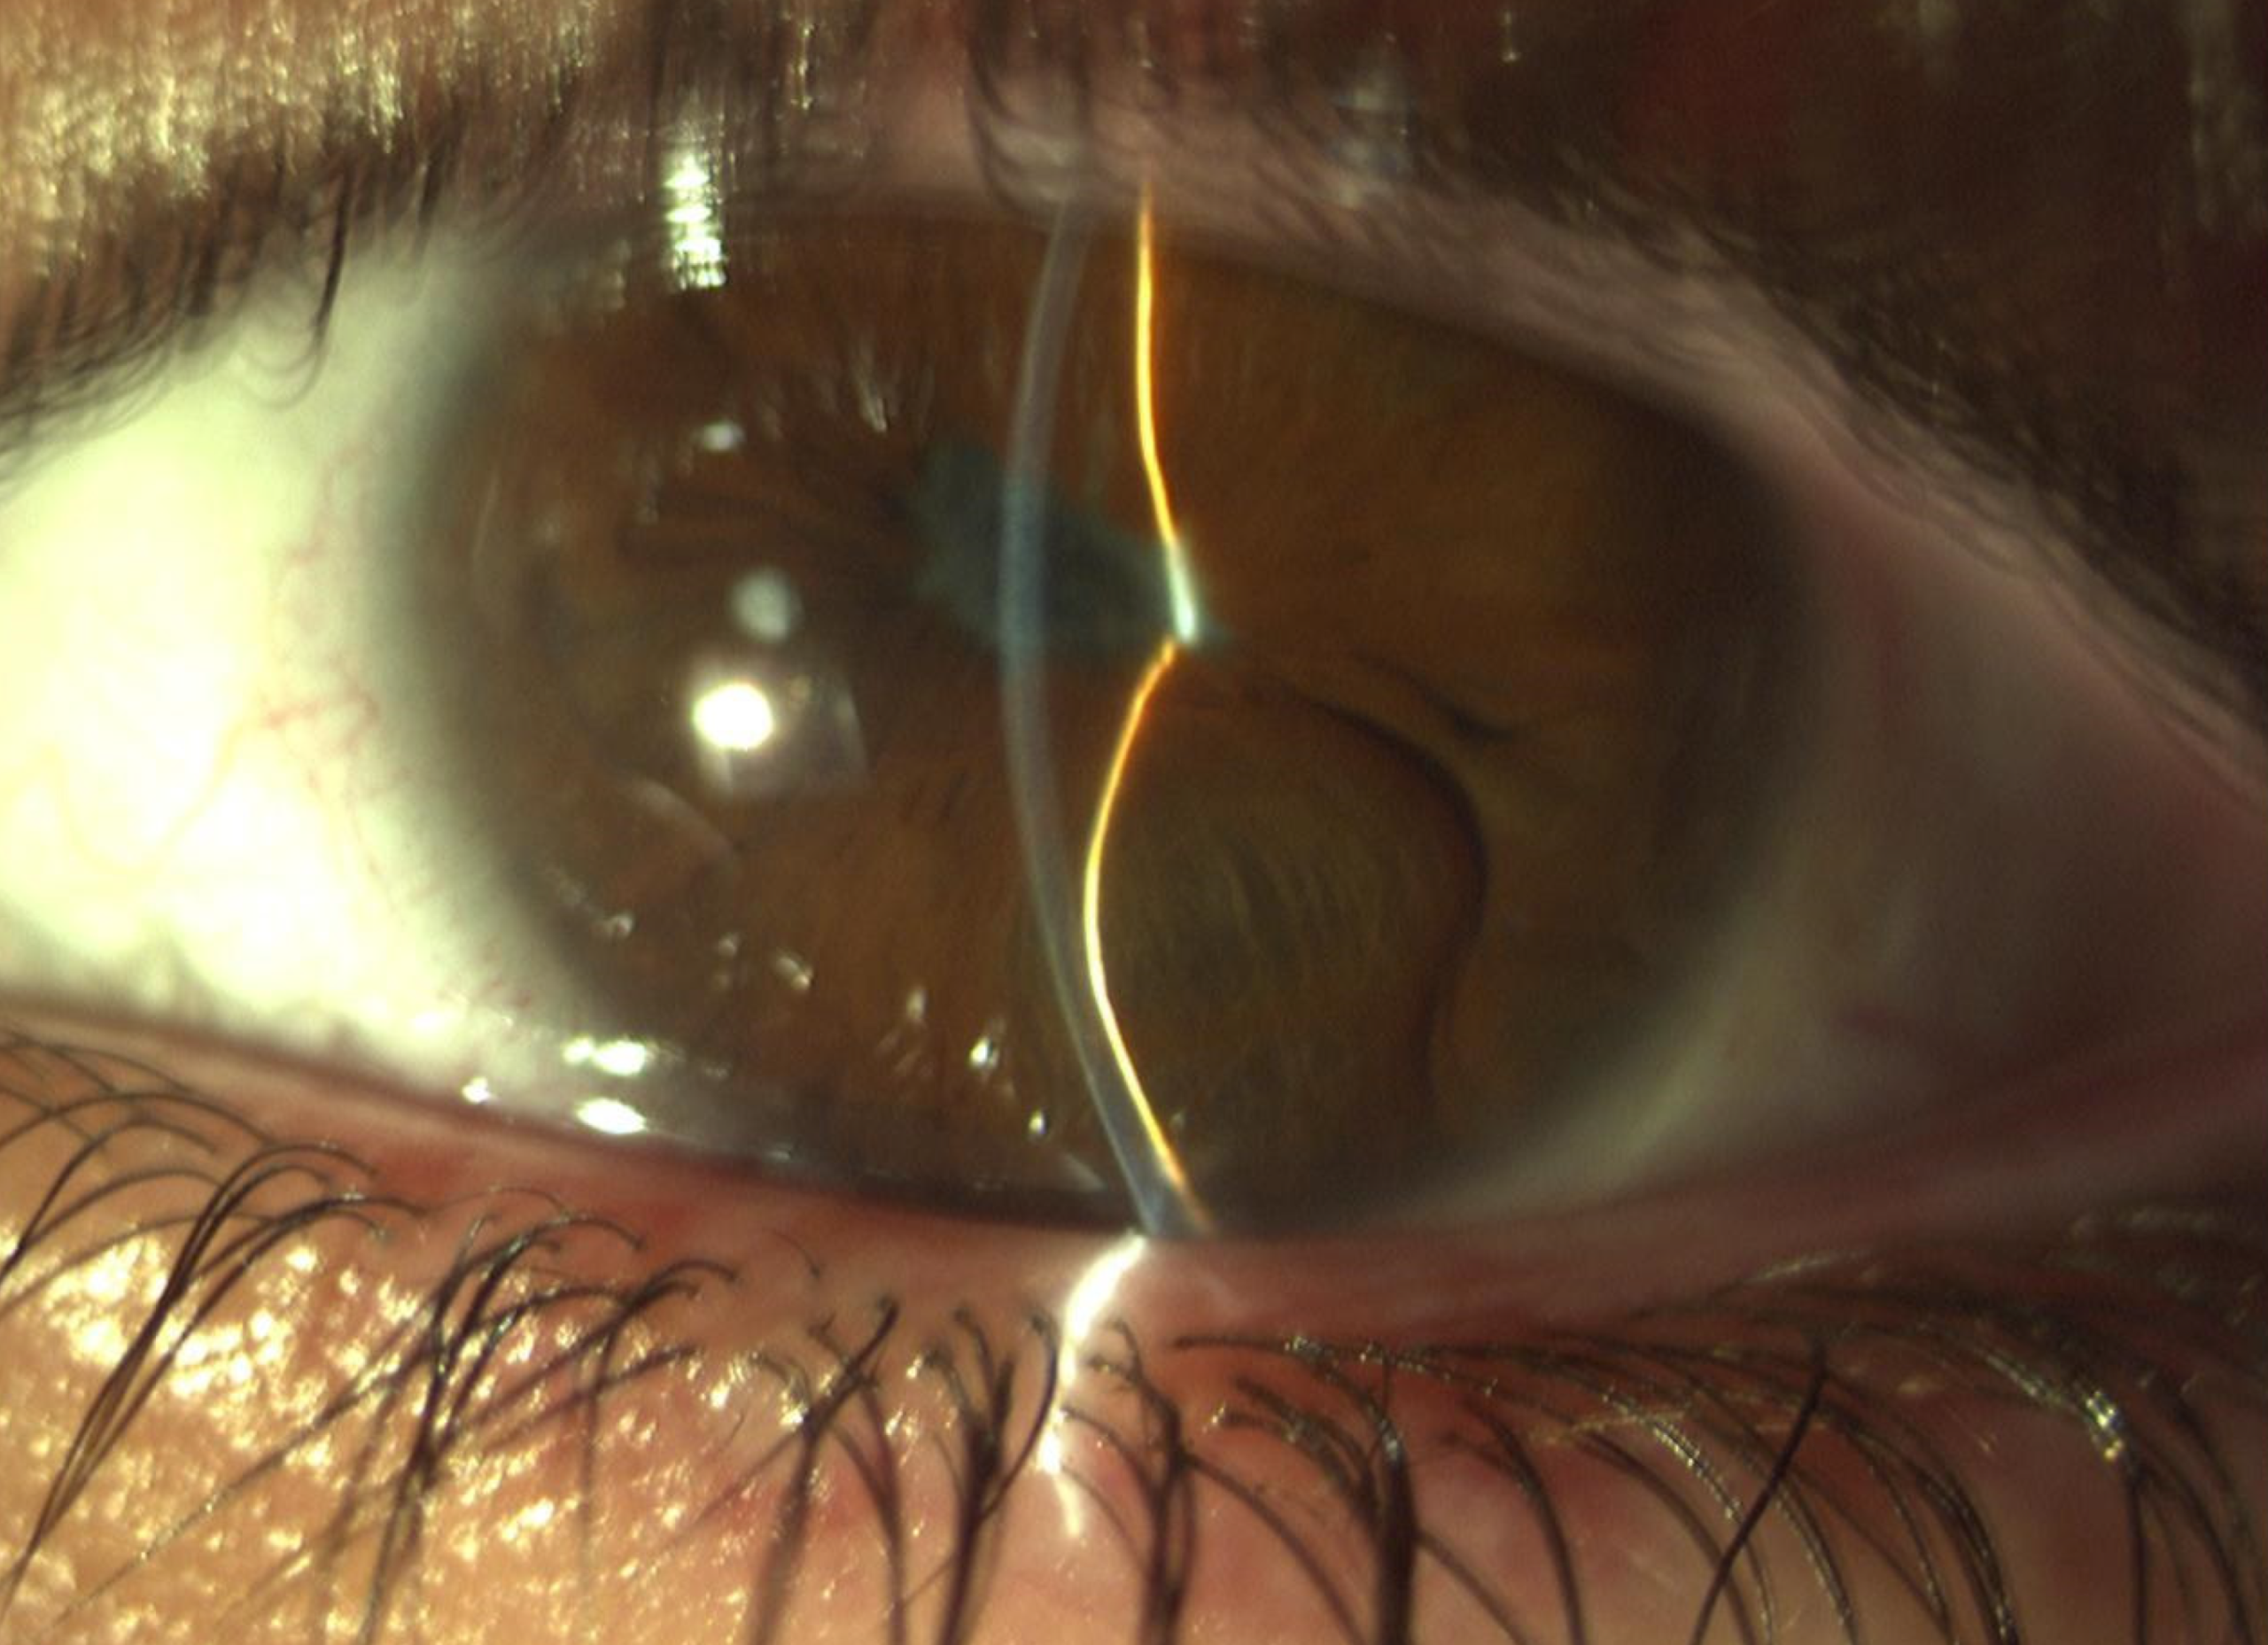
Iris bombe produces one of the more visually distinctive presentations in anterior segment examination, an entire iris bulging forward in a smooth, convex, dome-like configuration, and recognizing this specific pattern immediately tells a clinician the underlying mechanism at work: complete pupillary block from posterior synechiae, an emergency requiring prompt intervention to prevent secondary angle closure and its associated risk to the optic nerve.
How the Iris Comes to Bulge Forward
Iris bombe develops when posterior synechiae, adhesions between the iris and the underlying lens (or, less commonly, other posterior structures), form completely around the entire pupillary margin, a full 360-degree ring of adhesion that entirely blocks the normal flow of aqueous humor from the posterior chamber, where it is produced, forward through the pupil into the anterior chamber.
With this forward flow completely obstructed, aqueous humor produced by the ciliary body accumulates in the posterior chamber, building pressure that pushes the entire iris forward into the characteristic smooth, convex, “bombe” (bulging) configuration, in contrast to the flatter or only focally irregular iris contour seen with partial, incomplete synechiae.
Most Common Underlying Cause: Uveitis
Chronic or recurrent anterior uveitis is the most common setting in which extensive posterior synechiae, and ultimately complete iris bombe, develop, since ongoing intraocular inflammation promotes fibrin deposition and adhesion formation between the iris and lens, and inadequately controlled or recurrent inflammation over time allows these adhesions to progressively extend around the full pupillary circumference (see uveitic glaucoma management for the broader discussion of glaucoma mechanisms, including this one, occurring in the setting of chronic uveitis).
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteClinical Features
- A smooth, dome-shaped, forward convexity of the entire iris, visible on slit-lamp examination and often striking enough to be recognized immediately
- A markedly shallow anterior chamber, uniformly across its extent, reflecting the forward displacement of the entire iris rather than a more localized or asymmetric pattern
- Elevated intraocular pressure, related to the resulting secondary angle closure as the bulging peripheral iris crowds and can eventually appose the trabecular meshwork
- Evidence of extensive posterior synechiae on examination, with the pupil often irregular, poorly reactive, or entirely fixed given the adhesions binding it to the underlying lens
- Signs of the underlying uveitis or other causative process, including anterior chamber cell and flare, when inflammation remains active
Why This Is a Time-Sensitive Emergency
Complete pupillary block from iris bombe can rapidly progress to acute secondary angle closure, with the same urgency and threat to the optic nerve as primary acute angle closure, making prompt recognition and treatment genuinely time-sensitive rather than something to address at a routine, unhurried pace once identified.
Diagnostic Evaluation
- Slit-lamp examination identifying the characteristic forward iris convexity and shallow, uniformly affected anterior chamber
- Gonioscopy, when the view allows, to assess the degree of secondary angle closure resulting from the peripheral iris bulging
- Intraocular pressure measurement, given the risk of significant elevation from the resulting angle closure
- Assessment for the underlying cause, most often uveitis, including a history of prior episodes and examination for active inflammatory signs
Management
Urgent Laser Peripheral Iridotomy
Creating an opening through the iris with laser peripheral iridotomy provides an alternate pathway for aqueous to flow from the posterior to the anterior chamber, directly bypassing the completely blocked pupil and relieving the pressure buildup driving the iris bombe configuration, representing the definitive, urgently needed treatment for this specific mechanism of angle closure.
- In some cases, particularly with a very shallow chamber or technically difficult laser access, a surgical peripheral iridectomy may be needed instead of or in addition to laser treatment
Managing Elevated Intraocular Pressure
Initial medical pressure-lowering therapy, using aqueous suppressants, helps manage acutely elevated pressure while definitive iridotomy or iridectomy is arranged, following similar initial-stabilization principles used in primary acute angle closure.
Treating the Underlying Uveitis
Alongside relieving the mechanical pupillary block, treating the underlying active inflammation with appropriate anti-inflammatory therapy is essential, both to control the current episode and to reduce the risk of further synechiae formation and recurrent iris bombe in the future.
Preventing Recurrence
In patients with recurrent uveitis and a history of significant synechiae formation, more proactive use of cycloplegic agents during active inflammatory episodes, aimed at keeping the pupil mobile and reducing the opportunity for extensive synechiae to form in the first place, is an important preventive strategy for future episodes.
Prognosis
With prompt recognition and urgent iridotomy or iridectomy, along with adequate treatment of the underlying uveitis, iris bombe and its associated secondary angle closure can generally be effectively relieved, protecting the optic nerve from the sustained pressure elevation this mechanism would otherwise cause.
Delayed recognition or treatment risks the same optic nerve damage associated with any prolonged, uncontrolled angle closure, reinforcing why this distinctive, recognizable iris configuration should prompt urgent rather than routine evaluation and treatment.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Sng CC, Barton K. Mechanism and management of angle closure in uveitis. Curr Opin Ophthalmol. 2015;26:121-127.
- Kesav N, Palestine AG, Kahook MY, Pantcheva MB. Current management of uveitis-associated ocular hypertension and glaucoma. Surv Ophthalmol. 2020;65:397-407.
- Moorthy RS, Mermoud A, Baerveldt G, Minckler DS, Lee PP, Rao NA. Glaucoma associated with uveitis. Surv Ophthalmol. 1997;41:361-394.
- Panek WC, Holland GN, Lee DA, Christensen RE. Glaucoma in patients with uveitis. Br J Ophthalmol. 1990;74:223-227.
Test yourself
A few questions straight from this article.
-
What mechanism produces iris bombe?
Iris bombe arises when posterior synechiae between the iris and the underlying lens completely block normal aqueous flow from the posterior chamber forward through the pupil. The trapped aqueous then pushes the iris forward. -
How extensive must posterior synechiae be to cause the complete pupillary block of iris bombe?
Complete block requires a full 360-degree ring of adhesion forming around the entire pupillary margin. Anything less leaves a route for aqueous to reach the anterior chamber. -
Where does aqueous accumulate to drive the bulging iris contour in iris bombe?
With forward flow obstructed, aqueous produced by the ciliary body accumulates in the posterior chamber. The rising pressure there pushes the whole iris into its smooth convex bombe configuration. -
Which condition is the most common underlying cause of iris bombe?
Chronic or recurrent anterior uveitis is the commonest setting for extensive posterior synechiae and ultimately complete iris bombe. Inadequately controlled or recurrent inflammation lets adhesions extend around the full pupillary circumference. -
How does chronic intraocular inflammation lead to iris bombe?
Ongoing intraocular inflammation promotes fibrin deposition and adhesion formation between the iris and lens. Over repeated or poorly controlled episodes these adhesions progressively extend around the pupil. -
Which anterior chamber finding accompanies iris bombe?
The chamber is markedly shallow and uniformly so, reflecting forward displacement of the entire iris rather than a localised or asymmetric pattern. The iris itself shows a smooth, dome-shaped forward convexity. -
How does the iris contour of partial, incomplete posterior synechiae differ from iris bombe?
Partial, incomplete synechiae leave a flatter or only focally irregular iris contour. The smooth, uniformly convex dome is what marks complete pupillary block. -
Why is iris bombe treated as a time-sensitive emergency?
Complete pupillary block can progress rapidly to acute secondary angle closure, with the same urgency and threat to the optic nerve as primary acute angle closure. Delayed treatment risks the same optic nerve damage as any prolonged uncontrolled angle closure. -
What is the definitive treatment for the pupillary block of iris bombe?
An iridotomy gives aqueous an alternate route from the posterior to the anterior chamber, bypassing the blocked pupil and relieving the pressure driving the bombe. A surgical peripheral iridectomy may be needed when the chamber is very shallow or laser access is difficult. -
Which strategy helps prevent recurrent iris bombe in patients with recurrent uveitis?
More proactive use of cycloplegic agents during active inflammatory episodes keeps the pupil mobile and reduces the chance of extensive synechiae forming. Treating the underlying inflammation also lowers the risk of further synechiae and recurrence.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.