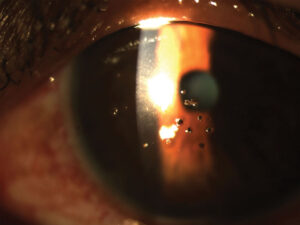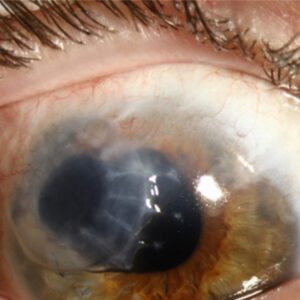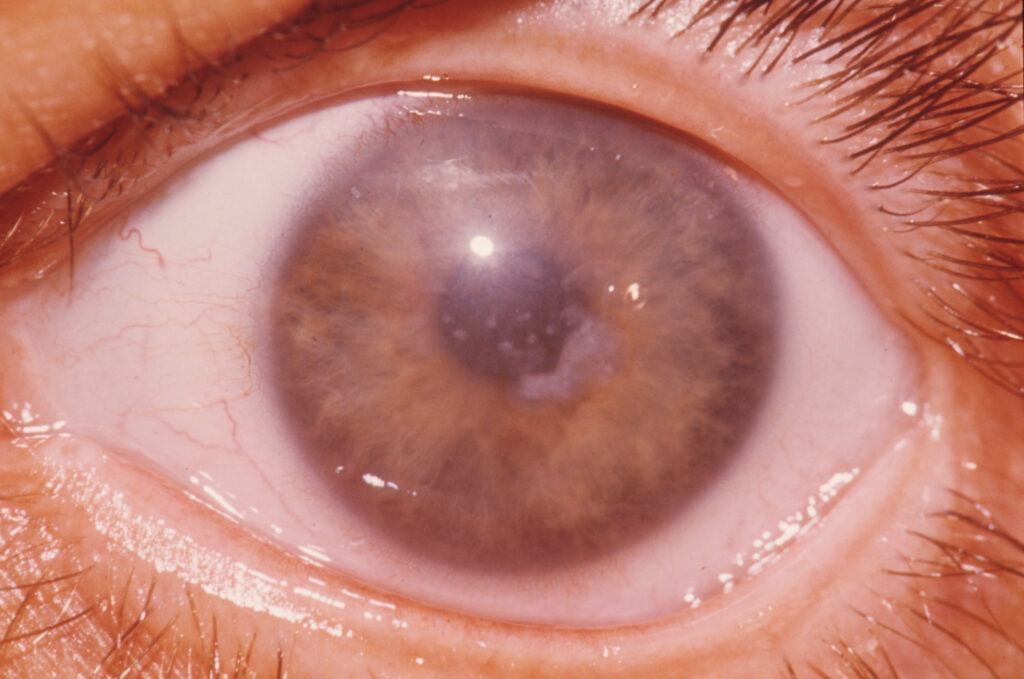
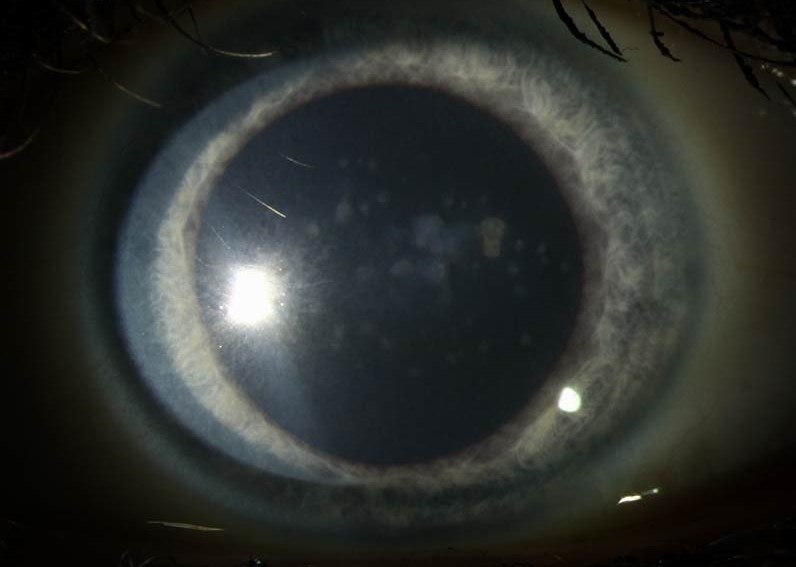
Macular corneal dystrophy stands apart from the other classic stromal dystrophies in a way that matters clinically: rather than discrete deposits in an otherwise clear cornea, it produces a diffuse, cloudy haze extending all the way to the limbus, reflecting an entirely different underlying metabolic defect and, importantly, a different inheritance pattern that carries distinct implications for genetic counseling.
A Different Metabolic Problem Entirely
Unlike lattice and granular corneal dystrophies, which result from abnormal protein (amyloid or hyaline) deposition due to TGFBI mutations, macular corneal dystrophy results from a defect in keratan sulfate metabolism, caused by mutations in the CHST6 gene, leading to accumulation of abnormal glycosaminoglycans within and between corneal stromal cells throughout the full thickness and full extent of the cornea.
This fundamentally different mechanism explains why the clinical appearance differs so much from the other stromal dystrophies: rather than localized deposits, the entire stroma is diffusely affected, producing a cloudy haze that, unlike lattice or granular dystrophy, extends edge to edge across the cornea, right up to the limbus.
Inheritance
Macular corneal dystrophy is inherited in an autosomal recessive pattern, distinguishing it from the autosomal dominant inheritance of lattice and granular dystrophies, which has real implications for genetic counseling: unaffected parents can both be carriers, and the recurrence risk calculation for future children differs accordingly.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteClinical Presentation
- Diffuse, grayish-white stromal haze affecting the full thickness of the cornea and extending to the limbus, without the clear intervening zones seen in granular dystrophy
- Onset is typically earlier and progression more rapid than granular or lattice dystrophy, often becoming visually significant already in the first or second decade of life
- Reduced corneal sensation has been reported in some patients, an additional distinguishing clinical feature
- The cornea may also be thinner than average, in contrast to some other stromal dystrophies
- Progressive visual loss tends to occur earlier and more severely than in the other classic stromal dystrophies, given the diffuse, full-thickness nature of the involvement
Diagnosis
Diagnosis is suggested by the characteristic diffuse, limbus-to-limbus stromal haze on slit-lamp examination, particularly when onset and progression are earlier than would be typical for granular or lattice dystrophy, and confirmed with genetic testing for CHST6 mutations when needed.
Distinguishing macular from the other classic stromal dystrophies on clinical grounds alone is usually straightforward given the distinctly diffuse pattern, though genetic testing supports definitive diagnosis and informs family counseling given the different inheritance pattern.
Management
Phototherapeutic Keratectomy
Given the diffuse, full-thickness nature of the stromal involvement, phototherapeutic keratectomy is generally less effective for macular corneal dystrophy than for the more superficial deposits sometimes seen in granular dystrophy, since ablating only the anterior stroma does not address the deeper, diffusely affected tissue.
Corneal Transplantation
Corneal transplantation, most often penetrating keratoplasty given the full-thickness nature of the disease, is more frequently needed, and needed earlier, in macular corneal dystrophy compared with the other classic stromal dystrophies, reflecting the more aggressive visual impact of this diffuse pattern.
Recurrence After Transplantation
As with the other stromal dystrophies, recurrence of macular dystrophy changes in the donor graft over time is a recognized long-term possibility, related to the same underlying keratan sulfate metabolic defect present throughout the patient’s own corneal tissue and cellular metabolism.
Prognosis
Macular corneal dystrophy tends to have a less favorable natural history than granular or lattice dystrophy, given its earlier onset, more diffuse involvement, and generally faster visual decline, making corneal transplantation a more frequently and more often earlier-needed intervention.
With appropriate transplantation when needed, visual outcomes are generally good, though ongoing surveillance for graft recurrence over the long term remains part of comprehensive care, as with the other genetically driven stromal corneal dystrophies.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Weiss JS, Moller HU, Aldave AJ, et al. IC3D classification of corneal dystrophies–edition 2. Cornea. 2015;34:117-159.
- Klintworth GK. Corneal dystrophies. Orphanet J Rare Dis. 2009;4:7.
- Akama TO, Nishida K, Nakayama J, et al. Macular corneal dystrophy type I and type II are caused by distinct mutations in a new sulphotransferase gene. Nat Genet. 2000;26:237-241.
- Al-Swailem SA, Al-Rajhi AA, Wagoner MD. Penetrating keratoplasty for macular corneal dystrophy. Ophthalmology. 2005;112:220-224.
Test yourself
A few questions straight from this article.
-
Which corneal appearance characterizes macular corneal dystrophy?
Macular corneal dystrophy produces a diffuse grayish-white stromal haze affecting the full corneal thickness and reaching the limbus, without the clear intervening zones of granular dystrophy. -
What metabolic defect underlies macular corneal dystrophy?
The disease results from a defect in keratan sulfate metabolism, causing abnormal glycosaminoglycans to accumulate within and between corneal stromal cells throughout the cornea. -
Mutations in which gene cause macular corneal dystrophy?
Macular corneal dystrophy is caused by CHST6 mutations, in contrast to the TGFBI mutations responsible for lattice and granular dystrophies. -
How is macular corneal dystrophy inherited?
Inheritance is autosomal recessive, unlike the autosomal dominant lattice and granular dystrophies, so unaffected parents can both be carriers and recurrence risk is calculated differently. -
When does macular corneal dystrophy typically become visually significant?
Onset is earlier and progression faster than in granular or lattice dystrophy, often becoming visually significant already in the first or second decade of life. -
Which additional clinical feature has been reported in macular corneal dystrophy?
Reduced corneal sensation has been reported in some patients with macular corneal dystrophy and serves as an additional distinguishing clinical feature. -
How does corneal thickness typically behave in macular corneal dystrophy?
The cornea in macular corneal dystrophy may be thinner than average, in contrast to some other stromal dystrophies. -
Why is phototherapeutic keratectomy of limited value in macular corneal dystrophy?
Because involvement is diffuse and full-thickness, ablating only the anterior stroma does not address the deeper affected tissue, making the procedure less effective than in granular dystrophy. -
Which transplantation is most often used for macular corneal dystrophy?
Penetrating keratoplasty is most often chosen because the disease involves the full corneal thickness, and transplantation is needed more frequently and earlier than in the other classic stromal dystrophies. -
What does long-term care include after keratoplasty for macular corneal dystrophy?
Visual outcomes after transplantation are generally good, but recurrence in the donor graft remains a recognized long-term possibility, so ongoing surveillance is part of comprehensive care.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.