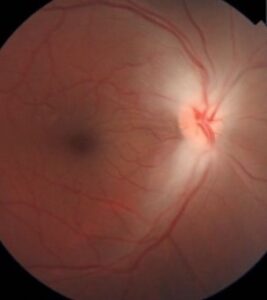
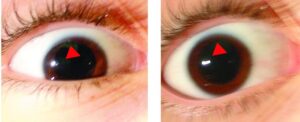
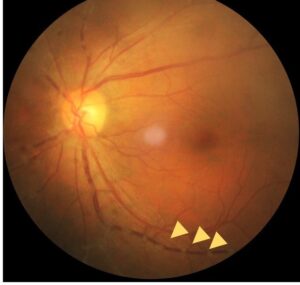
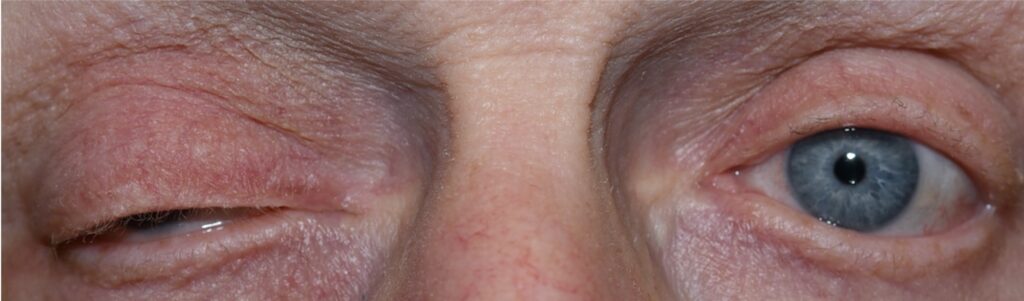
Third (oculomotor) nerve palsy produces one of the most recognizable, most anxiety-provoking, combinations of findings in neuro-ophthalmology: ptosis, an eye deviated “down and out,” and, in a subset of cases, a dilated, poorly reactive pupil.
That last finding — whether the pupil is involved or spared — is the single most important detail in the entire evaluation, because it is what separates a life-threatening compressive lesion from a benign, self-resolving microvascular event.
Why Pupil Involvement Is the Key Question
The pupillomotor fibers that constrict the pupil travel on the outer surface of the third nerve, making them especially vulnerable to compression from an external mass — most urgently, a posterior communicating artery aneurysm — which tends to affect these superficial fibers early and produce a dilated, poorly reactive pupil alongside the motility findings.
Microvascular ischemic third nerve palsy, by contrast, affects the nerve’s internal blood supply and tends to spare these superficial pupillomotor fibers.
This is why a “pupil-sparing” complete third nerve palsy in a patient with vascular risk factors is often managed with observation, while any degree of pupil involvement in a new third nerve palsy is treated as a neurosurgical emergency until proven otherwise.
Clinical Findings
- Ptosis, often complete, from levator palpebrae superioris weakness
- The eye positioned “down and out” from unopposed lateral rectus (intact, since it is innervated by the sixth nerve) and superior oblique (intact, fourth nerve) function against a weakened medial rectus, superior rectus, inferior rectus, and inferior oblique
- Diplopia, though this is not always immediately apparent if the ptosis is severe enough to cover the pupil and functionally occlude the affected eye
- A dilated, poorly reactive pupil in pupil-involved palsies
- Aberrant regeneration — abnormal, misdirected reinnervation producing findings such as lid elevation on attempted downgaze or adduction — a finding that develops over weeks to months and, when present from the very onset without any preceding acute event, actually suggests a chronic compressive lesion rather than an acute ischemic one
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteCauses
- Microvascular ischemia — diabetes and hypertension being the leading risk factors, typically pupil-sparing, and the most common cause overall in older adults with vascular risk factors
- Posterior communicating artery aneurysm — the most urgent cause to exclude, classically producing a pupil-involving palsy, often with pain
- Trauma
- Compressive lesions along the nerve’s course — tumor, or uncal herniation in the setting of raised intracranial pressure
- Cavernous sinus pathology, discussed further below, where the third nerve travels alongside other cranial nerves
- Giant cell arteritis, in the appropriate age group and clinical context
Evaluation
Any new third nerve palsy with pupil involvement, or any degree of pupil involvement in an otherwise incomplete palsy, warrants urgent neuroimaging — CT or MR angiography, or catheter angiography if the non-invasive studies are inconclusive and suspicion remains high — specifically to exclude a posterior communicating artery aneurysm.
This is because a missed aneurysm carries a risk of rupture and subarachnoid hemorrhage that can be fatal, which is why the possibility of pupil involvement is treated so seriously even before formal imaging results are available.
A pupil-sparing, complete third nerve palsy in an older patient with vascular risk factors, without pain out of proportion to what would be expected, can reasonably be observed with close follow-up, expecting spontaneous improvement over roughly three months.
This is the typical course of microvascular ischemic third nerve palsy, and reassurance about this expected recovery pattern is genuinely helpful for patients understandably alarmed by the sudden ptosis and misalignment.
Any third nerve palsy that fails to show expected improvement within this window, or that shows any atypical features (aberrant regeneration from the outset, other cranial neuropathies, systemic symptoms), should prompt reconsideration and a broader workup rather than continued observation.
Cavernous Sinus and Orbital Apex Syndromes
Because the third, fourth, and sixth cranial nerves, along with the first division of the fifth nerve, all pass through the cavernous sinus and, further forward, the orbital apex and superior orbital fissure, a lesion in this region can produce a combined multiple cranial neuropathy rather than an isolated third nerve palsy.
Recognizing when other cranial nerves are also involved — rather than assuming an isolated oculomotor palsy — points the workup toward this anatomic region specifically and broadens the differential to include cavernous sinus thrombosis, carotid-cavernous fistula, and orbital apex tumors, several of which are covered in their own dedicated articles on this site and each of which carries its own distinct urgency and treatment pathway.
Management
Management is directed entirely at the underlying cause: aneurysm clipping or endovascular coiling for a compressive aneurysm, blood sugar and blood pressure optimization alongside observation for microvascular disease, and treatment of any identified tumor or inflammatory process.
Prism correction, occlusion of one eye, or strabismus surgery are used to manage persistent diplopia once the acute phase has resolved and the deviation has stabilized, generally only after allowing adequate time for any spontaneous recovery to occur first.
The severity and pattern of any residual misalignment, including whether aberrant regeneration has occurred, shapes which of these options is most appropriate and how realistic full resolution of diplopia actually is for a given patient.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Fang C, Leavitt JA, Hodge DO, et al. Incidence and etiologies of acquired third nerve palsy using a population-based method. JAMA Ophthalmology.
- Trobe JD. Third nerve palsy and the pupil. Footnotes to the rule. Archives of Ophthalmology.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 5: Neuro-Ophthalmology.
- Bagheri N, Wajda B, eds. The Wills Eye Manual.
Test yourself
A few questions straight from this article.
-
In a complete third nerve palsy, the affected eye typically rests in which position?
Ptosis with the eye deviated down and out is the classic combination, alongside a dilated poorly reactive pupil in a subset of cases. -
Why are the pupillomotor fibres of the third nerve especially vulnerable to an external compressive mass?
The pupillomotor fibres run on the outer surface of the third nerve, so an external mass affects them early and dilates the pupil. -
A patient has a new third nerve palsy with a dilated, poorly reactive pupil. What is the priority?
Any pupil involvement in a new third nerve palsy warrants urgent CT or MR angiography to exclude a posterior communicating artery aneurysm. -
An older diabetic patient has a complete but pupil-sparing third nerve palsy without disproportionate pain. What is reasonable management?
A pupil-sparing complete palsy in an older patient with vascular risk factors can reasonably be observed, expecting spontaneous improvement. -
Which intact extraocular muscles pull the eye down and out in a third nerve palsy?
The lateral rectus (sixth nerve) and superior oblique (fourth nerve) remain intact and act unopposed against the weakened third nerve muscles. -
What is the most common cause of third nerve palsy overall in older adults with vascular risk factors?
Microvascular ischaemia, with diabetes and hypertension the leading risk factors, is the most common cause and is typically pupil-sparing. -
Over roughly what period is spontaneous improvement expected in microvascular ischaemic third nerve palsy?
Observation of a pupil-sparing palsy expects spontaneous improvement over roughly three months; failure to improve should prompt broader workup. -
Aberrant regeneration present from the very onset of a third nerve palsy suggests what?
Aberrant regeneration normally develops over weeks to months, so its presence from the outset points to a chronic compressive lesion. -
A third nerve palsy accompanied by fourth, sixth and first-division fifth nerve involvement localises to which region?
The third, fourth and sixth nerves and the first division of the fifth all pass through the cavernous sinus and orbital apex, so a lesion there combines palsies. -
When are prisms, occlusion or strabismus surgery used for diplopia following third nerve palsy?
These options are used for persistent diplopia after the acute phase resolves and the deviation stabilises, allowing time for spontaneous recovery first.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.