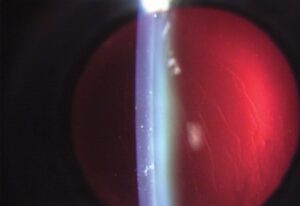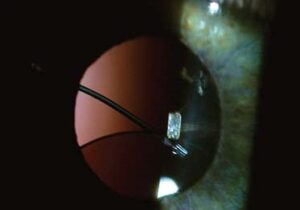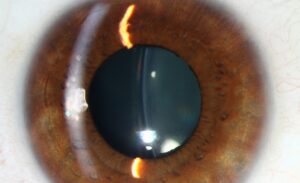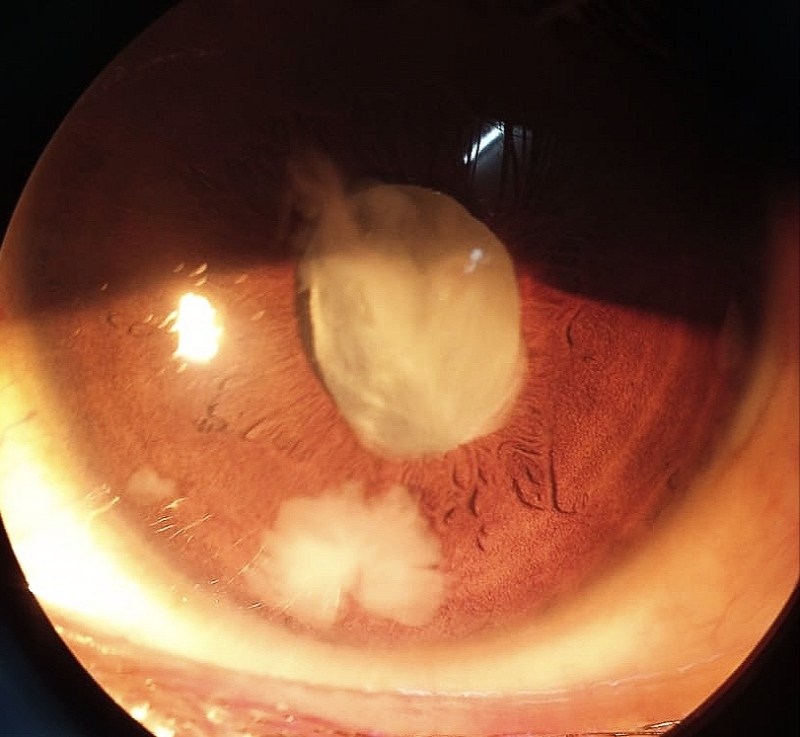
Lens-particle glaucoma is a secondary open-angle glaucoma caused by direct mechanical obstruction of the trabecular meshwork by fragments of lens cortical material released after trauma or cataract surgery.
It is distinct from phacolytic glaucoma, discussed in its own dedicated articles on this site, where the trabecular meshwork is obstructed by leaked, denatured lens proteins rather than actual particulate lens material, and where the lens capsule itself remains intact.
That distinction between intact-capsule protein leakage and an actual capsular breach releasing solid lens fragments is the key to keeping the two conditions straight.
Both conditions fall under the broader umbrella of lens-induced glaucomas, a category that also includes phacomorphic glaucoma, where the mechanism is purely mechanical crowding from an enlarging cataract rather than either particulate obstruction or protein leakage.
Mechanism
Lens-particle glaucoma requires a disrupted lens capsule, whether from penetrating trauma, blunt trauma with capsular rupture, or, most commonly in modern practice, complicated cataract surgery with retained cortical fragments.
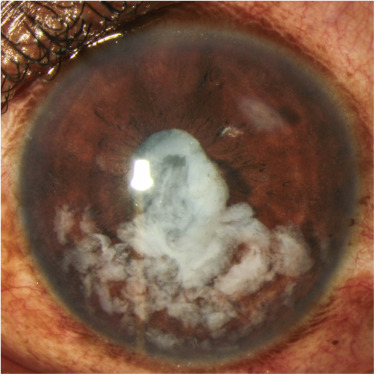
Once the capsule is breached, cortical lens material, softer and more particulate than the dense nucleus, disperses into the anterior chamber and mechanically clogs the trabecular meshwork, directly raising outflow resistance.
Unlike phacolytic glaucoma, which develops over a hypermature cataract’s slow natural course, lens-particle glaucoma typically follows a specific, identifiable inciting event, whether traumatic or surgical, and the timeline is usually much more acute.
The amount of retained material needed to cause clinically significant pressure elevation varies between eyes, and even a modest quantity of retained cortex can provoke a disproportionate pressure response in a susceptible eye.
Clinical Setting
- Retained lens cortical material after cataract surgery, particularly when capsular rupture or a difficult, prolonged case left residual fragments behind
- Penetrating ocular trauma disrupting the lens capsule directly, allowing cortical material to disperse into the anterior chamber
- Blunt trauma severe enough to rupture the capsule, sometimes with an associated traumatic cataract forming rapidly after the injury
- A delayed presentation, since retained cortical material can continue causing intermittent or progressive pressure elevation for weeks after the inciting event rather than only in the immediate aftermath
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteClinical Presentation
Patients present with pain, redness, and blurred vision, alongside elevated intraocular pressure, in a timeframe that is temporally linked to a known episode of trauma or a recent, often complicated, cataract surgery.
Visible white, flocculent cortical material is often seen floating or layering in the anterior chamber on slit-lamp exam, a finding that, when present, essentially confirms the diagnosis without much further workup needed.
Anterior chamber inflammation typically accompanies the mechanical obstruction, since retained lens material provokes a genuine inflammatory response in addition to the direct physical blockage of outflow.
Differential Diagnosis
Phacolytic glaucoma shares the general lens-related mechanism but occurs with an intact capsule and a hypermature cataract, typically in an older patient without a recent surgical or traumatic history, and does not show visible free cortical fragments in the chamber.
Postoperative inflammatory or infectious endophthalmitis needs to be considered in any eye with pain, inflammation, and elevated pressure shortly after cataract surgery, and distinguishing it from simple retained lens material is critical given the very different urgency and treatment each requires.
Pigmentary or inflammatory glaucoma from other causes lacks the visible cortical material and the clear temporal link to trauma or surgery that defines lens-particle glaucoma.
Management
Topical corticosteroids control the associated inflammation, and aqueous suppressants manage pressure elevation medically while a decision about surgical clearance is made.
Small amounts of retained cortical material sometimes clear spontaneously with medical management alone, particularly if the pressure response is mild and the inflammation is well controlled.
Surgical removal of retained lens material is indicated when pressure remains uncontrolled despite medical therapy, when inflammation is significant, or when the quantity of retained material is large enough that spontaneous clearance is unlikely.
Prompt surgical clearance, rather than prolonged medical management alone, is generally favored once the diagnosis is clear, since persistent lens material continues to provoke both inflammation and outflow obstruction for as long as it remains in the eye.
Patients recovering from complicated cataract surgery benefit from being told explicitly that a second, brief procedure to clear retained material is a recognized, manageable part of some complicated cases, rather than a sign that something has gone badly wrong overall.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Epstein DL. Diagnosis and management of lens-induced glaucoma. Ophthalmology.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 10: Glaucoma.
- Bowling B. Kanski’s Clinical Ophthalmology.
Test yourself
A few questions straight from this article.
-
Lens-particle glaucoma is a secondary open-angle glaucoma caused by which mechanism?
The pressure rise comes from solid particulate cortex physically clogging the trabecular meshwork and raising outflow resistance, not from protein leakage or crowding of the angle. -
What anatomical prerequisite must be present for lens-particle glaucoma to develop?
Cortical material can only escape into the anterior chamber once the capsule has been breached by penetrating trauma, blunt trauma or surgery. -
In modern practice, what is the commonest inciting event for lens-particle glaucoma?
Difficult or prolonged cataract surgery with capsular rupture and residual fragments is now the most frequent setting, ahead of either penetrating or blunt trauma. -
Which slit-lamp finding essentially confirms lens-particle glaucoma?
Visible white cortical material floating or layering in the chamber is diagnostic enough that little further workup is needed. -
Which feature distinguishes phacolytic glaucoma from lens-particle glaucoma?
Phacolytic glaucoma arises with the capsule still intact in an older eye with a hypermature cataract, and shows no free cortical fragments in the chamber. -
Which diagnosis must be excluded in a painful, inflamed, hypertensive eye soon after cataract surgery?
Endophthalmitis can look very like retained lens material early on, and separating the two matters because the urgency and the treatment are entirely different. -
What is the initial medical management of lens-particle glaucoma?
Steroids settle the inflammatory response to the retained material while aqueous suppressants hold the pressure down during the decision about surgical clearance. -
When is surgical removal of retained lens material indicated in lens-particle glaucoma?
Surgery is indicated for uncontrolled pressure, significant inflammation, or a volume of retained material too large for spontaneous clearance, and prompt clearance is generally favoured. -
What can happen to a small quantity of retained cortical material in lens-particle glaucoma?
Where the pressure response is mild and inflammation is well controlled, small amounts of retained cortex sometimes resolve without any further surgery. -
Over what period can retained cortex continue to raise pressure after the inciting event?
Retained cortical material can drive intermittent or progressive pressure elevation for weeks, so lens-particle glaucoma is not confined to the period right after trauma or surgery.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.