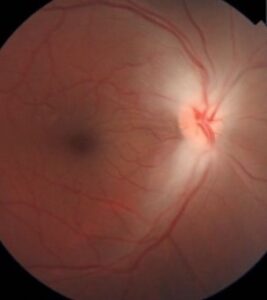
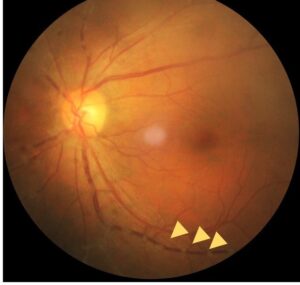
Optic disc drusen are calcified deposits within the optic nerve head itself, and they are the single most common cause of pseudopapilledema, discussed in its own dedicated article on this site, making the distinction between the two conditions one of the more practically important skills in neuro-ophthalmic examination.
Unlike true papilledema, which reflects elevated intracranial pressure and demands urgent neurological workup, optic disc drusen are a benign, if occasionally visually significant, structural anomaly that does not indicate any intracranial process.
Confusing the two can lead either to an unnecessary, invasive workup for a benign anatomic variant, or, in the opposite and more dangerous direction, to dismissing a genuinely swollen disc as drusen when it actually reflects a serious underlying neurological problem.
What Drusen Are
Optic disc drusen are composed of calcium, amino acids, and other proteinaceous material that accumulates progressively within the substance of the optic nerve head, most likely related to abnormal axonal metabolism and transport within a nerve that often has a smaller, more crowded scleral canal than average.
They are typically bilateral, though often asymmetric, and tend to become more calcified and visible over time, meaning a young child’s drusen may be entirely buried and invisible on fundus exam, only becoming apparent as more superficial, visible deposits emerge later in childhood or adolescence.
This progression from buried to superficial drusen is a key reason the diagnosis can be more difficult to confirm clinically in a young child than in an older patient with the same underlying anomaly.
Buried Versus Superficial Drusen
Buried drusen produce a disc appearance that can closely mimic true papilledema, elevated with blurred margins but without the true axonal swelling, vascular congestion, and hemorrhages typically associated with elevated intracranial pressure.
Superficial drusen are more readily recognized on direct examination, appearing as discrete, yellow-white, refractile nodules at the disc margin, sometimes described as looking like a cluster of small, glistening structures rather than a smoothly elevated, edematous disc.
The buried form is where diagnostic difficulty concentrates, and it is exactly this form that most often prompts the ancillary testing discussed below to distinguish it confidently from true disc swelling.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteDistinguishing Drusen From True Papilledema
- B-scan ultrasonography, discussed in its own dedicated article on this site, is highly effective for detecting calcified drusen, which show as highly reflective, echodense foci even when buried and not visible on direct exam
- Fundus autofluorescence, discussed in its own dedicated article on this site, can reveal the characteristic autofluorescent signal of drusen material without requiring any contrast dye
- Optical coherence tomography can show the drusen themselves as discrete, hyporeflective structures with characteristic shadowing, along with typically normal or only mildly elevated peripapillary retinal nerve fiber layer thickness, in contrast to the more pronounced diffuse thickening typical of true papilledema
- The absence of venous congestion, hemorrhage, cotton wool spots, and true axonal swelling on careful exam favors drusen over papilledema, though these features can occasionally be subtle in either condition
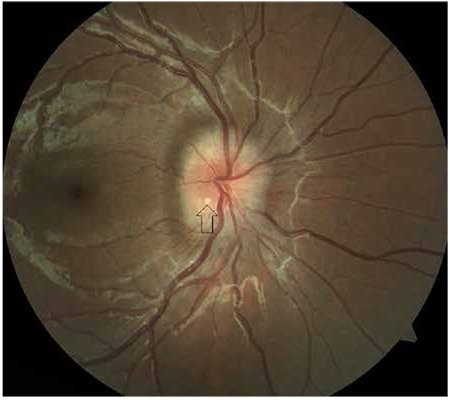
Clinical Significance
Optic disc drusen are usually asymptomatic and are frequently found incidentally during a routine eye exam, but a meaningful minority of patients develop visual field defects, most often an inferonasal arcuate or peripheral constriction pattern, related to the drusen’s mechanical effect on adjacent nerve fibers.
Rare but recognized complications include anterior ischemic optic neuropathy and, less commonly, choroidal neovascularization arising adjacent to the drusen, both of which can cause more acute, noticeable vision changes superimposed on the typically stable, slowly progressive baseline course.
Because true intracranial pathology and disc drusen can occasionally coexist in the same patient, a confirmed diagnosis of drusen does not automatically exclude a separate reason to investigate new neurological symptoms if they arise.
Management
No treatment is needed for the drusen themselves, since there is no way to remove or dissolve the calcified deposits, and management instead focuses on monitoring for the complications described above.
Baseline and periodic visual field testing, discussed in its own dedicated article on this site, helps detect and track any field loss related to the drusen’s mechanical effect on the nerve over time.
Patients found to have optic disc drusen benefit from a clear explanation of the diagnosis and its generally benign, stable course, which helps prevent unnecessary anxiety or repeated urgent neurological referrals for what is, in the great majority of cases, a stable structural finding rather than an evolving neurological emergency.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Auw-Haedrich C, Staubach F, Witschel H. Optic disk drusen. Survey of Ophthalmology.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 5: Neuro-Ophthalmology.
- Malmqvist L, Bursztyn L, Costello F, et al. The optic disc drusen studies consortium recommendations for diagnosis of optic disc drusen using optical coherence tomography. Journal of Neuro-Ophthalmology.
Test yourself
A few questions straight from this article.
-
Optic disc drusen are composed mainly of what material?
They consist of calcium, amino acids and other proteinaceous material that accumulates progressively within the substance of the optic nerve head. -
Optic disc drusen are the single most common cause of which clinical appearance?
They are the commonest cause of pseudopapilledema, which makes separating them from true disc swelling a core neuro-ophthalmic skill. -
Optic disc drusen tend to occur in nerves with which anatomic feature?
Formation is linked to abnormal axonal metabolism and transport in a nerve whose scleral canal is often smaller and more crowded than average. -
How do optic disc drusen typically behave over time?
Drusen calcify progressively, so deposits that are entirely buried in a young child often emerge as visible superficial nodules later in childhood or adolescence. -
On B-scan ultrasonography, optic disc drusen appear as what?
Because they are calcified, drusen show as highly reflective echodense foci on B-scan even when buried and invisible on direct examination. -
On OCT, which finding favours optic disc drusen over true papilledema?
OCT shows the drusen as discrete hyporeflective structures with characteristic shadowing, with nerve fibre layer thickness normal or only mildly raised rather than markedly thickened. -
Which visual field pattern is most often associated with optic disc drusen?
A meaningful minority of patients develop field loss, most often an inferonasal arcuate defect or peripheral constriction from the mechanical effect on adjacent nerve fibres. -
Which uncommon but recognised complication can arise in eyes with optic disc drusen?
Anterior ischaemic optic neuropathy and, less often, choroidal neovascularisation beside the drusen can cause acute visual change against an otherwise stable course. -
What does a confirmed diagnosis of optic disc drusen mean if new neurological symptoms appear?
Drusen and genuine intracranial disease can coexist in the same patient, so the structural diagnosis does not remove the need to investigate new neurological symptoms. -
What does management of optic disc drusen consist of?
The deposits cannot be removed or dissolved, so care consists of baseline and periodic perimetry to track field loss, plus clear counselling about the benign course.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.