Hertel exophthalmometry measures the distance from the lateral orbital rim to the corneal apex in millimeters.
It gives a simple number for axial globe protrusion, and clinicians use it to detect proptosis, compare the two eyes and follow orbital disease over time. However, the reading is only as good as the technique behind it.
What Hertel Exophthalmometry Measures
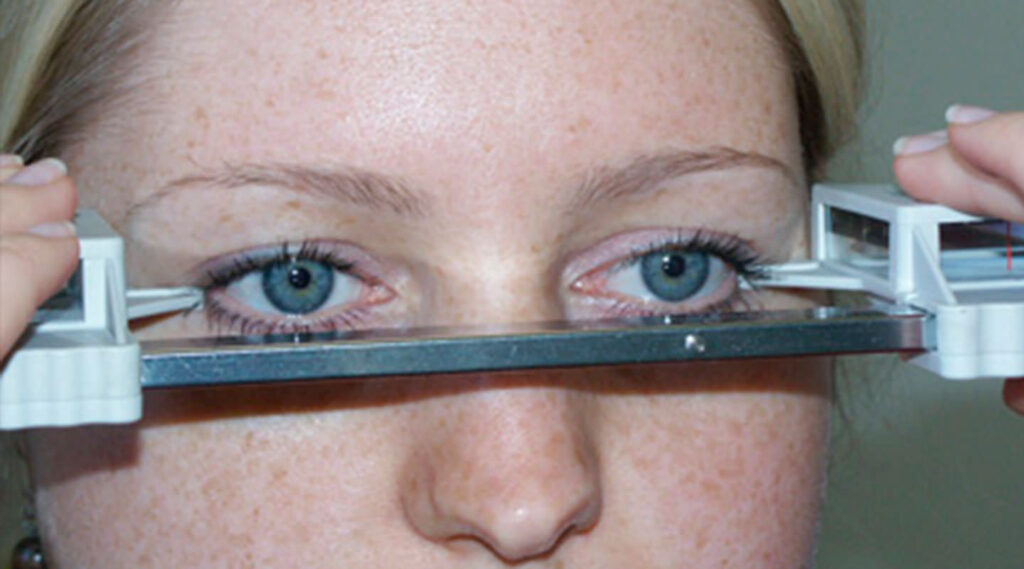
The instrument rests on both lateral orbital rims and projects the corneal apex onto a millimeter scale. As a result, the reading reflects how far each cornea sits in front of the lateral rim, but it does not measure the globe itself. Therefore, any change in the rim, the lids or the axial length can alter the number.
Parts of the Instrument
A horizontal bar carries two measuring units, and each unit has a footplate, a mirror or prism system, and a scale. The distance between the footplates is the base reading, printed on the bar.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this sitePreparing the Patient
First, seat the patient upright, facing you at the same eye level, and next explain that the footplates will rest gently on the bone beside each eye. Then ask the patient to keep the head still and both eyes open, and remove spectacles, because frames block the footplates.
Hertel Exophthalmometry Technique Step by Step
- First, place each footplate at the deepest point of the lateral orbital rim.
- Then adjust the bar until both footplates sit firmly without pressing soft tissue.
- Next, record the base reading.
- Then ask the patient to fixate in primary gaze on your open eye.
- Finally, align the parallax marks and read the corneal apex on the scale.
- Then repeat the steps for the fellow eye.
Recording the Result
Write both eye values and the base, for example “18 / 20, base 100,” so later readings can be compared reliably. Also note the device used, since different instruments may not agree exactly.
Normal Values in Hertel Exophthalmometry
Normal adult readings commonly fall within a range of about 12 to 21 mm, but values vary with ethnicity, sex and age. For example, Migliori and Gladstone reported higher normal limits in Black adults than in white adults. Therefore, interpret a borderline value against the patient’s own population and old photographs.
Asymmetry Thresholds
A difference of about 2 mm or more between the eyes is widely treated as suspicious, and asymmetry often carries more weight than the absolute value. As a result, a symmetric 22 mm may be normal for one patient, while an asymmetric 19 mm may not be.
Hertel Exophthalmometry in Thyroid Eye Disease
Proptosis is a core feature of thyroid eye disease (see thyroid eye disease), and serial readings help stage severity and track progression during the active phase. EUGOGO guidance treats an increase of 2 mm or more as a meaningful change.
Tracking Treatment Response
Trials of teprotumumab used a proptosis reduction of at least 2 mm as a primary response measure, so consistent technique matters when you judge whether a drug is working. However, readings taken by different examiners may vary close to that threshold, so keep the same examiner, device and base at each visit when possible.
Interobserver Variability
Studies report meaningful differences between observers using the same patient, and footplate position and soft tissue pressure explain much of this variation. Parallax also adds error when the alignment marks are ignored, so a true change may hide inside measurement noise.
Limits of Hertel Exophthalmometry
The method depends on a normal, symmetric lateral orbital rim. However, fractures, previous orbital surgery or congenital asymmetry make the reading unreliable, and lateral wall decompression also moves the reference point. In these cases, CT measurements or clinical photographs may serve better.
Pseudoproptosis and Mimics
Several conditions make an eye look prominent without true proptosis.
- For example, high axial myopia or buphthalmos
- Also, upper or lower lid retraction
- Enophthalmos of the fellow eye
- Contralateral ptosis
- Facial or orbital rim asymmetry
Hertel Exophthalmometry and Imaging
A rising reading should prompt examination of motility, pupils and optic nerve function. Unilateral or rapidly progressive proptosis usually warrants orbital imaging, and imaging also helps when the rim landmark is abnormal. However, the exophthalmometer remains the quickest bedside screen.
Counseling the Patient
Patients often worry that one eye is bulging. First, explain that the test is painless and takes less than a minute, then show them the numbers and what a meaningful change looks like.
Pitfalls to Avoid
- Do not compare readings taken with different bases
- Never press footplates into soft tissue
- Also avoid reading without aligning the parallax marks
- Do not rely on the device after lateral rim fracture or decompression
- Always check for pseudoproptosis before labeling proptosis


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Migliori ME, Gladstone GJ. Determination of the normal range of exophthalmometric values for black and white adults. Am J Ophthalmol. 1984;98:438-442.
- Bartalena L, Kahaly GJ, Baldeschi L, et al. The 2021 European Group on Graves’ orbitopathy (EUGOGO) clinical practice guidelines for the medical management of Graves’ orbitopathy. Eur J Endocrinol. 2021;185:G43-G67.
- Douglas RS, Kahaly GJ, Patel A, et al. Teprotumumab for the treatment of active thyroid eye disease. N Engl J Med. 2020;382:341-352.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 7: Oculofacial Plastic and Orbital Surgery. San Francisco: AAO; latest edition.
- Bowling B. Kanski’s Clinical Ophthalmology: A Systematic Approach. 8th ed. Elsevier; 2016.
Test yourself
A few questions straight from this article.
-
What distance does Hertel exophthalmometry measure?
The instrument rests on both lateral orbital rims and reads, in millimeters, how far each corneal apex sits in front of the rim; it does not measure the globe itself. -
Within roughly what range do normal adult Hertel exophthalmometry readings commonly fall?
Normal adult readings commonly fall around 12 to 21 mm, but they vary with ethnicity, sex and age, so borderline values should be judged against the patient's own population. -
On Hertel exophthalmometry, what inter-eye difference is widely treated as suspicious for proptosis?
An asymmetry of about 2 mm or more is treated as suspicious, and asymmetry often carries more weight than the absolute value. -
In teprotumumab trials for thyroid eye disease, what served as a primary response measure?
The trials judged response by a proptosis reduction of at least 2 mm, which is why consistent exophthalmometry technique matters when assessing whether a drug is working. -
Where should each footplate of a Hertel exophthalmometer be placed?
Each footplate sits at the deepest point of the lateral orbital rim, firmly but without pressing into soft tissue. -
Besides both eye values, what must be recorded with a Hertel exophthalmometry reading so later readings are comparable?
Readings are written with the base, for example 18 / 20, base 100, because readings taken with different bases should not be compared; the device used is also noted. -
After a lateral orbital rim fracture or lateral wall decompression, what may assess proptosis better than Hertel exophthalmometry?
The method depends on a normal, symmetric lateral rim; fractures, orbital surgery or decompression move the reference point, so CT measurements or photographs may serve better. -
Which condition can make an eye look prominent without true proptosis on Hertel exophthalmometry?
High axial myopia or buphthalmos, lid retraction, fellow-eye enophthalmos, contralateral ptosis and facial asymmetry are listed as causes of pseudoproptosis to exclude before labelling proptosis. -
What explains much of the interobserver variability in Hertel exophthalmometry readings?
Footplate position and soft tissue pressure account for much of the variation between observers, and ignoring the parallax marks adds further error. -
Which pattern of proptosis found on Hertel exophthalmometry usually warrants orbital imaging?
Unilateral or rapidly progressive proptosis usually warrants orbital imaging, and a rising reading should also prompt checks of motility, pupils and optic nerve function.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.