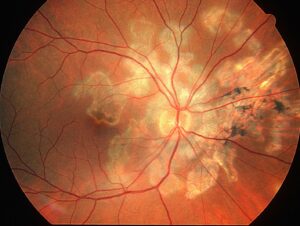
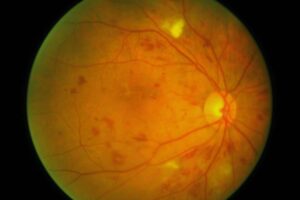
Choroidal tubercles are small, yellow-white lesions deep to the retina that signal hematogenous spread of Mycobacterium tuberculosis.
Reviews describe them as a frequent intraocular sign of disseminated tuberculosis. A careful dilated fundus exam can therefore support a diagnosis that chest imaging has not yet confirmed.
What Choroidal Tubercles Are
Each tubercle is a granuloma in the choroid that forms around bacilli in the bloodstream. Because choroidal blood flow is so high, seeding often happens there first, and when a single lesion keeps enlarging, clinicians call it a tuberculoma.
Fundus Appearance of Choroidal Tubercles
The lesions look round or oval, pale yellow, gray or white, with soft, indistinct borders. Most are smaller than one disc diameter, although size varies, and they usually sit in the posterior pole, often near the optic disc.
Numbers range from one or two to dozens, and lesions often affect both eyes. Moreover, the overlying retina usually stays flat and clear.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteWho Develops Them
Miliary disease affects young children, older adults and people with weak cell-mediated immunity. Therefore, HIV infection, malnutrition, diabetes, renal failure and anti-TNF therapy raise suspicion. Tubercles also accompany tuberculous meningitis, so examine the fundus in any patient with that diagnosis.
Symptoms Patients Report
Many patients have no visual complaint at all, and instead vision drops only when a lesion involves the macula or causes subretinal fluid. Meanwhile, fever, weight loss, night sweats and cough dominate the history. As a result, the ophthalmologist often sees an inpatient referred by physicians.
Examining for Choroidal Tubercles
Dilate both pupils and use indirect ophthalmoscopy first for a wide survey. Then examine the posterior pole at the slit lamp with a 78 D or 90 D lens, and also record the number, size and position of each lesion for later comparison.
Imaging Choroidal Tubercles
Fundus photography documents the baseline and makes follow-up objective, while on fluorescein angiography, active lesions are usually hypofluorescent early and hyperfluorescent late. However, indocyanine green angiography often reveals more hypofluorescent dots than the clinical exam shows. OCT also shows a dome-shaped choroidal elevation, sometimes with subretinal fluid above it.
Why the Sign Matters Systemically
A tubercle places the eye inside a disseminated infection, and chest radiographs can look normal early, so a clear film does not exclude miliary disease. In addition, tuberculin skin tests and interferon-gamma release assays may be falsely negative in severe disease, so the fundus finding can justify earlier tissue sampling and treatment.
Differential of Choroidal Tubercles
Several multifocal choroidal lesions can look similar, especially in immunocompromised patients.
- Pneumocystis choroidopathy, with flat yellow plaques in HIV
- Cryptococcal and other fungal choroiditis
- Sarcoid choroidal granulomas
- Choroidal metastases, usually larger and fewer
- Multifocal choroiditis, birdshot chorioretinopathy and other white dot syndromes
- Septic emboli and Roth spots
Features That Point Elsewhere
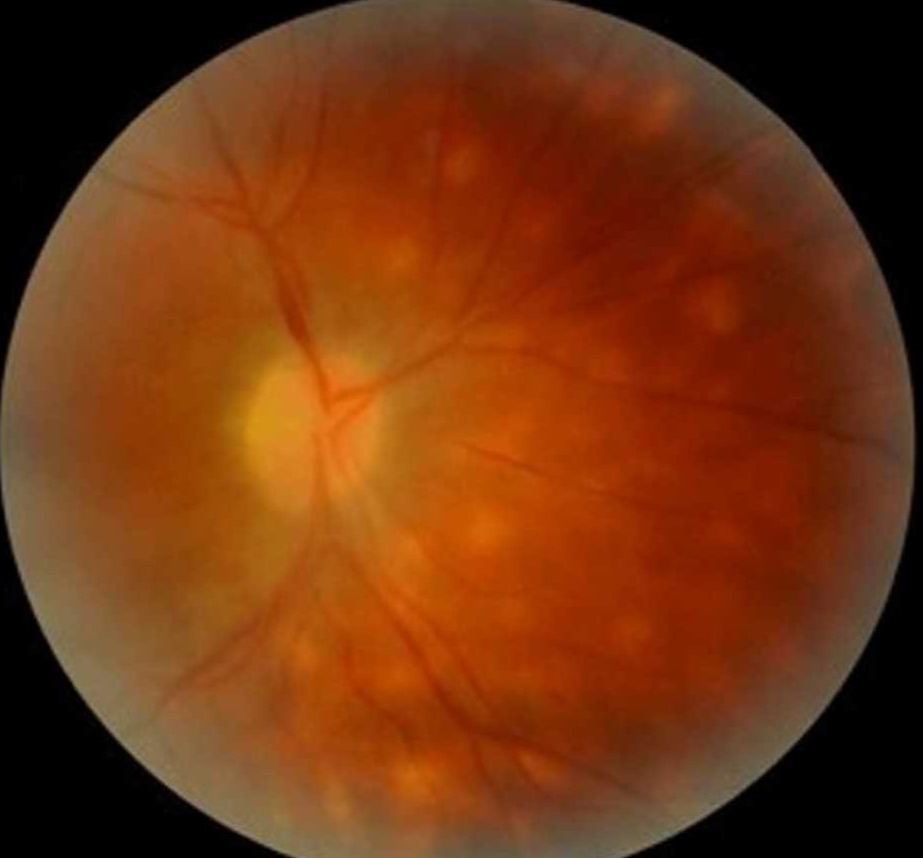
For example, Candida usually breaks through into the vitreous, forming fluffy white balls. In contrast, tubercles stay deep and the vitreous often remains quiet.
Drusen and hard exudates sit at different levels, and their margins are sharper (see drusen vs exudates). A solitary flat pigmented lesion suggests a nevus instead (see choroidal nevus vs small melanoma).
Systemic Workup After Choroidal Tubercles
Share the findings promptly with infectious disease or internal medicine colleagues.
- Chest CT if the radiograph is normal or equivocal
- Sputum or gastric aspirate for smear, culture and nucleic acid testing
- Blood and urine mycobacterial cultures
- HIV testing in every patient
- Lumbar puncture when headache, confusion or neck stiffness appear
Treatment of Choroidal Tubercles
Tubercles respond to standard systemic antituberculous therapy with multiple drugs. Physicians then choose the regimen and duration according to national guidelines and disease sites. They may also add corticosteroids for meningitis or severe inflammation, always under antimicrobial cover.
Expected Course on Therapy
Lesions usually fade over weeks to months once treatment starts, and afterwards they often heal as flat atrophic scars with pigmented edges. However, new lesions can appear early during therapy as a paradoxical reaction. For example, in HIV patients starting antiretrovirals, this may reflect immune reconstitution inflammatory syndrome.
Counseling the Patient
Explain that the spots reflect infection elsewhere in the body, and the eyes act as a window, and most patients keep good vision when the macula is spared. Also stress full adherence, because stopping early risks relapse and drug resistance, and then ask them to report blurred vision or color change during ethambutol use.
Follow-Up in Choroidal Tubercles
Review the fundus after a few weeks, then at intervals matched to clinical progress. Next, compare photographs to confirm that lesions shrink and no new ones develop. Finally, persistent growth despite therapy should prompt a search for resistance or another diagnosis.
Pitfalls to Avoid
- Do not skip fundus examination in suspected miliary TB or TB meningitis
- Never rely on a normal chest radiograph, because early films can be clear
- Do not dismiss negative IGRA results in severely ill patients
- Avoid steroids alone for multifocal choroiditis until TB is excluded


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Gupta V, Gupta A, Rao NA. Intraocular tuberculosis: an update. Surv Ophthalmol. 2007;52:561-587.
- Massaro D, Katz S, Sachs M. Choroidal tubercles: a clue to hematogenous tuberculosis. Ann Intern Med. 1964;60:231-241.
- Illingworth RS, Wright T. Tubercles of the choroid. Br Med J. 1948;2:365-368.
- Agrawal R, Testi I, Mahajan S, et al. Collaborative Ocular Tuberculosis Study consensus guidelines on the management of tubercular uveitis, report 1. Ophthalmology. 2021;128:266-276.
- Bowling B. Kanski’s Clinical Ophthalmology: A Systematic Approach. 8th ed. Elsevier; 2016.
Test yourself
A few questions straight from this article.
-
What is a choroidal tubercle in disseminated tuberculosis?
Each tubercle is a granuloma in the choroid that forms around Mycobacterium tuberculosis carried in the blood; a single lesion that keeps enlarging is called a tuberculoma. -
Why is the choroid often the first ocular site seeded in hematogenous tuberculosis?
Because choroidal blood flow is so high, circulating bacilli often seed the choroid first, where granulomas then form. -
What are the typical size and location of choroidal tubercles in miliary tuberculosis?
Most tubercles are smaller than one disc diameter and usually sit in the posterior pole, often near the optic disc, frequently in both eyes. -
Which feature helps separate choroidal tubercles from Candida chorioretinitis?
Candida usually breaks through into the vitreous, forming fluffy white balls, whereas tubercles stay deep beneath a flat retina and the vitreous is often quiet. -
Which imaging test often shows more choroidal tubercles than clinical examination reveals?
Indocyanine green angiography often reveals more hypofluorescent dots than the clinical exam shows, while fluorescein shows active lesions hypofluorescent early and hyperfluorescent late. -
A patient has choroidal tubercles but a normal chest radiograph. How should this radiograph be interpreted?
Chest radiographs can look normal early in miliary tuberculosis, so a clear film does not exclude it; chest CT is advised when the radiograph is normal or equivocal. -
Which test is recommended for every patient in the systemic workup after choroidal tubercles are found?
The workup includes HIV testing in every patient, alongside chest CT when needed, sputum or gastric aspirate testing and mycobacterial blood and urine cultures. -
What is the treatment of choroidal tubercles?
Tubercles respond to standard systemic multidrug antituberculous therapy; corticosteroids may be added for meningitis or severe inflammation, always under antimicrobial cover. -
New choroidal tubercles appear early in TB therapy in an HIV patient starting antiretrovirals. What may this reflect?
New lesions can appear early during therapy as a paradoxical reaction, and in HIV patients starting antiretrovirals this may reflect immune reconstitution inflammatory syndrome. -
Choroidal tubercles keep growing despite antituberculous therapy. What should this prompt?
On follow-up, photographs should confirm that lesions shrink; persistent growth despite therapy should prompt a search for resistance or an alternative diagnosis.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.